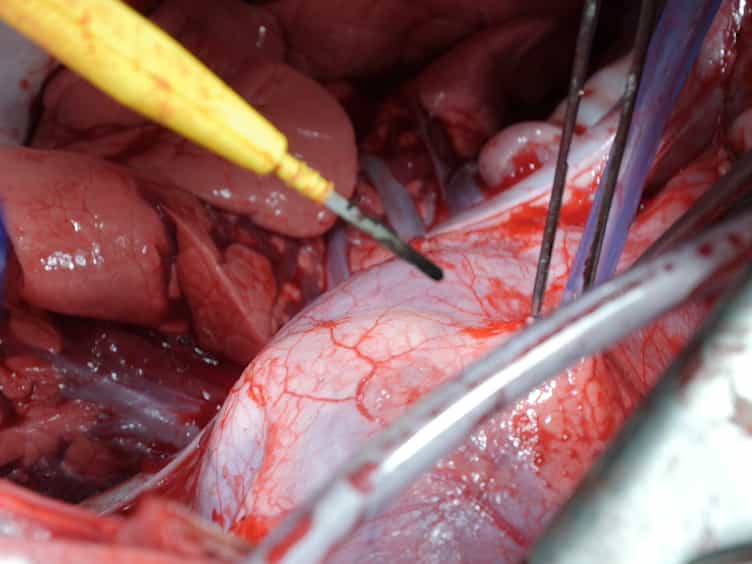
Related Experiment Video
Updated: May 13, 2025

Three-Dimensional Printing of a Complex Aortic Anomaly
Published on: November 1, 2018
Concomitant Kommerell diverticulectomy, carotid-subclavian bypass, and modified ravitch pectus excavatum repair via
Carlo R Bartoli1,2,3, Shiv Patel4, Victor Mallory5,6
1Division of Pediatric and Adult Congenital Cardiothoracic Surgery, Geisinger Medical Center, 100 North Academy Ave, MC 27-75, Danville, PA, 17822, USA. crbartoli@geisinger.edu.

Insights
This study details a successful single-stage surgical repair for a 17-year-old male with congenital heart disease and pectus excavatum, highlighting a viable approach for complex cases.
Area of Science:
- Cardiovascular Surgery
- Thoracic Surgery
- Congenital Malformations
Background:
- Congenital heart disease (CHD) can coexist with pectus excavatum, presenting complex surgical challenges.
- The optimal surgical strategy, whether concomitant or staged repair, remains a subject of debate.
- Associated vascular anomalies, such as Kommerell diverticulum, can complicate surgical planning.
Purpose of the Study:
- To report a case of concomitant repair of complex CHD and pectus excavatum.
- To evaluate the feasibility and safety of a single-stage surgical approach.
- To review existing literature on operative strategies for combined CHD and pectus excavatum repair.
Main Methods:
- A 17-year-old male with left aortic arch, aberrant right subclavian artery, Kommerell diverticulum, and pectus excavatum underwent surgical intervention.
- The procedure involved Kommerell diverticulectomy, carotid-subclavian bypass, and modified Ravitch pectus excavatum repair.
- The repair was performed as a single operation via sternotomy.
Main Results:
- The patient presented with dysphagia, nausea, and cosmetic concerns related to pectus excavatum.
- The concomitant surgical repair was successfully completed without any complications.
- The patient experienced relief from swallowing difficulties and cosmetic improvement.
Conclusions:
- Concomitant surgical repair of congenital heart disease and pectus excavatum is feasible and safe when performed in a single operation via sternotomy.
- This approach can effectively address both cardiovascular and thoracic wall abnormalities simultaneously.
- Further investigation into the comparative outcomes of concomitant versus staged repairs is warranted.
Abstract:
Congenital heart disease may present with pectus excavatum. Concomitant and staged repair are described, but the optimal approach is controversial. We report a 17-year-old male with left aortic arch, aberrant right subclavian artery, and Kommerell diverticulum who presented with long standing swallowing difficulties, prandial nausea, and pectus excavatum with cosmetic concerns. Kommerell diverticulectomy, carotid-subclavian bypass, and modified Ravitch pectus excavatum repair were performed without complication. Concomitant congenital heart surgery and pectus excavatum repair may be successfully performed in a single operation via sternotomy. Incidence, operative approaches, and complications of concomitant versus staged correction of congenital heart disease and pectus excavatum are briefly reviewed.