

Effects of Obesity and Sex on Supine Functional Residual Capacity and Expiratory Flow Limitation in Children
Dharini M Bhammar1,2,3, Daniel P Wilhite3,4, Temitayo Olojo2,5
1Division of Medical Oncology, Department of Internal Medicine, College of Medicine, The Ohio State University Wexner Medical Center, Columbus, Ohio, USA.

Insights
Children with obesity breathe at lower lung volumes when lying down, increasing their risk for expiratory flow limitation (EFL). Understanding these physiological changes can help manage sleep issues in obese children.
Area of Science:
- Pediatric Pulmonology
- Obesity Research
- Sleep Medicine
Background:
- Childhood obesity is linked to sleep-disordered breathing.
- Physiologic mechanisms underlying this association require further investigation.
Purpose of the Study:
- To examine the impact of obesity on lung volumes and expiratory flow limitation (EFL) in the supine position.
- To assess respiratory symptoms in relation to obesity and posture.
Main Methods:
- Compared lung volumes and EFL in 94 children (8-12 years) with and without obesity in seated and supine positions.
- Simulated obesity in lean children using abdominal mass loading (2.3kg or 5.0kg).
- Recorded ratings of perceived breathlessness (RPB).
Main Results:
- Children with obesity exhibited significantly lower functional residual capacity (FRC) in the supine position compared to seated.
- Expiratory flow limitation (EFL) was more prevalent in obese children when supine.
- Abdominal mass loading in lean children reduced FRC and increased RPB, mimicking obesity effects.
Conclusions:
- Obesity leads to reduced lung volumes in the supine position, elevating the risk of EFL in children.
- A deeper understanding of obesity's mechanical effects is crucial for managing sleep-related symptoms in pediatric obesity.
Introduction:
Childhood obesity is associated with a higher risk of sleep-disordered breathing, but our understanding of the underlying physiologic mechanisms is limited. This study investigated the effects of obesity on lung volumes, expiratory flow limitation (EFL), and respiratory symptoms in the supine position.
Methods:
Ninety-four children (8-12 years old, n = 58 with obesity and n = 36 without obesity) underwent lung volume and EFL measurements in the seated and supine positions in this repeated-measures cross-sectional study. Children without obesity underwent an additional condition where either a 2.3 kg (n = 26) or 5.0 kg (n = 8) mass was placed on their abdomen to simulate obesity. Ratings of perceived breathlessness (RPB) were recorded.
Results:
Functional residual capacity (FRC) in the supine when compared with the seated posture decreased more so in children without obesity (43.9 ± 1.0 vs. 34.4 ± 1.0% total lung capacity [TLC]) compared with children with obesity (35.5 ± 0.8 vs. 29.6 ± 0.8% TLC; p = 0.0048 group*posture). EFL in the supine position was present in 17% of children with obesity compared with 6% of children without obesity (p = 0.1218). In children without obesity, mass-loading with 5.0 kg produced further reductions in FRC (seated: 45.0 ± 1.7% TLC; supine: 36.7 ± 1.7% TLC; supine+5.0 kg: 29.4 ± 1.7% TLC; p = 0.0087 seated vs. supine+ and p = 0.0178 supine vs. supine + ) and an increase in RPB (seated: 0.38 ± 0.24; supine: 0.42 ± 0.24; supine+5.0 kg: 1.25 ± 0.27; p = 0.0002 seated vs. supine+ and p = 0.0001 supine vs. supine + ).
Conclusions:
Children with obesity breathe at significantly lower lung volumes while supine, increasing the risk of EFL. A better physiologic understanding of the mechanical effects of obesity could potentially improve the management of sleep-related symptoms among children with obesity.


Related Concept Videos
 01:47
Lung Capacity
 01:15
Respiratory Volumes
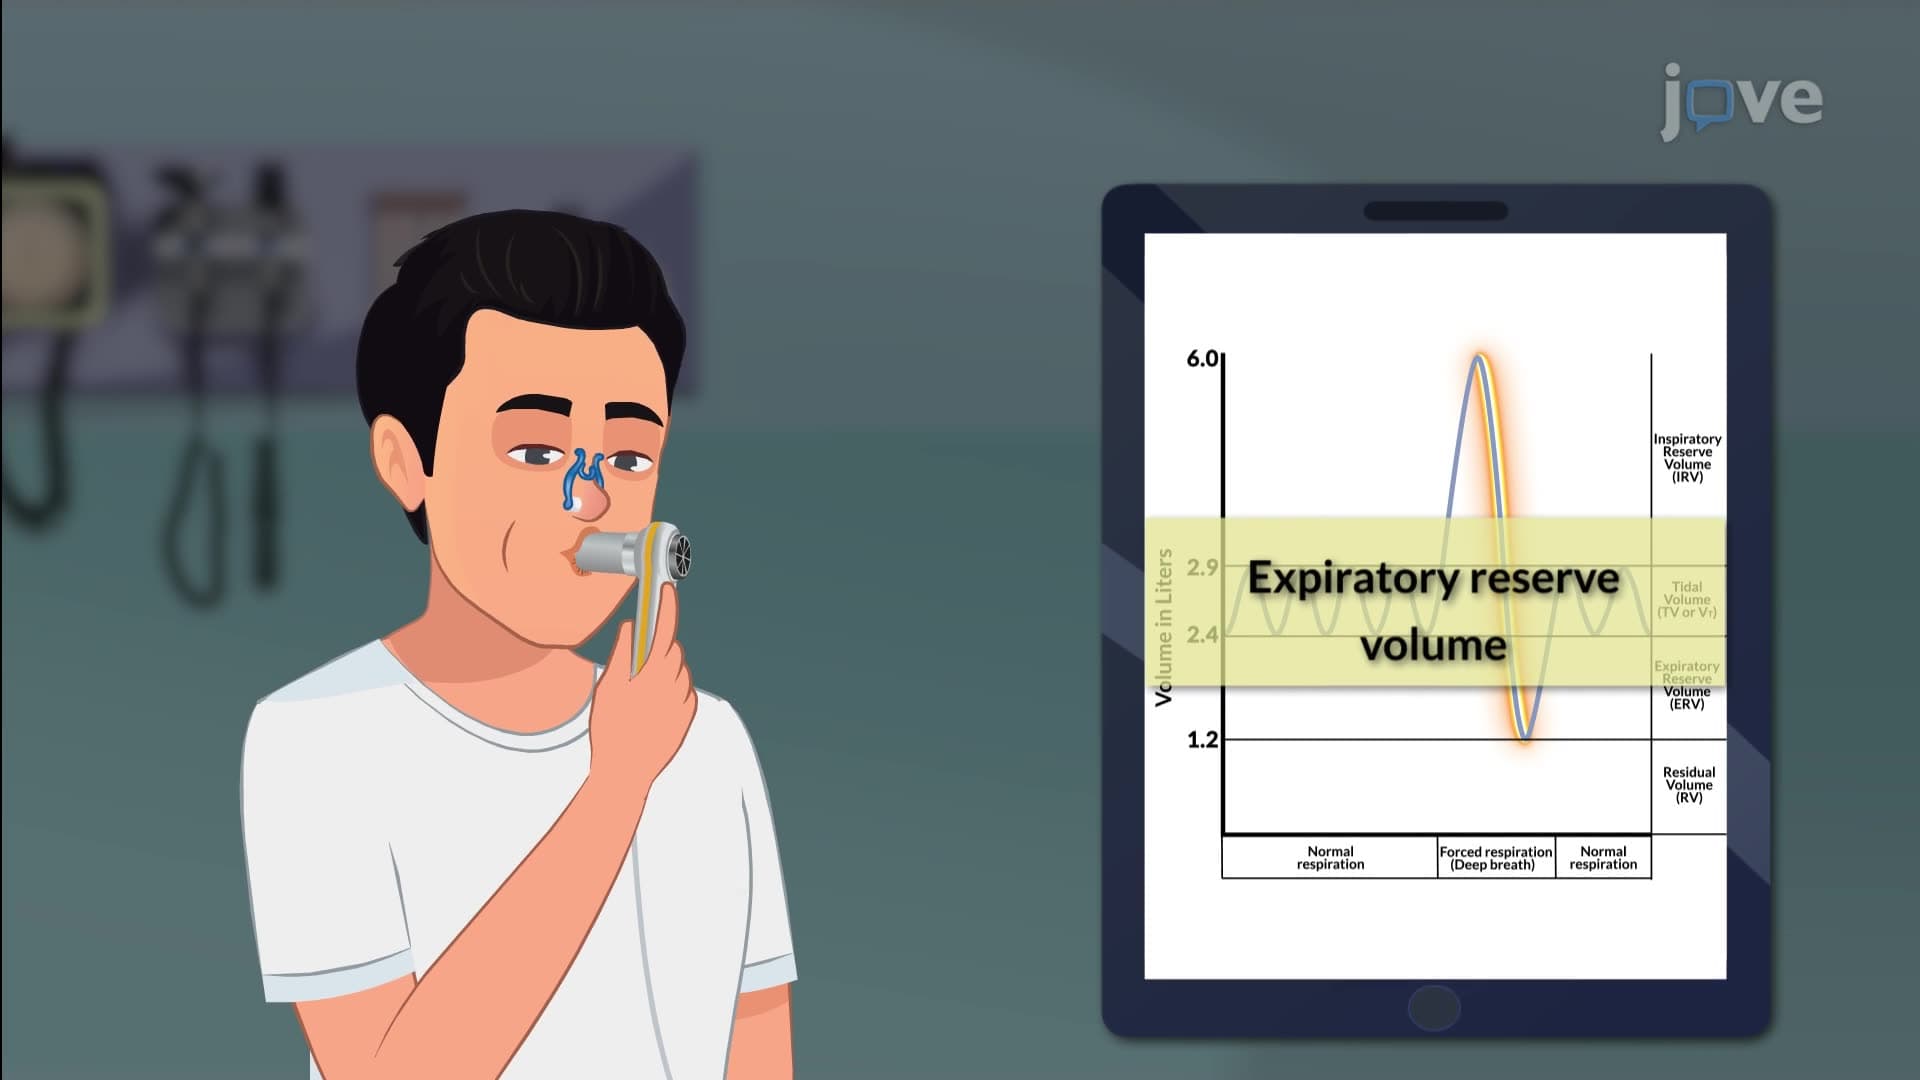
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History