Related Experiment Video
Updated: May 11, 2025


Use of a Central Venous Line for Fluids, Drugs and Nutrient Administration in a Mouse Model of Critical Illness
Published on: May 2, 2017
Parenteral calcium administration and outcomes in critically ill patients with hypocalcemia: A retrospective cohort
Max Melchers1,2, Hanneke Pierre Franciscus Xaverius Moonen1,2, Tessa Maria Breeman1
1Department of Intensive Care Medicine, Gelderse Vallei Hospital, 6761 EP, Ede, The Netherlands.

Insights
Parenteral calcium did not improve survival or shock resolution in intensive care unit (ICU) patients with hypocalcemia. In fact, it may increase mortality risk, especially in sepsis patients with mild hypocalcemia.
Area of Science:
- Critical Care Medicine
- Intensive Care Unit (ICU) Management
- Electrolyte Balance
Background:
- Hypocalcemia is a common complication in intensive care unit (ICU) patients.
- The use of calcium in critically ill patients with hypocalcemia is debated due to conflicting outcome data.
- Subgroup analyses on calcium administration outcomes are lacking.
Purpose of the Study:
- To investigate the association between parenteral calcium administration and clinical outcomes in critically ill patients with hypocalcemia.
- To analyze outcomes in both sepsis and non-sepsis patient groups.
- To examine the impact of calcium on mortality and shock resolution.
Main Methods:
- Retrospective cohort study of adult ICU patients with hypocalcemia.
- Inclusion criteria: first 7 days of ICU admission, no renal replacement therapy, ≥48 hours ICU stay.
- Primary outcomes: 180-day mortality and time-to-shock resolution; subgroup analyses for sepsis/non-sepsis and mild/moderate hypocalcemia.
Main Results:
- No significant difference in 180-day mortality between patients receiving and not receiving parenteral calcium (aHR=1.18).
- Parenteral calcium was associated with a shorter time to shock resolution (aOR=0.81).
- Increased mortality risk observed in sepsis patients with mild hypocalcemia receiving calcium (aHR=1.88 for 90-day, aHR=1.79 for 180-day).
Conclusions:
- Parenteral calcium administration offers no survival or shock resolution benefits for ICU patients with hypocalcemia.
- Calcium administration may be associated with increased mortality, particularly in specific subgroups like sepsis patients with mild hypocalcemia.
- Further research, including randomized controlled trials, is necessary to validate these findings.
Background:
Hypocalcemia is common among patients admitted to the intensive care unit (ICU). The administration of calcium in critically ill patients with hypocalcemia remains debated, as previous data on outcomes are conflicting, and subgroup analyses are lacking. This study aimed to investigate the association between parenteral calcium administration and clinical outcomes in critically ill patients who had hypocalcemia with and without sepsis.
Methods:
This retrospective cohort study included individuals who developed hypocalcemia during the first 7 days of admission to a mixed medical-surgical adult ICU at a University-affiliated teaching hospital. Patients who were not receiving renal replacement therapy, and were admitted to the ICU for at least 48 h between October 1, 2015 and September 24, 2020, were included. The primary outcomes included all-cause 180-day mortality and time-to-shock resolution. Subgroup analyses were conducted in sepsis and nonsepsis patients with mild or moderate hypocalcemia, based on median splits. Proportional hazard regression analyses were performed to identify the association between parenteral calcium administration and outcome parameters.
Results:
Among the 1100 patients who met the inclusion criteria, 427 (38.8 %) patients were admitted for sepsis and 576 (52.4 %) patients received parenteral calcium. Patients who received and did not receive parenteral calcium demonstrated no significant difference in 180-day mortality (adjusted hazard ratio [aHR] = 1.18, 95 % confidence interval [CI]: 0.90 to 1.56). Intravenous calcium administration reduced the probability of a shorter time to shock resolution (adjusted odds ratio = 0.81, 95 % CI: 0.70 to 0.94). Subgroup analyses in patients with and without sepsis indicated no significant association between calcium administration (aHR = 1.63, 95 % CI: 0.99 to 2.69) and 180-day mortality (aHR = 1.06, 95 % CI: 0.74 to 1.51). Notably, parenteral calcium was associated with an elevated risk of 90- and 180-day mortality in patients who had sepsis and mild hypocalcemia (aHR = 1.88, 95 % CI: 1.02 to 3.47 and aHR = 1.79, 95 % CI: 1.07 to 3.00, respectively).
Conclusions:
Intravenous calcium administration did not provide survival or shock resolution benefits in ICU patients with hypocalcemia, and may even be harmful. Further research, including randomized controlled trials, are needed to confirm these findings.


Related Concept Videos
 01:21
Skeleton and Calcium Homeostasis
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 00:51
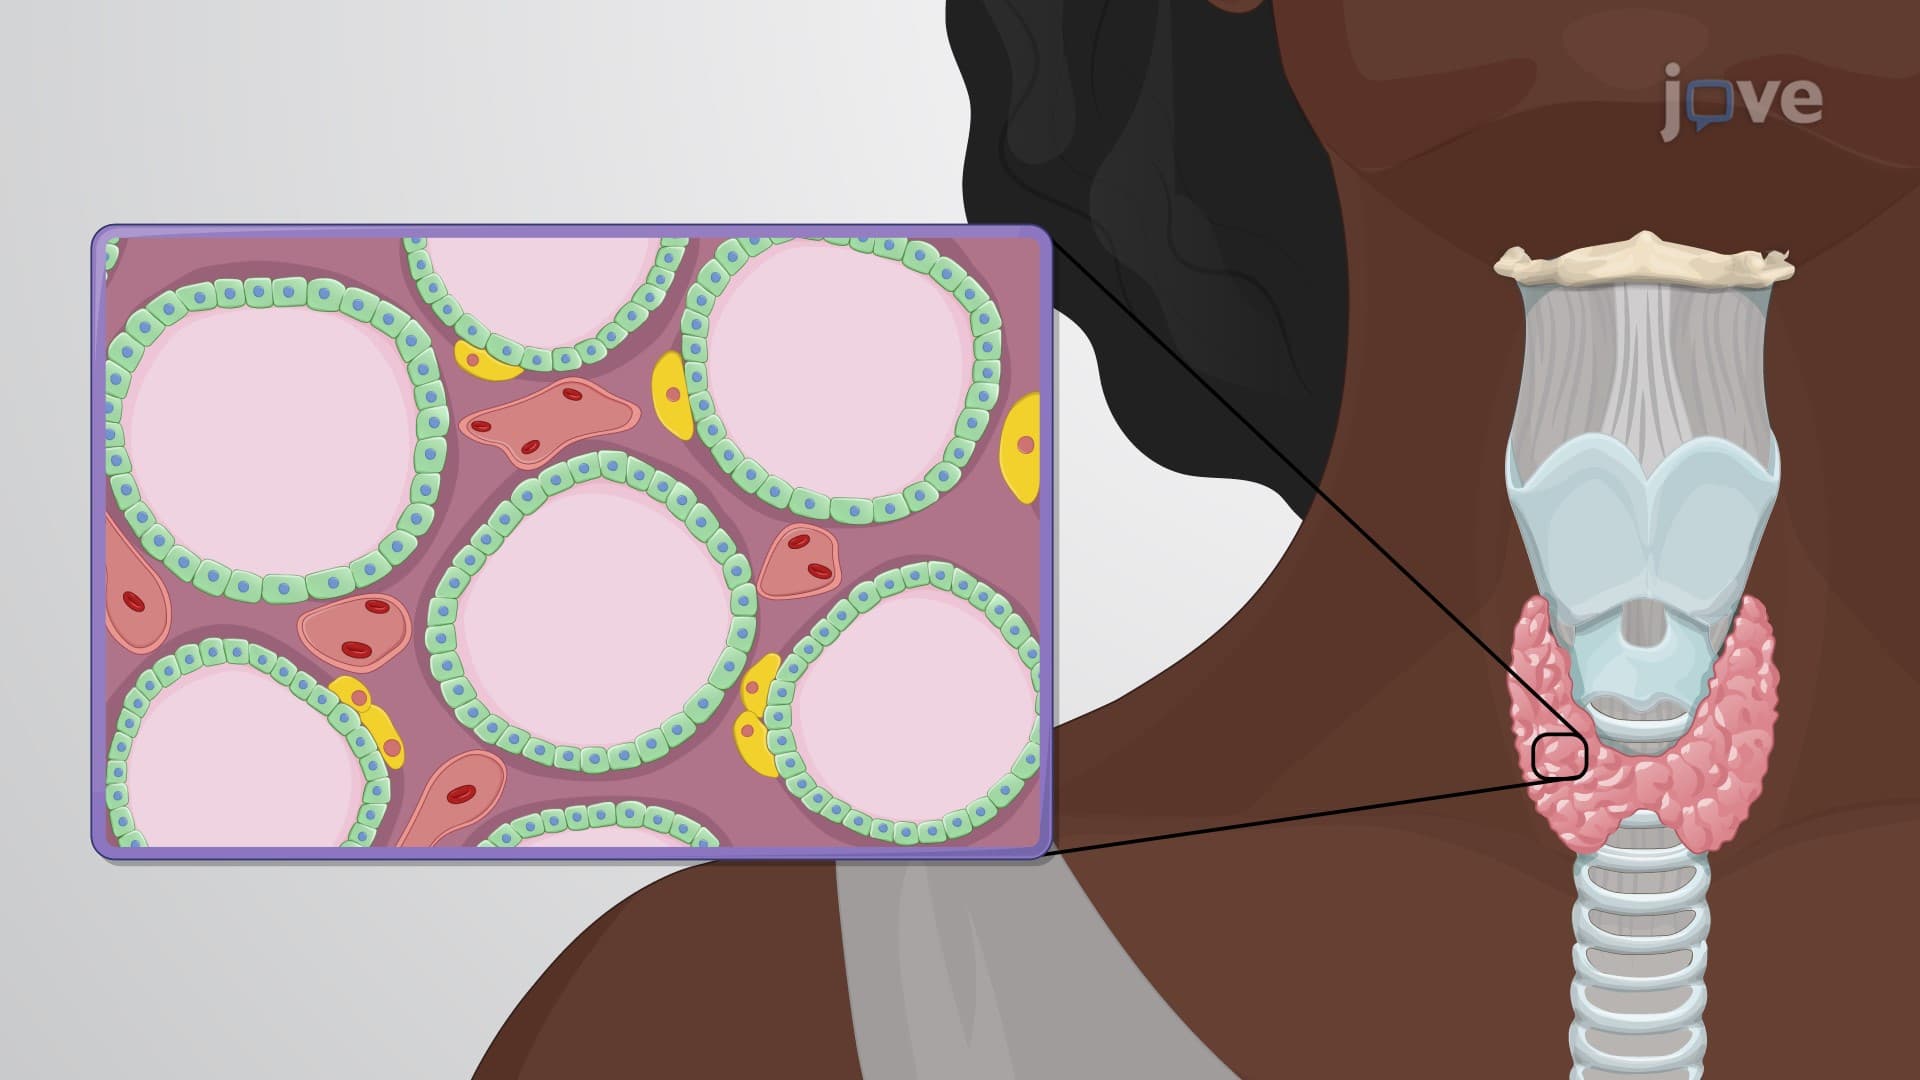
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:24
Parenteral Anesthetics: Overview
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...