Related Experiment Video
Updated: May 10, 2025
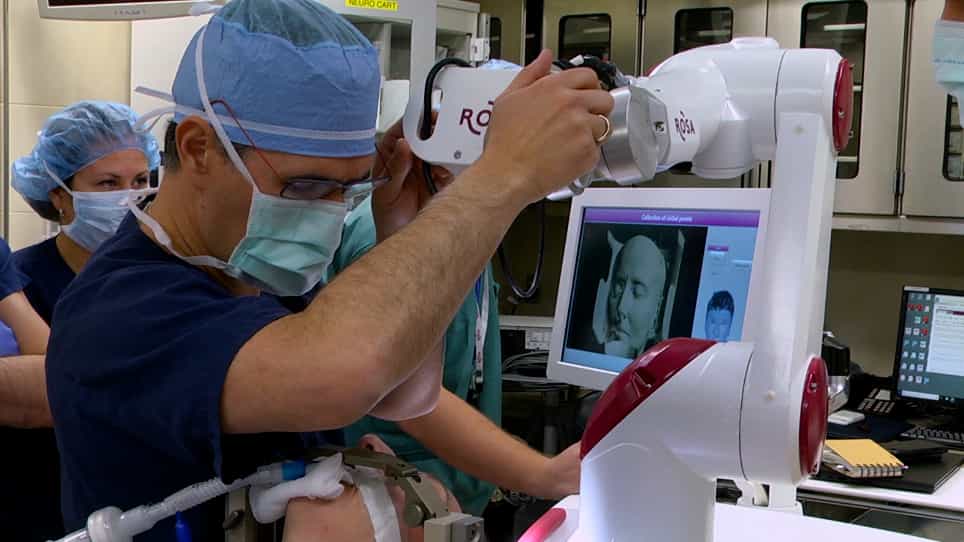

Operative Technique and Nuances for the Stereoelectroencephalographic SEEG Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023
Comparative Feasibility and Complication Analyses of Extraoperative (Bedside) Removal of
Jiahao J Chen, Thandar Aung1,2, Theodora Constantine3,4
1Department of Neurological Surgery, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania, USA, jic368@pitt.edu.

Introduction:
Stereotactic electroencephalography (SEEG) involves the implantation of intracortical electrodes for the precise localization of the epileptogenic zone and is well-established in terms of its safety and efficacy during implantation; however, there is a notable lack of research comparing different electrode removal techniques, specifically regarding complications and feasibility of these approaches. This study evaluates the feasibility and clinical utility of intraoperative versus extraoperative (bedside) removal of stereotactic electroencephalography (SEEG) electrodes.
Methods:
The early feasibility study retrospectively reviewed 117 consecutive SEEG patients at our institution, comparing 101 intraoperative cases with 16 extraoperative cases. A total of 1,624 SEEG electrodes were evaluated. Results related to demographics, feasibility of bedside removal, and occurrence of complications were analyzed and statistically compared between groups.
Results:
Our findings reveal comparable patient demographics across both groups and demonstrate low complication rates of 1.98% for intraoperative and 0.00% for extraoperative removals, with a combined rate of 1.71%. Importantly, zero cases of infection were observed in both settings. In addition to the low rates of complication in both the intraoperative and extraoperative explant groups, the study indicates a statistically significantly reduced use of sedation in the extraoperative group, which may enhance patient comfort and eliminate the need for additional sedatives during their ongoing treatment. The extraoperative bedside approach also offers practical benefits, such as removing the need for operating room (OR) resources and staffing, which can prevent OR delays and contribute to shorter hospital stays.
Conclusion:
With the appropriate indications, the extraoperative removal of SEEG electrodes appears to be a feasible and safe alternative to the intraoperative method. It presents potential advantages in optimizing patient flow within epilepsy monitoring units, improving operational efficiency, and potentially reducing healthcare costs while promoting patient comfort. Future research is essential to validate these findings further and refine the bedside technique for broader clinical application.
More Related Videos
 05:54
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
 13:32
Recording Human Electrocorticographic ECoG Signals for Neuroscientific Research and Real-time Functional Cortical Mapping
Published on: June 26, 2012