Related Experiment Video
Updated: Sep 8, 2026
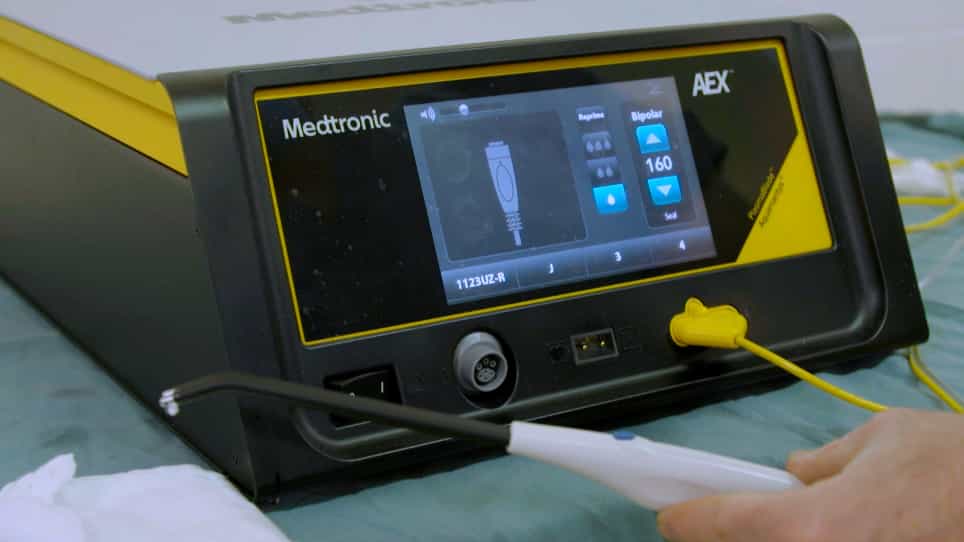

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Management of retroperitoneal haematoma following penetrating trauma

Experience with the management of 106 consecutive patients found to have a retroperitoneal haematoma (RH) at laparotomy for penetrating trauma over a 2-year period is reviewed. Three types of retroperitoneal haematoma are recognized: Type I (central), Type II (flank) and Type III (pelvic). Type I RH was present in 22 patients as a result of injuries to the inferior vena cava (9), the aorta (5), the pancreas and duodenum (5), the portal vein (2), and to both aorta and inferior vena cava (1). Fourteen patients died (63.8 per cent) representing 70 per cent of all deaths in the series. Type II RH was seen in 73 patients. Thirty-two were stable and the perinephric fascia was not opened with no morbidity or mortality. Forty-one were explored: 15 on pre-operative evidence of renal injury which was confirmed at laparotomy. In the remaining 26 a stable haematoma was explored and no significant lesion found. It is considered that in 45 of 73 Type II RH (61.0 per cent) exploration was unnecessary. Five patients died (6.8 per cent). Type III RH was found in 11 patients and was due to iliac vessel injuries. Two patients died. In conclusion Type I and III RH should be routinely explored. Stable Type II RH discovered at laparotomy should be explored selectively based on pre-operative clinical and radiological assessment of renal injury.
Experience with the management of 106 consecutive patients found to have a retroperitoneal haematoma (RH) at laparotomy for penetrating trauma over a 2-year period is reviewed. Three types of retroperitoneal haematoma are recognized: Type I (central), Type II (flank) and Type III (pelvic). Type I RH was present in 22 patients as a result of injuries to the inferior vena cava (9), the aorta (5), the pancreas and duodenum (5), the portal vein (2), and to both aorta and inferior vena cava (1). Fourteen patients died (63.8 per cent) representing 70 per cent of all deaths in the series. Type II RH was seen in 73 patients. Thirty-two were stable and the perinephric fascia was not opened with no morbidity or mortality. Forty-one were explored: 15 on pre-operative evidence of renal injury which was confirmed at laparotomy. In the remaining 26 a stable haematoma was explored and no significant lesion found. It is considered that in 45 of 73 Type II RH (61.0 per cent) exploration was unnecessary. Five patients died (6.8 per cent). Type III RH was found in 11 patients and was due to iliac vessel injuries. Two patients died. In conclusion Type I and III RH should be routinely explored. Stable Type II RH discovered at laparotomy should be explored selectively based on pre-operative clinical and radiological assessment of renal injury.


Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care