Related Experiment Video
Updated: May 10, 2025
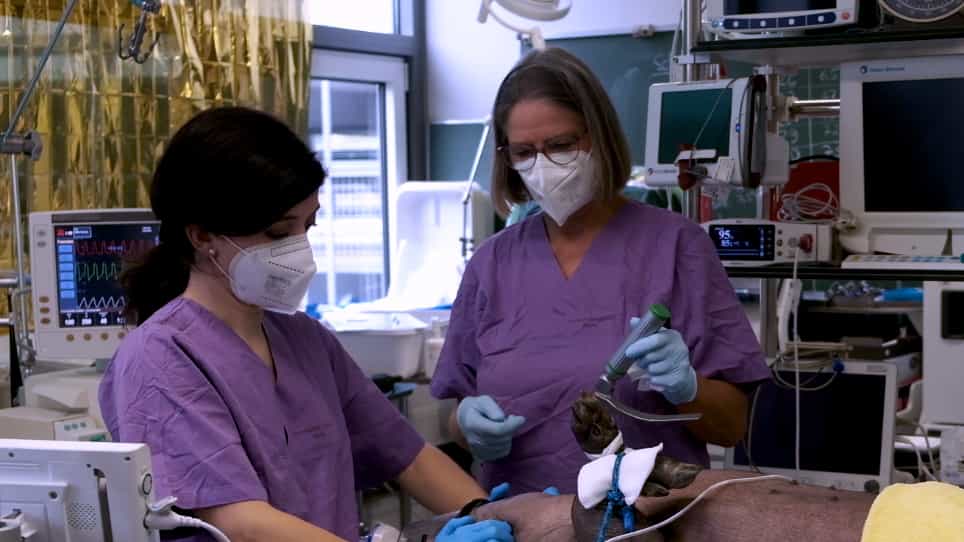

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
First-pass success rate and predictive factors for stylet use in videolaryngoscopic intubations with a Macintosh
Seung Eun Song1, Ji-Yoon Jung2, Chul-Woo Jung3
1Department of Anesthesiology and Pain Medicine, Jeju National University Hospital, Jeju National University College of Medicine, Jeju, Republic of Korea.

Purpose:
The aim of this study was to evaluate the first-pass success rate of videolaryngoscopic intubations without a stylet using a Macintosh blade and to identify predictive factors for successful intubation.
Methods:
We conducted a prospective observational study of 224 adult patients scheduled for elective videolaryngoscopic intubations using a Macintosh blade. We excluded patients who had cervical spine issues, airway disease, anticipated difficult intubation, or a body mass index > 35 kg·m-2, or who required rapid sequence induction. We initially attempted intubations without a stylet, with laryngeal manipulation on the second attempt if needed, and a stylet added after two failures. We evaluated the first-pass success rate and identified predictive factors using multivariable logistic regression, incorporating demographic, conventional, and ultrasonographic airway parameters. We performed ultrasound examination after induction of general anesthesia. We developed and evaluated a prediction model using receiver operating characteristic curve analysis.
Results:
The first-pass success rate was 80% (180/224), increasing to 96% (215/224) after laryngeal manipulation on the second attempt. Nine patients (4%) required a stylet. Longer sternomental distance (odds ratio [OR], 1.24; 95% confidence interval [CI], 1.01 to 1.53; P = 0.04) and increased thyromental height (OR, 1.14; 95% confidence interval [CI], 1.07 to 1.21; P < 0.001) were associated with first-pass success without a stylet. Limited (OR, 0.39; 95% CI, 0.16 to 1.00; P = 0.049) or severely limited (OR, 0.05; 95% CI, 0.01 to 0.19; P < 0.001) cervical spine movement negatively affected success.
Conclusions:
Routine stylet preparation for elective videolaryngoscopic intubations with a Macintosh blade may not be necessary, as only a small percentage of patients required it.


Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:23
Tracheostomy Suctioning II: Procedure