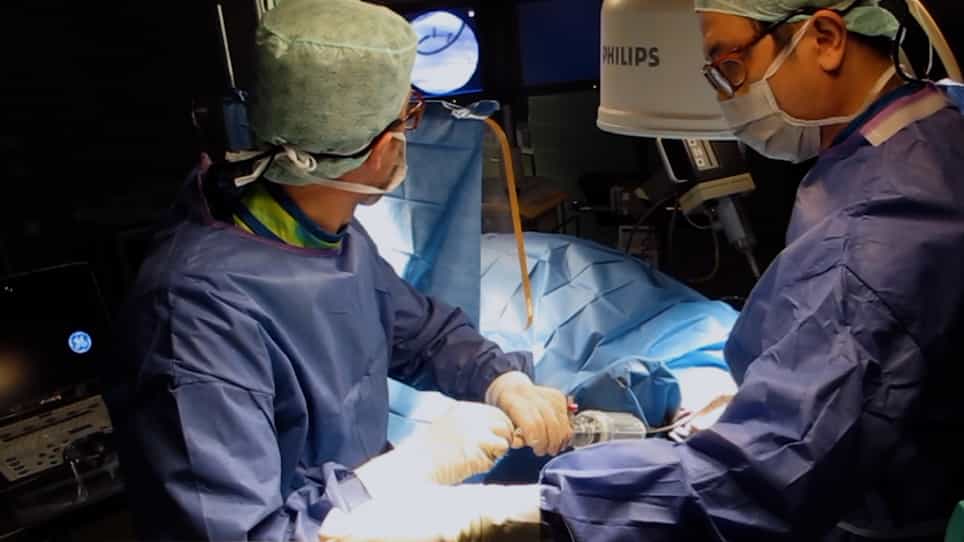
Related Experiment Video
Updated: May 6, 2026
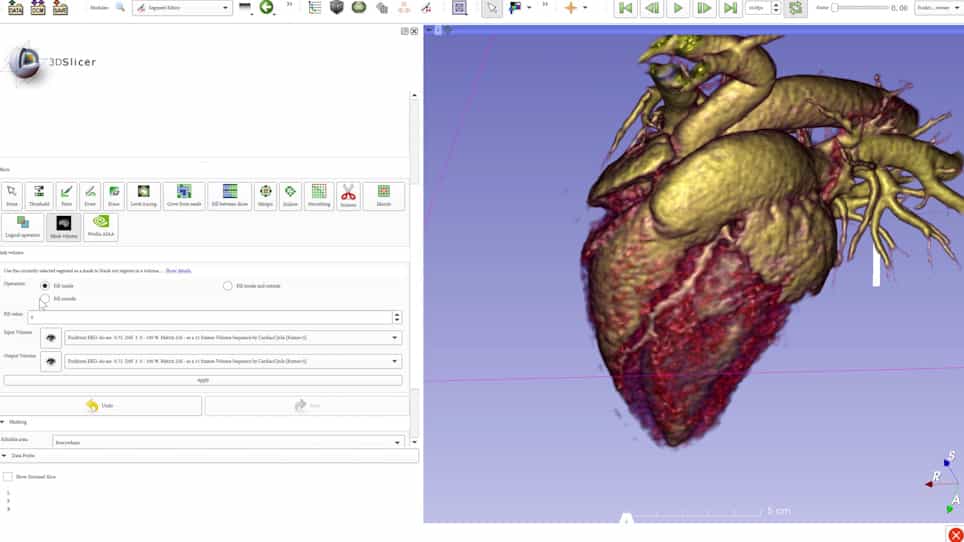

Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Comparative effectiveness and safety of self-expanding versus balloon-expandable transcatheter aortic valve
Montaser Elkholy1, Mohammad Akkawi1, George G Kidess2
1Wayne State University School of Medicine, Detroit Medical Center, Detroit, MI, USA.

Background:
Transcatheter aortic valve replacement (TAVR) is a safe alternative to surgical aortic valve replacement for patients with symptomatic severe aortic stenosis at increased surgical risk. However, comparative data on self-expanding valves (SEV) versus balloon-expanding valves (BEV) remain limited.
Methods:
A comprehensive review of PubMed and Embase was conducted through April 2024, identifying eight studies (five randomized controlled trials and three propensity-matched observational studies) comparing SEV and BEV in TAVR. Primary outcomes included all-cause mortality, cardiovascular mortality, and device success per Valve Academic Research Consortium criteria, while secondary outcomes assessed bioprosthetic valve dysfunction and adverse events (annulus rupture/dissection, coronary artery occlusion, valve dislocation/embolization, valve thrombosis, moderate and severe paravalvular aortic regurgitation, endocarditis, permanent pacemaker implantation, major or life-threatening bleeding, acute kidney injury, and stroke).
Results:
The analysis included 4032 patients (SEV = 2006; BEV = 2017). SEV was associated with higher rates of moderate-to-severe paravalvular aortic regurgitation [OR, 1.76; CI 1.13-2.74; P = 0.01] and permanent pacemaker placement [OR, 1.57; CI, 1.23-2.00; P = 0.0002] compared to BEV. No significant differences were observed in 30-day or 1-year all-cause mortality, cardiovascular mortality, device success, bioprosthetic valve dysfunction, valve dislocation/embolization, valve thrombosis, endocarditis, major or life-threatening bleeding, coronary artery occlusion, stroke, rehospitalization, or acute kidney injury.
Conclusions:
SEV and BEV demonstrated comparable outcomes in mortality and device success. However, the higher risk of moderate-to-severe paravalvular aortic regurgitation and permanent pacemaker placement with SEV should be considered when selecting the optimal TAVR valve for individual patients.