Magnetic Resonance Imaging at Second Surveillance Biopsy After Diagnosis in Patients With Grade Group 1 Prostate Cancer in the Canary Prostate Active Surveillance Study
Related Experiment Video For active surveillance
Updated: May 23, 2025

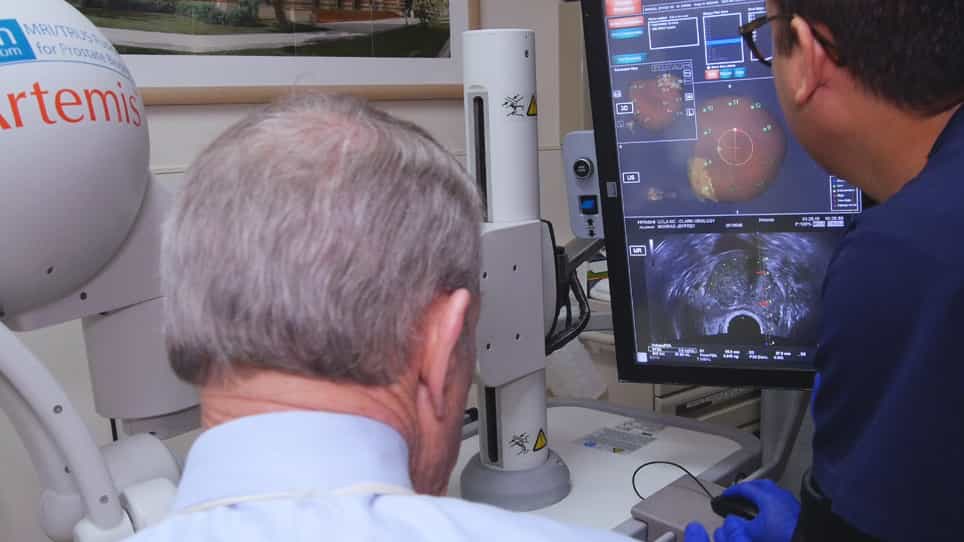
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Meera R Chappidi1, Lisa F Newcomb1,2, Yingye Zheng3
1Department of Urology, University of Washington, Seattle, Washington.

Purpose:
No clear guidelines exist regarding MRI use after confirmatory biopsy during active surveillance. Our objective was to evaluate MRI performance after confirmatory biopsy in patients with vs without prior MRI-informed biopsy.
Materials And Methods:
Patients in the Canary Prostate Active Surveillance Study with Gleason Grade Group (GG) 1 disease undergoing MRI-informed Biopsy 2, defined as second surveillance biopsy after diagnosis, were separated into prior vs no prior MRI-informed biopsy groups. Primary outcome was reclassification (≥GG2) at MRI-informed Biopsy 2. Reclassification rates and location (systematic cores, targeted cores, both) were compared between groups. Univariable and multivariable logistic regression identified predictors of reclassification.
Results:
Patients with (n = 101) vs without (n = 103) prior MRI-informed biopsy had lower reclassification rates at Biopsy 2 (21% vs 36%, P = .017) and lower GG at reclassification (95% vs 73% of reclassifications to GG2, P = .039). In multivariable modeling, Prostate Imaging Reporting and Data System 4 or 5 lesion at MRI-informed Biopsy 2 was associated with increased odds of reclassification (odds ratio = 2.04, 95% CI [1.04-4.05]). The negative predictive value of MRI at Biopsy 2 was 87% (95% CI [78-96]) and 73% (95% CI [61-85]) in with vs without prior MRI groups. Reclassification location was identified by targeted cores only in 36% vs 19% of patients with vs without prior MRI (P = .4). Reclassification location was identified by systematic cores only in 36% vs 58% of patients with vs without prior MRI (P = .4).
Conclusions:
These results support MRI use at Biopsy 2 and suggest negative surveillance MRI should not replace Biopsy 2. Both targeted and systematic cores should be taken at Biopsy 2 in patients with and without prior MRI on active surveillance.