Related Experiment Video
Updated: May 20, 2025
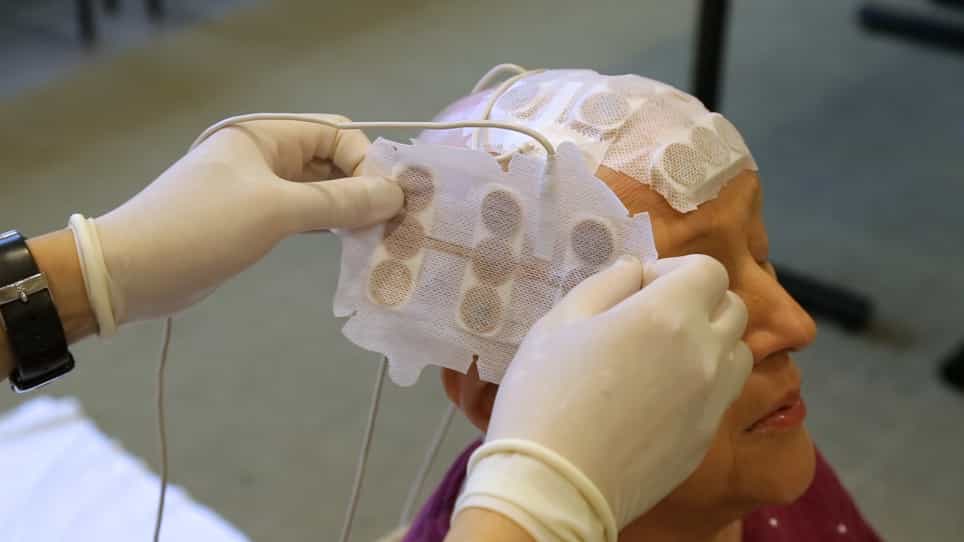
The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Surufatinib in advanced neuroendocrine tumours: Final overall survival from two randomised, double-blind,
Jianming Xu1, Lin Shen2, Jie Li2
1Department of Gastrointestinal Oncology, The Fifth Medical Center, Chinese PLA General Hospital, Beijing, China.

Background:
SANET-ep (NCT02588170) and SANET-p (NCT02589821) demonstrated the efficacy and safety of surufatinib versus placebo in patients with advanced extra-pancreatic and pancreatic neuroendocrine tumours (NETs). Here, we present a pooled analysis of final overall survival (OS) from two randomised phase 3 studies.
Methods:
The SANET studies were randomised, placebo-controlled, double-blind, phase 3 studies in China, comparing the efficacy and safety of oral 300-mg surufatinib (n = 265) versus placebo (n = 133) in patients with unresectable/metastatic, well-differentiated NETs (grade 1/2). After progression of disease or study unblinding, patients receiving placebo crossed over/switched to open-label surufatinib. By pooling the data from the two studies, OS analysis was completed using Kaplan-Meier methodology and a Cox proportional hazards model in the intention-to-treat population. Exploratory analyses were performed using different models to correct the confounding effect introduced by crossover. Long-term safety was assessed.
Results:
At study termination, 69 % of the placebo group had crossed over/switched to surufatinib. Median OS was 50.1 versus 46.8 months for patients initially on surufatinib versus those initially on placebo (stratified hazard ratio [HR] 0.935, 95 % confidence interval [CI] 0.684-1.278; p = 0.6727). After correcting the confounding effect introduced by crossover/switching, the HR ranged from 0.558 to 0.825. Commonly (≥10 %) reported treatment-related adverse events (grade 3/4) included hypertension and proteinuria.
Conclusion:
OS of patients initially on surufatinib was not significantly longer versus patients initially on placebo, likely due to the high amount of crossover from placebo to surufatinib. No new safety signals were observed.
Clinical Trials Registration:
SANET-ep (NCT02588170) and SANET-p (NCT02589821).
Insights
Pooled analysis of SANET-ep and SANET-p trials found surufatinib did not significantly improve overall survival (OS) in neuroendocrine tumors (NETs) due to high placebo crossover rates. No new safety concerns were identified.
Area of Science:
- Oncology
- Clinical Pharmacology
Background:
- The SANET-ep and SANET-p trials evaluated surufatinib efficacy and safety in advanced neuroendocrine tumors (NETs).
- This analysis pools data from these two phase 3 studies to report final overall survival (OS) outcomes.
Purpose of the Study:
- To present a pooled analysis of final overall survival (OS) data from the SANET-ep and SANET-p randomized phase 3 studies.
- To evaluate the efficacy and safety of surufatinib compared to placebo in patients with advanced unresectable/metastatic well-differentiated NETs (grade 1/2).
Main Methods:
- Two randomized, placebo-controlled, double-blind phase 3 studies (SANET-ep and SANET-p) were conducted in China.
- Patients received either oral surufatinib (300 mg) or placebo. Crossover from placebo to open-label surufatinib was permitted upon disease progression or unblinding.
- Overall survival (OS) was analyzed using Kaplan-Meier methodology and Cox proportional hazards models in the intention-to-treat population, with exploratory analyses to adjust for crossover effects.
Main Results:
- A significant proportion (69%) of patients in the placebo arm crossed over to surufatinib.
- Median OS was 50.1 months for the surufatinib group versus 46.8 months for the placebo group (stratified HR 0.935, p=0.6727).
- After adjusting for crossover, the hazard ratio for OS ranged from 0.558 to 0.825, suggesting a potential benefit. Common grade 3/4 treatment-related adverse events included hypertension and proteinuria.
Conclusions:
- Overall survival was not significantly different between initial surufatinib and placebo groups, likely influenced by high crossover rates.
- No new safety signals were identified with surufatinib treatment.
- Exploratory analyses suggest a potential survival benefit of surufatinib after adjusting for crossover effects.
More Related Videos
 06:08
Establishment and Characterization of Patient-Derived Xenograft Models of Anaplastic Thyroid Carcinoma and Head and Neck Squamous Cell Carcinoma
Published on: June 2, 2023
 06:15
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
