Related Experiment Video
Updated: May 12, 2026
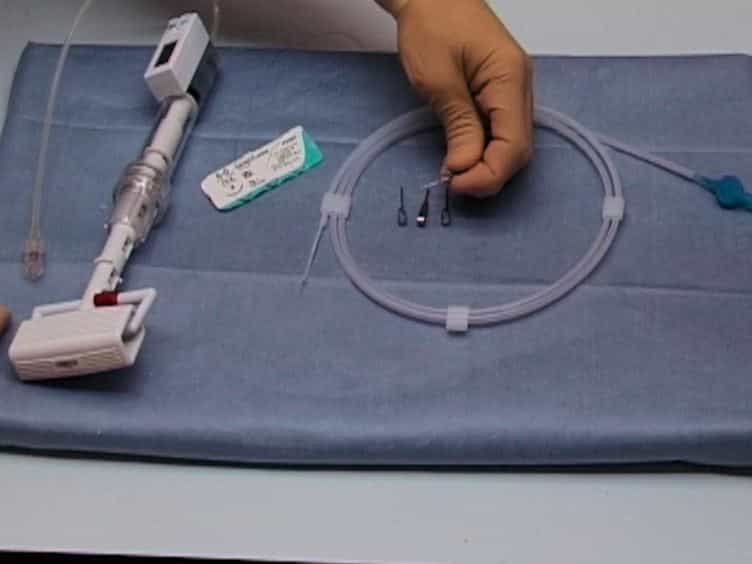
A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Infrarenal and juxtarenal abdominal aortic aneurysm repair in young patients
Giulia Bertagna1, Maciej Juszczak2, Massimo Vezzosi2
1Department of Vascular Surgery, University Hospitals Birmingham NHS Foundation Trust, Birmingham, UK; Vascular Surgery Unit, Department of Translational Research and New Technologies in Medicine and Surgery, University of Pisa, Pisa, Italy.

Insights
Open surgical repair (OSR) and endovascular repair (EVAR) show excellent outcomes for younger patients with abdominal aortic aneurysms (AAA). Both methods offer high survival and freedom from reintervention in this demographic.
Area of Science:
- Vascular Surgery
- Aortic Aneurysm Repair
- Minimally Invasive Procedures
Background:
- Younger patients (<70 years) with infrarenal (IR) and juxtarenal (JR) abdominal aortic aneurysms (AAA) require effective treatment options.
- Comparing open surgical repair (OSR) and endovascular repair (EVAR) is crucial for optimizing outcomes in this specific age group.
Purpose of the Study:
- To evaluate and compare the early and mid-term outcomes of OSR and EVAR for primary IR and JR AAA in patients under 70 years of age.
- To assess 30-day mortality, survival rates, and freedom from reintervention for both repair modalities.
Main Methods:
- Retrospective analysis of consecutive patients (<70 years) undergoing OSR or EVAR for IR/JR AAA between 2010-2021.
- Primary endpoint: 30-day mortality. Secondary endpoints: survival and freedom from reintervention.
- Data presented as median (IQR); P < .05 considered significant.
Main Results:
- 230 patients included (median age 65); 133 IRAAA, 97 JRAAA. EVAR patients had higher prevalence of coronary artery disease (48% vs 23%).
- 30-day mortality was low (0.9%). Major nonfatal complications were similar (2.4% OSR vs 3.4% EVAR).
- EVAR demonstrated significantly shorter critical care and hospital stays (P < .001). 5-year survival (89%) and freedom from reintervention (88%) were comparable between OSR and EVAR (P = .53).
Conclusions:
- Endovascular repair (EVAR), including fenestrated EVAR, and open surgical repair (OSR) are associated with excellent early and mid-term outcomes.
- These repair methods are suitable for appropriately selected younger patients presenting with infrarenal and juxtarenal abdominal aortic aneurysms.
- The study highlights the effectiveness of both OSR and EVAR in younger AAA patients, with EVAR offering advantages in reduced hospital stay.
Objective:
To report the outcome of elective open surgical repair (OSR) and endovascular repair (EVAR) of primary infrarenal (IR) and juxtarenal (JR) abdominal aortic aneurysms (AAA) in patients <70 years of age.
Methods:
Single-center retrospective study of consecutive patients <70 years old with primary IRAAA and JRAAA treated by OSR and EVAR between January 2010 and December 2021. The primary end point was 30-day mortality. Secondary end points were survival and freedom from reintervention. Data are presented as median (interquartile range [IQR]). A P value of <.05 was considered significant.
Results:
We included 230 patients (214 men; median age 65 years; range, 64-67 years) who underwent repair of IRAAA (n = 133; 53 OSR, 80 EVAR) and JRAAA (n = 97; 30 OSR, 67 fenestrated EVAR). Coronary artery disease was more prevalent in EVAR patients (48% vs OSR, 23%; P < .001) and those with JRAAA (51% vs IRAAA: 31%; P = .003). The 30-day mortality rate was 0.9% (n = 2). Major nonfatal complications occurred in 2.4% of patients (2/83) after OSR and 3.4% (5/147) after EVAR: myocardial infarction (n = 1; OSR), temporary renal replacement therapy (n = 1; OSR), respiratory failure requiring prolonged ventilation (n = 2; EVAR), and reoperation (n = 5; OSR 2 vs EVAR 3). The median critical care and total hospital stay was as follows: OSR 2 days (IQR, 1-2 days) and 6 days (IQR, 4-7 days); EVAR 1 day (IQR, 0-1 day) and 2 days (IQR, 1-3 days) (P < .001). The median follow-up was 90 months (IQR, 59-121 months). Estimated 5-year survival (± standard error) and freedom from late reintervention were 89% ± 2% and 88% ± 2%, respectively, with no difference related to modality of repair (P = .53) or aneurysm extent (P = .25).
Conclusions:
IR EVAR, fenestrated EVAR, and OSR are associated with excellent early and mid-term outcomes in appropriately selected younger patients with IR and JR AAA.

Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management