Related Experiment Video
Updated: Jun 19, 2026
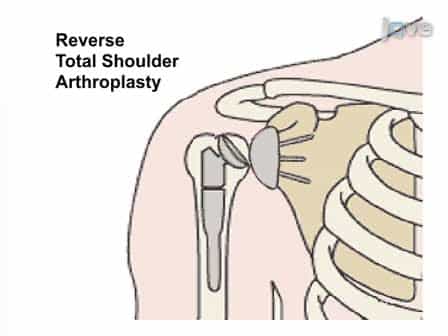

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Arthroscopic Double-Row Rotator Cuff Repair With Box Configuration
Soheil Sabzevari1, Ryan Murray2, Shaquille Charles1
1Department of Orthopaedic Surgery, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania, USA.

Background:
Arthroscopic transosseous-equivalent (TOE) techniques may offer additional advantages, including a more efficient surgery with a self-reinforcing construct with equivalent clinical results to medial knotted TOE repair for rotator cuff tears (RCTs).
Indications:
An arthroscopic knotless double-row (DR) rotator cuff repair (RCR) using FiberTak RC anchors for medial row fixation with box configuration may be an appropriate construct for operatively indicated small-to-moderate full-thickness RCTs.
Technique:
Our modified technique uses TOE repair principles to address RCTs too small for traditional 4.75-mm anchors using medial row fixation and too large to apply a single medial to lateral anchor repair. The patient is placed in a beach chair position. In addition to standard anterior and posterior portals, a lower lateral working portal and a higher posterolateral viewing portal are made. Subsequent to supraspinatus footprint visualization/preparation, two 2.6-mm FiberTak RC anchors each loaded with 1 LabralTape and 1 FiberWire are placed medially. The 4 sets of sutures for one anchor are placed through the rotator cuff tendon together in 1 spot and the process is repeated for the second anchor. One FiberWire from each anchor is then tied extracorporeally and then a double pulley technique is used to compress the medial aspect of the repair at the footprint in a box configuration. Finally, 1 limb of LabralTape from each of the medial anchors along with the corresponding FiberWire is secured through 2 lateral-row 4.75-mm anchors anteriorly and posteriorly to restore the lateral footprint and secure the rotator cuff in TOE box configuration. This modified technique can provide anatomical compression of the rotator cuff tendon at the footprint with additional medial compression achieved by the box configuration while taking advantage of knotless fixation.
Results:
Postoperatively, a sling is worn for 4 weeks, passive range of motion (ROM) is initiated at 2 weeks, active ROM is begun at 6 weeks, and strengthening at 3 months. Patients may return to full unrestricted activities around 5 to 6 months.
Discussion/Conclusion:
A modified arthroscopic DR RCR with box configuration is an excellent treatment option for patients with small-to-moderate full-thickness RCT who fail conservative treatment.
Patient Consent Disclosure Statement:
The author(s) attests that consent has been obtained from any patient(s) appearing in this publication. If the individual may be identifiable, the author(s) has included a statement of release or other written form of approval from the patient(s) with this submission for publication.

Related Concept Videos
 01:36
Mismatch Repair
 02:50
Spindle Assembly
In most cells, centrosomes are the primary microtubule nucleation centers. In the centrosome-mediated pathway, the G2-prophase transition triggers centrosome maturation and increased microtubule nucleation. Progressive nucleation results in a microtubule array...
 01:20
Mismatch Repair
The Mutator Protein Family Plays a Key Role in DNA Mismatch Repair
The human genome has more than 3 billion base pairs of DNA per cell. Prior to cell division, that vast amount of genetic...
02:50Spindle Assembly
In most cells, centrosomes are the primary microtubule nucleation centers. In the centrosome-mediated pathway, the G2-prophase transition triggers centrosome maturation and increased microtubule nucleation. Progressive nucleation results in a microtubule array...
 01:09
Transmission Shafts: Problem Solving
Next, use bending moment diagrams for the shaft to...
 01:22
Controller Configurations
Control-system compensation involves various configurations, most commonly series or cascade compensation, in which the controller aligns...