

Use of Intravascular Ultrasound during Peripheral Vascular Interventions for Claudication Is Not Associated with
Chen Dun1, M Libby Weaver2, Sanuja Bose3
1Department of Biomedical Informatics and Data Science, The Johns Hopkins University School of Medicine, Baltimore, MD; Department of Surgery, The Johns Hopkins University School of Medicine, Baltimore, MD.

Background:
The efficacy of intravascular ultrasound (IVUS) for improving outcomes of peripheral vascular interventions (PVIs) has not been well studied. We aimed to evaluate the association of IVUS with long-term outcomes in patients undergoing PVI for claudication.
Methods:
We conducted a two-cohort study using data from 100% of Medicare fee-for-service claims (2018-2022) and the Vascular Quality Initiative Vascular Implant Surveillance and Interventional Outcomes Network (VISION; 2016-2019). For both cohorts, we identified all patients who underwent an index (first-time) femoropopliteal PVI for claudication, excluding patients with chronic limb-threatening ischemia (CLTI) and acute limb ischemia. We compared IVUS use over time and by procedure type and setting. We used multivariable Cox proportional hazards models to assess the associations of IVUS with repeat PVI, conversion to CLTI, and amputation. For the Medicare cohort, adjustments were made for baseline patient characteristics, while for the VISION cohort, additional adjustments were made for detailed anatomic factors. All models were clustered by physician.
Results:
In the Medicare dataset, 69,092 patients (median age 74 years; 40.5% female; 12.1% non-Hispanic Black) underwent an index femoropopliteal PVI for claudication, of whom 22.1% (N = 15,253) received IVUS. In the VISION dataset, 6,722 patients (median age 72 years; 38.7% female; 11.6% non-Hispanic Black) underwent an index femoropopliteal PVI for claudication, of whom 3.8% (N = 254) received IVUS. The mean follow-up time for both cohorts was 2.7 years. For both the Medicare and VISION cohorts, IVUS use significantly increased over time, particularly in ambulatory surgery center/office-based laboratory settings and in conjunction with atherectomy procedures (P < 0.001). In the Medicare cohort, IVUS use was associated with a higher hazard of repeat PVI (adjusted hazard ratio [aHR] 1.07, 95% CI 1.02-1.12) and progression to CLTI (aHR 1.11, 95% CI 1.03-1.20) after adjustment compared to PVI without IVUS. In the VISION cohort, there were no significant differences in outcomes between IVUS and non-IVUS cases (all, P > 0.05).
Conclusion:
The use of IVUS for the treatment of claudication is rapidly increasing, without clear benefits in outcomes. The role of IVUS in treating claudication deserves further investigation.
More Related Videos
 14:52
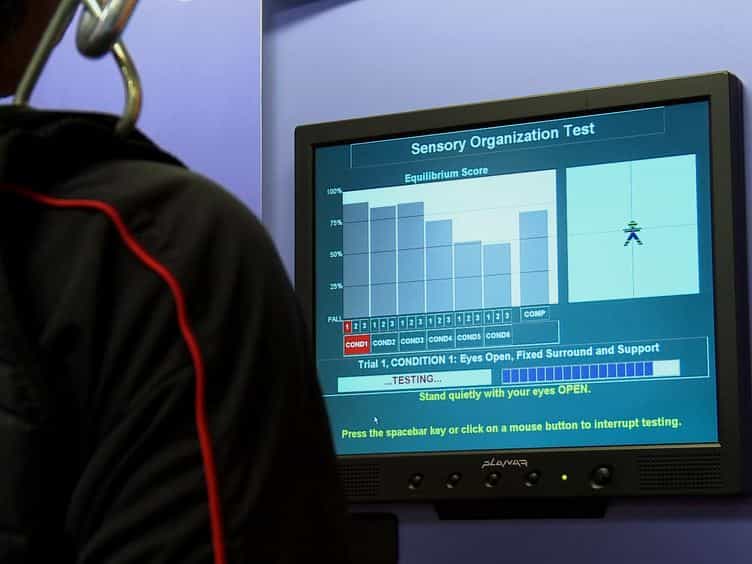
Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
 10:50
Osmotic Drug Delivery to Ischemic Hindlimbs and Perfusion of Vasculature with Microfil for Micro-Computed Tomography Imaging
Published on: June 29, 2013
Related Concept Videos
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:17
Ultrasonography
During an ultrasonography procedure, a handheld device called...