Related Experiment Video
Updated: May 11, 2026
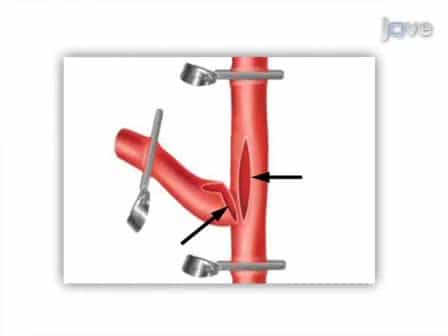
Microsurgical Venous Pouch Arterial-Bifurcation Aneurysms in the Rabbit Model: Technical Aspects
Published on: May 11, 2011
Risk factors for recanalization after coil embolization for cerebral aneurysms: importance of the first coil and
Ken Aoki1, Hiroyasu Nagashima1, Yuichi Murayama2
1Department of Neurosurgery, Katsushika Medical Center, The Jikei University School of Medicine, Tokyo, Japan.

Background:
Endovascular coil embolization for cerebral aneurysms is a well-established treatment; however, postoperative recanalization remains a risk. This study aimed to clarify risk factors for cerebral aneurysm recanalization after coil embolization and to develop a predictive model for assessing risks.
Methods:
This retrospective study included patients with cerebral saccular aneurysms who underwent initial coil embolization at our hospital in Tokyo, Japan between 2012 and 2023. The following cases were excluded: follow-up of <1 year, re-treatment and use of bioactive coils. Outcomes included aneurysm characteristics and postoperative Raymond-Roy Occlusion Classification (RROC). Univariate and multivariate Cox proportional hazards models were used to identify independent predictors. A simplified risk score was constructed using LASSO logistic regression and β-coefficients from multivariable analysis. Internal validity was assessed by bootstrap resampling. External validation was performed using an independent cohort and model performance was evaluated in terms of discrimination and calibration.
Results:
Among the 150 patients with aneurysms, 79 were analyzed after applying exclusion criteria. Multivariate analysis identified four independent predictors of recanalization: rupture status, aneurysm size ≥7 mm, RROC without class I, and first volume embolization ratio <8 %. These variables were incorporated into an integer-based risk score ranging from 0 to 7. The model demonstrated strong discrimination in the internal validation cohort (C-statistic: 0.89), which remained acceptable in the external validation cohort (C-statistic: 0.81, 95 % CI: 0.74-0.89). Risk stratification showed increasing recanalization rates of 1.8 %, 13.5 %, and 41.5 % in low- (0-2), intermediate- (3-4), and high-risk (5-7) groups, respectively. Calibration in the external cohort showed slight overestimation of risk in high-score patients.
Conclusion:
This study identified four significant risk factors for recanalization after coil embolization and proposed a practical, externally validated risk score. The model provides clinically relevant risk stratification and may support individualized follow-up strategies.