Related Experiment Video
Updated: May 9, 2025
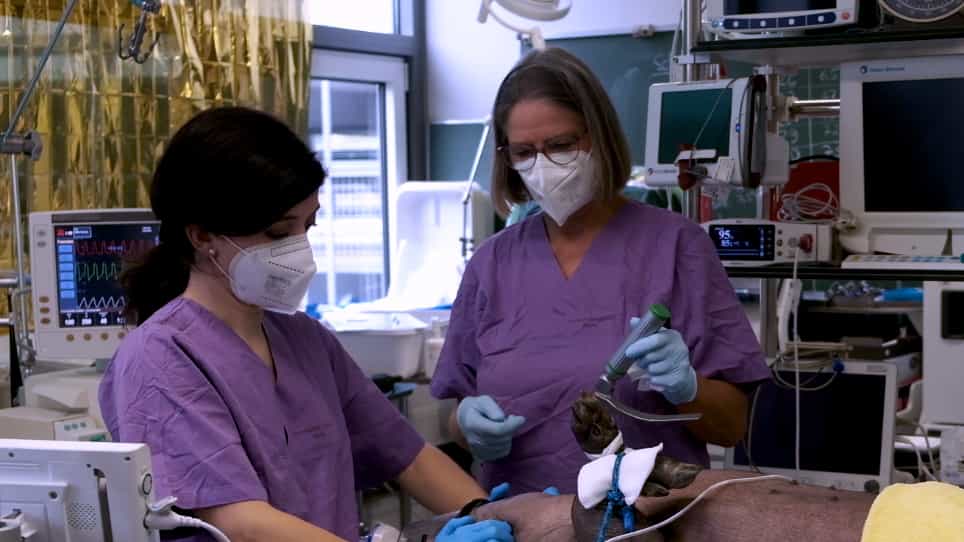

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Performance characteristics and complications of an Inter-Changeable Operator Model for intubation in an Australian
Alan A Garner1,2,3,4, Andrew Scognamiglio5, Anna Lee6
1Nepean Clinical School, University of Sydney, Sydney, New South Wales, Australia.

Objective:
The Inter-Changeable Operator Model (ICOM) enables paramedics and flight nurses to perform intubations interchangeably with team physicians in prehospital critical care. However, literature on ICOM characteristics and performance is limited.
Methods:
We conducted a retrospective, observational study of an ICOM operating within an Australian Helicopter Emergency Medical Service over a nine-year period. First pass success, major complication rates and clinically important time intervals were compared between first intubator groups.
Results:
A total of 413 patients met the inclusion criteria, with paramedics performing the majority of first intubation attempts (379/413, 91.8%). Physicians primarily conducted second intubation attempts and managed high-risk patients. In unadjusted analysis, the risk of major complication in the paramedic/supervised registrar group was not lower than the most senior physician intubator group (relative risk [RR] 0.59, 95% confidence interval [CI]: 0.26-1.32; P = 0.198) and after adjustment the risk was also not lower (RR 0.60, 95% CI: 0.24-1.54; P = 0.289). First pass failure occurred in 12 (3.1%) and 1 (4.8%) patients intubated by paramedic/supervised registrar and most senior physician groups, respectively (P = 0.498). The median (95% CI) adjusted difference in contact to intubation time between paramedic/supervised registrar first intubator and most senior physician groups was -2 min (-7 to 3; P = 0.392). Total adjusted scene time was also not significantly different between groups (median difference 2 min, 95% CI: -3 to 7; P = 0.500).
Conclusions:
Paramedics conducting most intubations within an ICOM are both safe and efficient. Larger studies are required to examine differences between physician subgroups.


Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....