Related Experiment Video
Updated: May 8, 2025
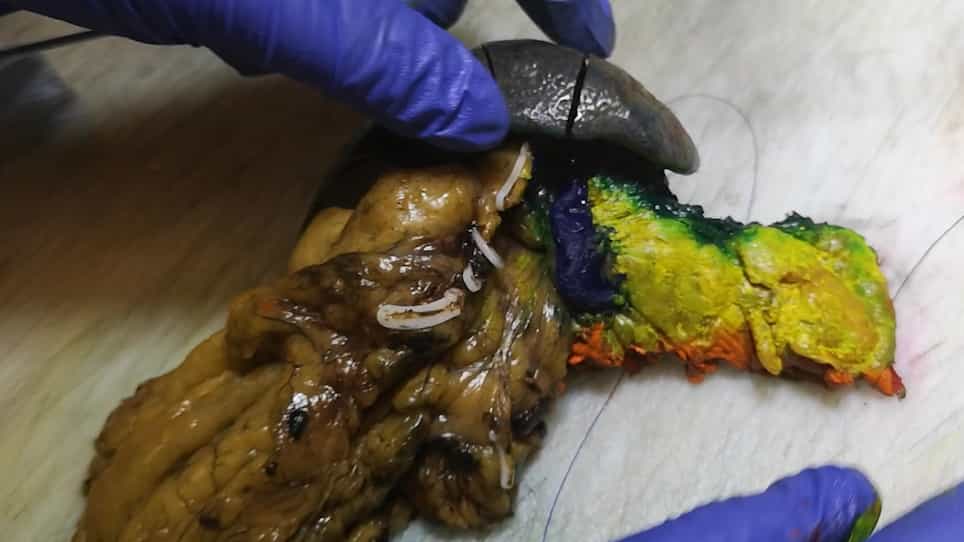

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Applicability of current nodal staging system for resected pancreatic cancer after neoadjuvant therapy: a
Woohyung Lee1, Jeein Park2, Aram Shin1
1Division of Hepatobiliary and Pancreatic Surgery, Department of Surgery, Asan Medical Center, Brain Korea 21 Project, University of Ulsan College of Medicine, Seoul, Republic of Korea.

Background:
The prognostic value of nodal staging in patients undergoing surgery for borderline resectable (BRPC) and locally advanced pancreatic cancer (LAPC) remains unclear. This study evaluated a novel system based on metastatic lymph nodes (nMLN).
Methods:
Patients who underwent surgery were categorized into upfront surgery (UP) and neoadjuvant chemotherapy (NAT) groups. In the NAT group, the nMLN system was developed using K-adaptive partitioning, classifying patients by the number of metastatic lymph nodes (nMLN0: 0; nMLN1: 1-4; nMLN2: ≥5). Prognostic performance was compared between the nMLN and AJCC 8th edition systems using time-dependent area under the curve (AUC) analyses.
Results:
A total of 730 UP and 347 NAT patients were included. Compared to the UP group, the NAT group had fewer N1 cases (P = 0.032) and less lymphovascular invasion (P < 0.001). The nMLN system significantly stratified overall survival (OS) and recurrence-free survival (RFS) in NAT (P < 0.001) and UP groups (P < 0.001). Prognostic performance was comparable between the nMLN and AJCC 8th systems for OS (AUC: 0.628 vs. 0.629) and RFS (AUC: 0.643 vs. 0.649).
Conclusion:
Both the nMLN and AJCC 8th staging systems provide effective prognostic stratification and are applicable in NAT and UP settings.