Related Experiment Video
Updated: May 12, 2025
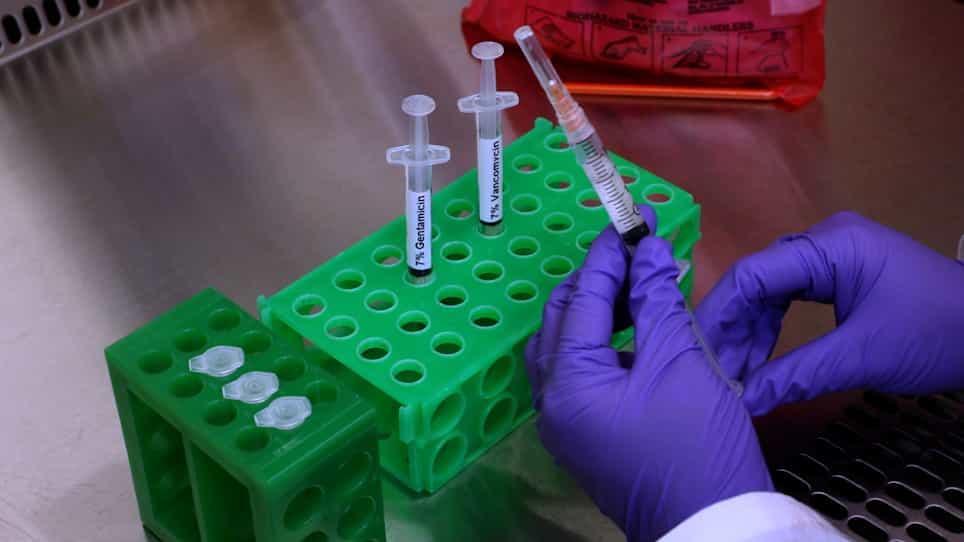

A Novel Method to Determine the Longitudinal Antibacterial Activity of Drug-Eluting Materials
Published on: March 3, 2023
Rethinking antibiotic prophylaxis in orthopaedic oncology: insights from a cohort study of endoprosthetic infections
Tariq Azamgarhi1,1, Craig Gerrand2,2, Simon Warren3,3
1Pharmacy Department, Royal National Orthopaedic Hospital NHS Trust, Brockley Hill, Stanmore, HA7 4LP, UK.

Abstract:
Introduction: Endoprosthetic replacement (EPR) is the preferred limb salvage method for musculoskeletal tumours involving bone; however, infection rates range from 8 % to 12 %. We investigated the impact of antibiotic prophylaxis at primary implantation on the development of prosthetic joint infection (PJI). Methods: We conducted a retrospective analysis of patients who underwent primary EPRs between 2010 and 2021. Prosthetic joint infections were identified and classified according to criteria from the European Bone and Joint Infection Society (EBJIS). The follow-up period extended until an infection was identified, subsequent surgery for non-infectious reasons occurred or the last known follow-up was conducted. For all primary procedures, we collected details of postoperative complications at the surgical site, including superficial wound infections, delayed wound healing and wound dehiscence. PJIs were divided into two groups. The first group included patients with an uncomplicated postoperative course, while the second comprised those with either postoperative wound problems or infections from an identifiable source. Results: Out of 1064 patients, 73 (6.9 %) developed PJI within a median follow-up of 25.6 months (IQR 8.8-52.7). A total of 26 % of PJIs were attributed to primary implantation, while 74 % of PJIs were due to secondary causes, with 47 % having wound complications and 27 % presenting acutely. The microbiological profiles between groups differed significantly, with infections from skin flora related to primary implantation and a high proportion of other bacteria (Gram-negatives and enterococci) linked to secondary infections. Conclusions: Skin flora are likely responsible for infections related to the primary procedure, and antibiotic prophylaxis should be optimised accordingly. Additional measures are needed to prevent secondary infections.
More Related Videos

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:23
Hand hygiene
Hand washing...
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 00:57
Antibiotic Selection