Related Experiment Video
Updated: May 12, 2025
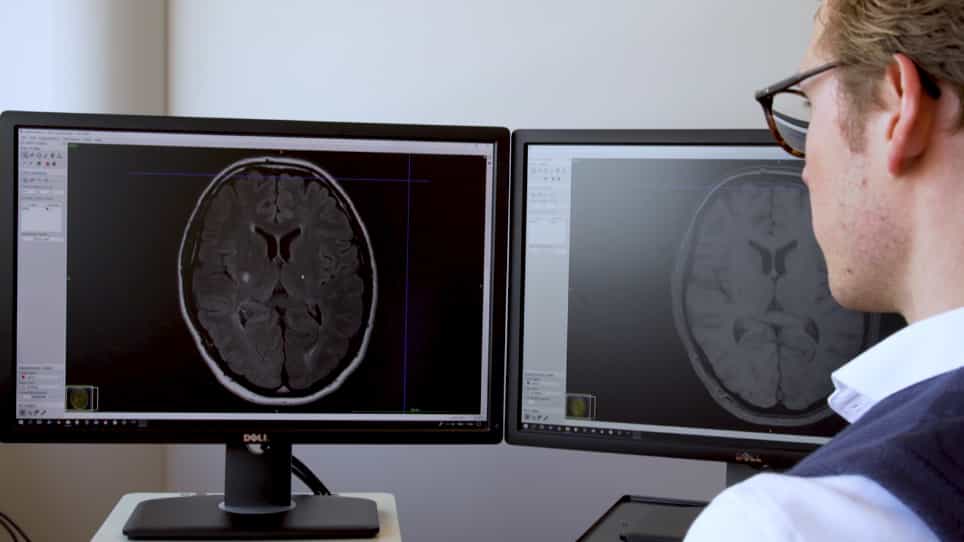

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Atherogenic and Inflammatory Markers in Recent Small Subcortical Infarcts: Associations with Location, Morphology,
Chaojuan Huang1, Jie Geng1,2, Jie Fan1,3
1Department of Neurology, The First Affiliated Hospital of Anhui Medical University, Hefei, Anhui, 230022, People's Republic of China.

Background:
Recent small subcortical infarcts (RSSIs) have emerged as a growing public health concern due to their poor long-term clinical outcomes. This study aimed to investigate the associations between the atherogenic index of plasma (AIP), systemic immune-inflammation index (SII), and systemic inflammation response index (SIRI) with the occurrence and recurrence of RSSIs.
Methods:
Three hundred forty-two patients with RSSIs who met the eligibility criteria were included in the cross-sectional analysis. Comprehensive demographic, laboratory, and neuroimaging data were collected at baseline. Patients were categorized into subcortical white matter, basal ganglia, and brainstem RSSIs based on lesion location. Lesions were further classified by shape (round/oval or tubular) and diameter (≤15 mm or >15 mm). Of these, 336 patients completed follow-up at six months. Logistic regression models were established to assess the relationships between AIP, SII, and SIRI with the occurrence and recurrence of RSSIs, considering variations in lesion location and morphology. The short-term prognostic performances of individual and combined risk factors were evaluated using receiver operating characteristic curve analysis.
Results:
Cross-sectional analysis revealed a significant positive correlation between AIP and basal ganglia RSSIs (OR: 3.269, 95% CI: 1.209-8.839), as well as between SIRI and brainstem RSSIs (OR: 1.472, 95% CI: 1.012-2.143) and tubular RSSIs (OR: 1.440, 95% CI: 1.043-1.989), after adjusting for potential confounders. In the longitudinal analysis, multivariate regression indicated that hypertension, periventricular white matter hyperintensities, and SII were independently associated with RSSI recurrence. The predictive model demonstrated strong performance, with an area under the curve of 0.853 (95% CI: 0.738-0.968), sensitivity of 90.9%, and specificity of 75.4%.
Conclusion:
Atherogenic and inflammatory markers are associated with specific locations and morphologies of RSSIs and serve as potential predictive factors for short-term RSSI recurrence. These findings may enhance our understanding of the mechanisms underlying RSSIs and inform early prevention strategies.


