

SEX AND RACE/ETHNICITY DIFFERENCES ON IN-HOSPITAL OUTCOMES IN OCTOGENARIANS WITH CARDIOGENIC SHOCK
Carlos Diaz-Arocutipa1, Rafael Salguero-Bodes, Elena Puerto
1Unidad de Revisiones Sistemáticas y Meta-análisis (URSIGET), Vicerrectorado de Investigación, Universidad San Ignacio de Loyola, Lima, Peru.

Abstract:
Background: Cardiogenic shock carries a high mortality rate, particularly among octogenarians. Our aim was to evaluate the clinical characteristics, management, and in-hospital outcomes among octogenarians, with a particular focus on sex and race/ethnicity differences. Methods: Retrospective cohort study using the National Inpatient Sample (NIS) including patients ≥80 years old hospitalized with cardiogenic shock from 2016 to 2019. Patients were stratified by sex and race/ethnicity (White, Black, Hispanic). Logistic regression was used to estimate odds ratios (OR) with their 95% confidence interval (CI). Results: Among 110,610 patients, in-hospital mortality was 44.6%, with significant differences by sex and race/ethnicity ( P = 0.013). Mortality was highest in White females (46.0%) and Black females (46.1%), while Hispanic males had the lowest rate (43.1%). After adjustment, White females had a higher mortality risk compared to White males (OR 1.07, 95% CI 1.01-1.14, P = 0.022). Black and Hispanic patients had lower utilization of intra-aortic balloon pumps and percutaneous ventricular assist devices ( P < 0.001), but experienced higher rates of major bleeding (Black males 8.0%, Black females 7.2%) and renal replacement therapy (Black males 8.4%, Black females 8.6%) ( P < 0.001). Hispanic males had the highest total hospital charges (median $133,115), while Black females had the lowest (median $77,006) ( P < 0.001). Conclusions: Significant sex and race/ethnicity differences exist in outcomes among octogenarians with cardiogenic shock. White females had the highest mortality, while Black and Hispanic patients had lower utilization of advanced therapies but higher complication rates. Addressing these differences is essential to improve equity in cardiovascular care.
More Related Videos


Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
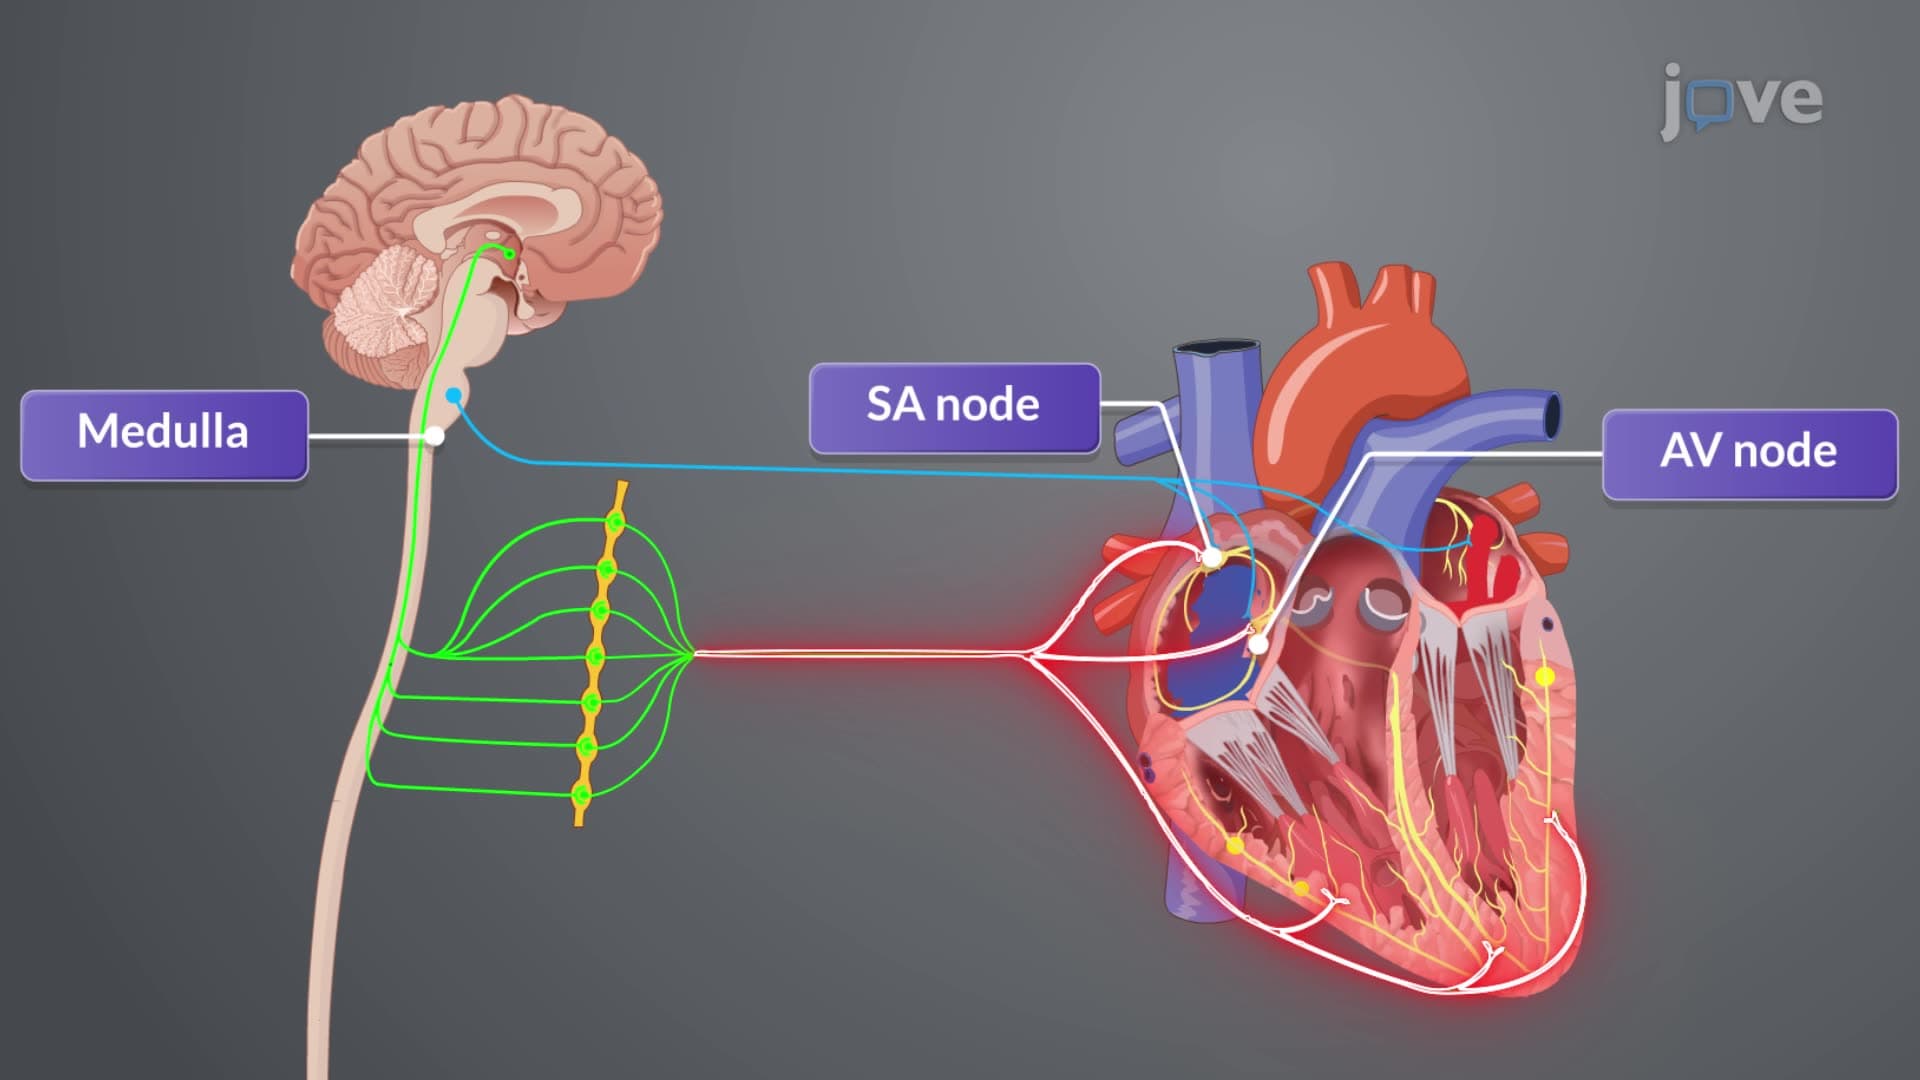
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
Pathophysiology of Cardiac Performance