Related Experiment Video
Updated: May 14, 2025


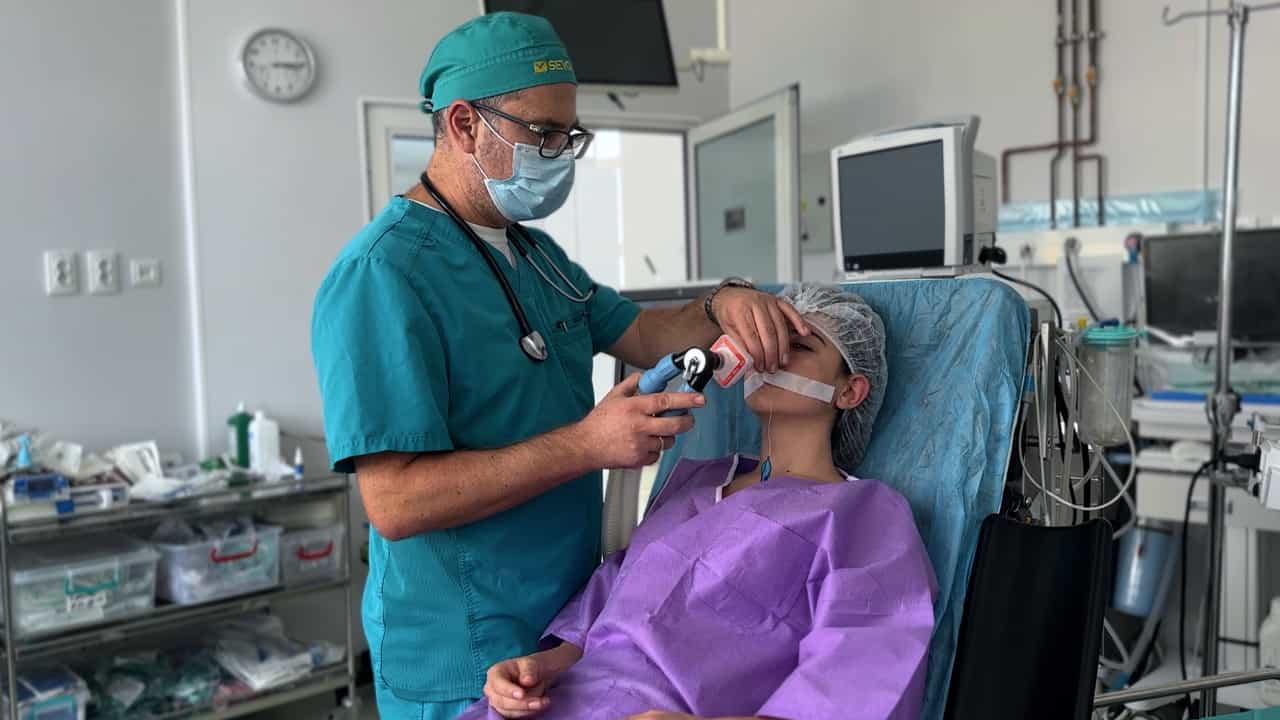
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
Size Matters: Endotracheal Tube Sizes and Glottic Stenosis Familiarity Among Intubating Physicians
Jason S Chwa1, Elizabeth A Shuman2, Karla O'Dell2
1Keck School of Medicine University of Southern California Los Angeles California USA.

Objective:
Given the prevalence of post-intubation acute laryngeal injury (ALgI) and its association with glottic stenosis, greater attention has been placed on the mitigation of modifiable risk factors in patients requiring intubation, notably endotracheal tube (ETT) size. No widely accepted guidelines for adult ETT sizing exist. To better understand how factors driving ETT sizing may differ across specialties, we conducted a survey of faculty Anesthesiologists, Intensivists, and Emergency Medicine (EM) physicians.
Methods:
An anonymous 14-question Qualtrics survey was distributed to relevant faculty employed at a single tertiary care institution. Participants completed questions pertaining to their training, ETT sizing preferences, factors considered in decision-making, and perceived knowledge regarding risk factors of glottic stenosis.
Results:
A total of 103 complete responses were included, with a response rate of 55.1%. Standard ETT size was reported by 94 (91.3%) respondents to be 7.5 mm or larger in adult males and by 92 (89.3%) respondents to be 7.0 mm or larger in adult females. All respondents preferred a significantly larger ETT size for males compared to females (all p < 0.001). "Need for bronchoscopy" was the most cited factor precluding both males and females from being intubated with a smaller ETT across all specialties. When queried on posterior glottic stenosis, 64 (62.1%) respondents erroneously identified cuff pressure as a risk factor.
Conclusions:
Understanding ETT sizing among intubating physicians is critical to reducing intubation-related ALgI. Future laryngologist-led interventions may be directed toward the adoption of a predominately height-based model for ETT sizing and education on glottic stenosis.
Level Of Evidence:
5.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....