Related Experiment Video
Updated: May 14, 2025
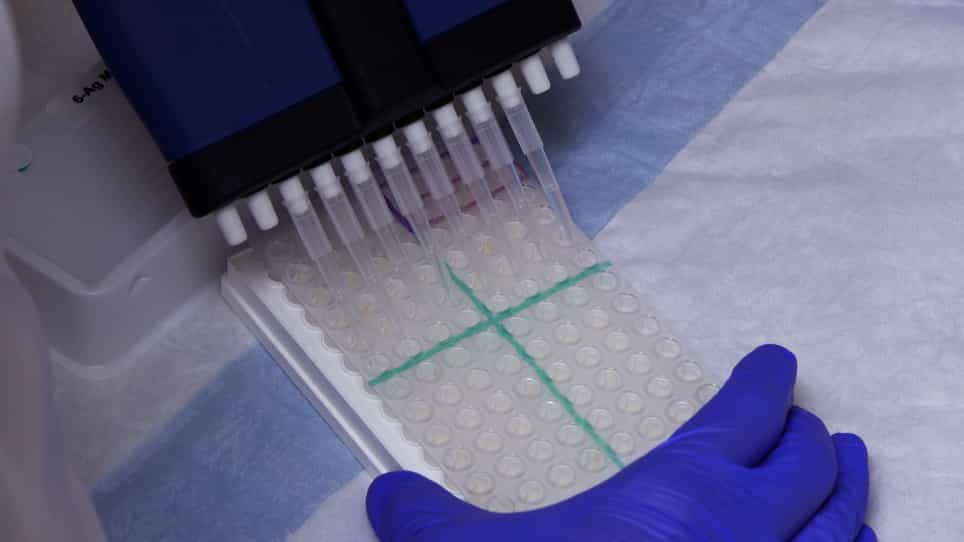

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
An Exploratory Cost-Effectiveness Analysis of Immune Therapy in Delaying the Initiation of Automated Insulin Delivery
Shweta Mital1, Michael J Haller2, Desmond A Schatz2
1College of Pharmacy, University of Manitoba, Winnipeg, Canada.

Objective: Immune therapies such as teplizumab and antithymocyte globulin (ATG) offer promise in delaying type 1 diabetes (T1D). However, growing availability of automated insulin delivery (AID) systems for insulin management may alter the cost-effectiveness of these therapies. Immune therapies may become more cost-effective when paired with AID instead of conventional insulin management. Meanwhile, as immune therapies delay T1D for only a short period, effective AID may reduce the economic value of prevention. This study provides the first cost-effectiveness analysis of the interplay between immune therapies and AID systems. Methods: Using microsimulation modeling, we examined the cost-effectiveness of six alternative prevention-treatment strategies defined by a combination of three preventive immune therapies (teplizumab, ATG, or no therapy) and two insulin management strategies (AID or conventional insulin management). Effectiveness was measured by quality-adjusted life years (QALYs). Costs were estimated from a payer perspective. Results: Among the six strategies considered, preventive ATG therapy followed by AID was the most cost-effective. It entailed $394,250 in lifetime costs and yielded 19.13 QALYs. These costs were lower and QALY gains higher than those with strategies that did not involve immune therapy or AID. Preventive teplizumab therapy followed by AID generated 0.25 more QALYs than ATG therapy followed by AID, albeit at an additional cost of $153,670, resulting in an incremental cost-effectiveness ratio of $369,890/QALY. Conclusions: Preventive ATG therapy followed by AID after T1D onset can be a potentially cost-effective approach. In the absence of randomized clinical trials for ATG in the prevention space, findings in this study assume that ATG is at least half as efficacious as teplizumab. The optimal prevention-treatment strategy will ultimately depend on payers' ability to negotiate prices for teplizumab and further evidence on efficacy of ATG in preventing T1D.
Objective: Immune therapies such as teplizumab and antithymocyte globulin (ATG) offer promise in delaying type 1 diabetes (T1D). However, growing availability of automated insulin delivery (AID) systems for insulin management may alter the cost-effectiveness of these therapies. Immune therapies may become more cost-effective when paired with AID instead of conventional insulin management. Meanwhile, as immune therapies delay T1D for only a short period, effective AID may reduce the economic value of prevention. This study provides the first cost-effectiveness analysis of the interplay between immune therapies and AID systems. Methods: Using microsimulation modeling, we examined the cost-effectiveness of six alternative prevention-treatment strategies defined by a combination of three preventive immune therapies (teplizumab, ATG, or no therapy) and two insulin management strategies (AID or conventional insulin management). Effectiveness was measured by quality-adjusted life years (QALYs). Costs were estimated from a payer perspective. Results: Among the six strategies considered, preventive ATG therapy followed by AID was the most cost-effective. It entailed $394,250 in lifetime costs and yielded 19.13 QALYs. These costs were lower and QALY gains higher than those with strategies that did not involve immune therapy or AID. Preventive teplizumab therapy followed by AID generated 0.25 more QALYs than ATG therapy followed by AID, albeit at an additional cost of $153,670, resulting in an incremental cost-effectiveness ratio of $369,890/QALY. Conclusions: Preventive ATG therapy followed by AID after T1D onset can be a potentially cost-effective approach. In the absence of randomized clinical trials for ATG in the prevention space, findings in this study assume that ATG is at least half as efficacious as teplizumab. The optimal prevention-treatment strategy will ultimately depend on payers' ability to negotiate prices for teplizumab and further evidence on efficacy of ATG in preventing T1D.
More Related Videos
 11:31
High-Efficiency Generation of Antigen-Specific Primary Mouse Cytotoxic T Cells for Functional Testing in an Autoimmune Diabetes Model
Published on: August 16, 2019
 10:03
Bioluminescent Monitoring of Graft Survival in an Adoptive Transfer Model of Autoimmune Diabetes in Mice
Published on: November 18, 2022
Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...