PSMA PET/CT findings in high-risk biochemical recurrence after local treatment of prostate cancer
Related Experiment Video
Updated: May 15, 2025

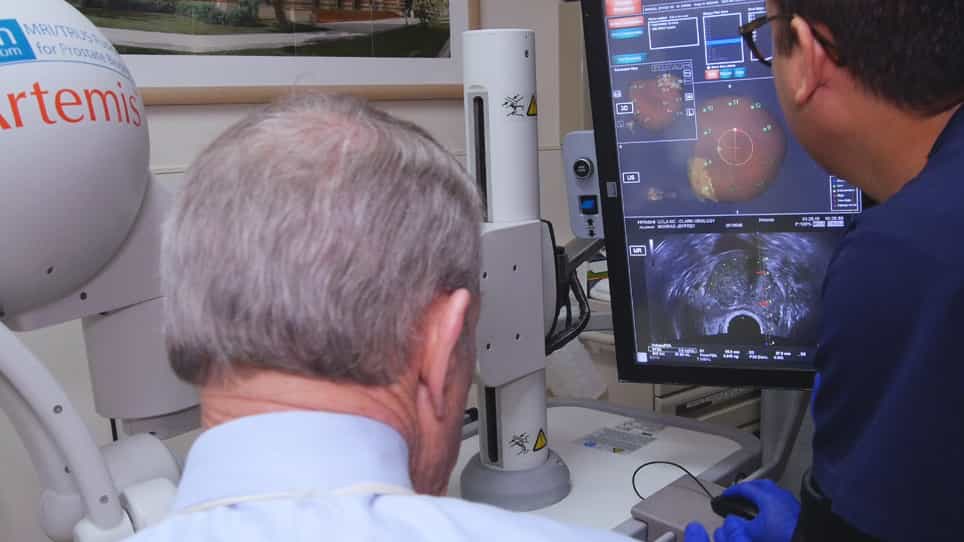
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Nicole Handa1, Richard Bennett2, Eric V Li1
1Northwestern University, Feinberg School of Medicine Chicago IL USA.

Objectives:
To describe PSMA PET/CT characteristics of patients with high-risk BCR.
Subjects/Patients And Methods:
This was a retrospective analysis of patients with high-risk BCR prostate cancer (PSA ≥ 2 ng/ml above nadir after radiation therapy [RT] or ≥1 ng/ml after radical prostatectomy [RP] +/- RT) who underwent PET/CT from July 2021-March 2023. Patients with prior cytotoxic chemotherapy, androgen deprivation therapy (ADT) initiated >3 months prior to PET/CT or positive conventional imaging within 3 months of PET/CT were excluded. Neoadjuvant/adjuvant ADT completed ≥9 months prior was allowed. Logistic regression, Pearson's Chi-squared, Wilcoxon rank sum and Fisher's exact tests were used for analysis.
Results:
A total of 113 of 145 (77%) included patients in the analysis had ≥1 lesion on PSMA PET/CT. There was no difference in PSMA PET/CT positivity based on age, race, Gleason Grade at initial biopsy or PSA. Overall, 29 (20%) patients had lesions in the prostate/prostate bed only, 31 (21%) had lesions consistent with N1M0 disease and 53 (37%) had lesions consistent with M1 disease. For M1 patients, 21/53 (40%) had oligometastatic disease (1-3 lesions), and 32/53 (60%) had a higher burden (>3 lesions). Local recurrence was more common with RT and nodal recurrence with RP, with no difference in distant metastasis by initial treatment.
Conclusion:
Nearly 80% of patients with high-risk BCR after local treatment for prostate cancer with RP and/or RT will have positive findings on PSMA PET/CT. In addition to intensified systemic therapy, up to 55% of the patients may have benefitted from salvage local therapy, nodal pelvic radiation or metastasis-directed therapies for oligometastatic disease.