Related Experiment Video
Updated: May 15, 2025
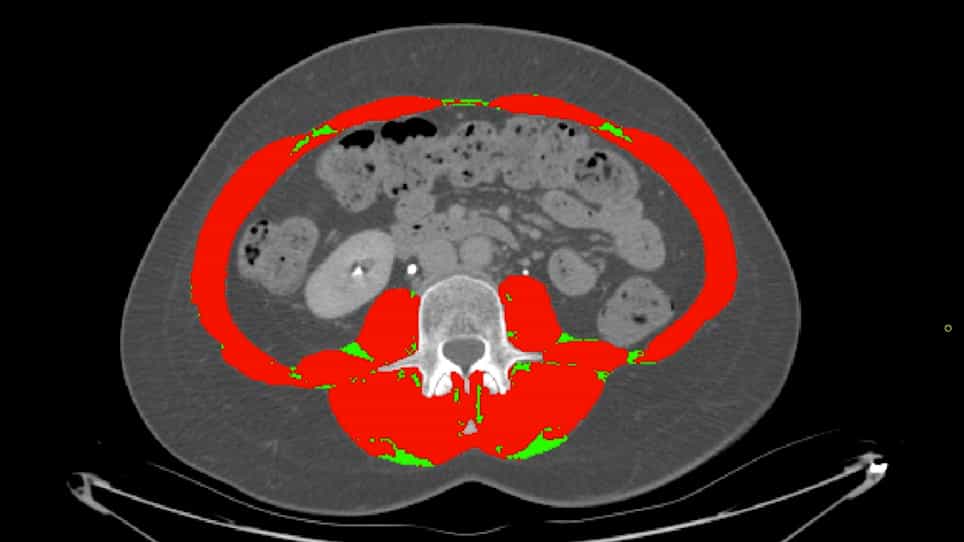

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Association of Visceral Adiposity and Sarcopenia with Geospatial Analysis and Outcomes in Acute Pancreatitis
Ankit Chhoda1, Manisha Bohara2, Anabel Liyen Cartelle1
1Division of Gastroenterology, Department of Medicine, Beth Israel Deaconess Medical Center, Boston, MA 02215, USA.

Abstract:
Background: Radiological imaging has improved our insight into how obesity and sarcopenia impacts acute pancreatitis via several measured variables. However, we lack understanding of the association between social determinants of health and these variables within the acute pancreatitis population. Methods: This study included patients at a single tertiary care center between 1 January 2008 and 31 December 2021. Measurements of visceral adiposity (VA), subcutaneous adiposity (SA), the ratio of visceral to total adiposity (VA/TA), and degree of sarcopenia via psoas muscle Hounsfield unit average calculation (HUAC) were obtained on CT scans performed at presentation. Using geocoded patient data, we calculated the social vulnerability index (SVI) from CDC metrics. Descriptive and regression analyses were performed utilizing clinical and radiological data. Results: In 484 patients with 592 acute pancreatitis-related hospitalization, median (IQR) VA was 176 (100-251), SA was 209.5 (138.5-307), VA/TA ratio was 43.5 (32.3-55.3), and HUAC was 51.3 (44.4-58.9). For our primary outcome, geospatial analyses showed a reverse association between VA and SVI with a coefficient of -9.0 (p = 0.04) after adjustment for age, health care behaviors (i.e., active smoking and drinking), and CCI, suggesting residence in areas with higher SVI is linked to lower VA. However, VA/TA, SA, and HUAC showed no significant association with SVI. The SVI subdomain of socioeconomic status had significant association with VA (-39.78 (95% CI: -75.88--3.70), p = 0.03) after adjustments. For our secondary outcome, acute pancreatitis severity had significant association with higher VA (p ≤ 0.001), VA/TA (p ≤ 0.001), and lower HUAC (p ≤ 0.001). When comparing single vs. recurrent hospitalization patients, there was significantly higher median VA with recurrences (VA-single acute pancreatitis: 149 (77.4-233) vs. VA-recurrent acute pancreatitis: 177 (108-256); p = 0.04). Conclusions: In this study we found that patients residing in more socially vulnerable areas had lower visceral adiposity. This paradoxical result potentially conferred a protective effect against severe and recurrent acute pancreatitis; however, this was not found to be statistically significant.
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: