

Effectiveness of structured myofascial release in the treatment of primary dysmenorrhea
Buse Sert1, Gizem Boztaş Elverişli2, Esra Atılgan1
1Department of Physiotherapy and Rehabilitation, Institute of Health Sciences, İstanbul Medipol University, Kavacık South Campus Göztepe Mah. Atatürk Cad. No: 40/16, 34815 Beykoz, Istanbul, Turkey.

Objectives:
To determine the effect of structured myofascial release techniques on symptoms in individuals with primary dysmenorrhea.
Material And Methods:
Based on an expected effect size (d = 0.25), α = 0.05, β = 0.20, a minimum of 36 participants was calculated using G*Power for 80 % power. Although 52 were targeted considering 30 % attrition, 41 completed the study. We enrolled 41 participants with PD who were randomly classified into three groups: Structured myofascial release (MFG), transcutaneous electrical nerve stimulation (TENS) and training. All participants were evaluated 3 times: 1st measurement on the first day of the menstrual cycle (pre), 2nd measurement after treatment (post) and 3rd measurement 4 weeks after treatment (follow-up). Outcome measures; demographic information, McGill Pain Questionnaire Short Form, Menstruation Symptom Questionnaire (MSQ), Functional and Emotional Measure of Dysmenorrhea (FEMD), and VAS questionnaire were applied. Pain threshold and muscle tension were measured.
Results:
While a significant difference was detected between the pre-post and pre-follow-up values in the pairwise comparisons of MC-1, MC-2, MC-3, and MC-4 values in the MFG group, a significant difference was detected between the pre-post and pre-follow-up MC-1, MC-2, and MC-4 values in the TENS and training groups (p < 0.05). Key outcome differences included a 30 % reduction in MPQ-SF scores in the MFG group (p < 0.001). In all groups, a significant difference was found between the three time-dependent measurements of the MSQ and FEMD values (Pre, Post, Follow-up) (p < 0.05). The mean Follow-up Myoton was 3.63 ± 0.33 in the MFG group, 4.49 ± 0.49 in the TENS group and 4.89 ± 0.57 in the Training group. A significant difference was found between the three time-dependent measurements of Myoton and VAS values (Pre, Post, and Follow-up of the individuals in the MFG group) (*F = 46.600; *χ2 = 25.739; p < 0.001).
Conclusions:
The MFG group demonstrated superior efficacy to the TENS and training groups in alleviating dysmenorrheic pain, enhancing pain threshold, reducing dysmenorrhea symptoms, and decreasing lower abdominal tension. This effect persisted during the follow-up period, 4 weeks post-treatment.
More Related Videos
 07:36
Analysis of Raw and Processed Cyperi Rhizoma Samples Using Liquid Chromatography-Tandem Mass Spectrometry in Rats with Primary Dysmenorrhea
Published on: December 23, 2022
 05:36
Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Related Concept Videos
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:24
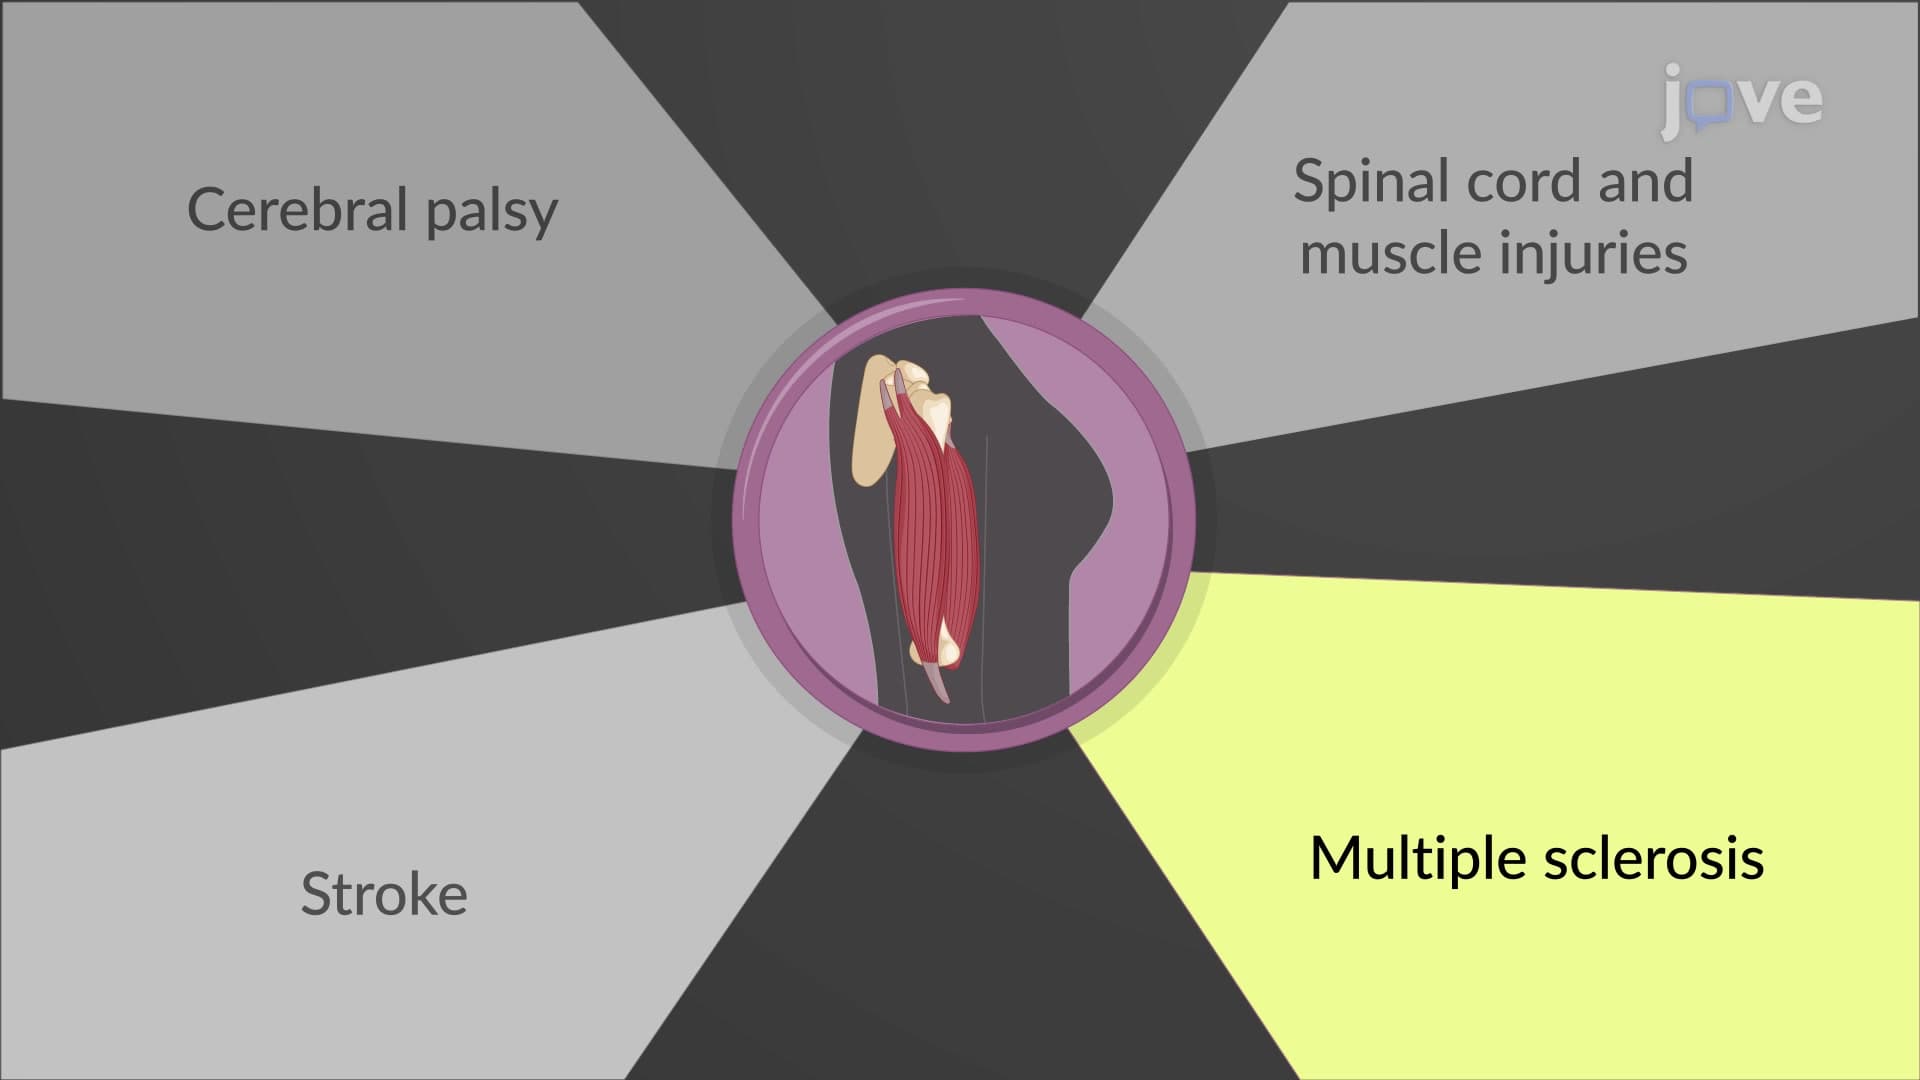
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...