Related Experiment Video
Updated: May 17, 2025


Author Spotlight: Advancing Pathogen Detection and Disease Assessment in Real-Time Using M-ROSE
Published on: March 1, 2024
A Diagnostic Uncertainty in an Immunocompromised Patient: Rapidly Progressive Interstitial Lung Disease vs.
Ibrahim Shamasneh1, Neaam Al-Bahadili1, Faustina Amable1
1Internal Medicine, Piedmont Athens Regional Medical Center, AU/UGA Medical Partnership, Athens, USA.

Abstract:
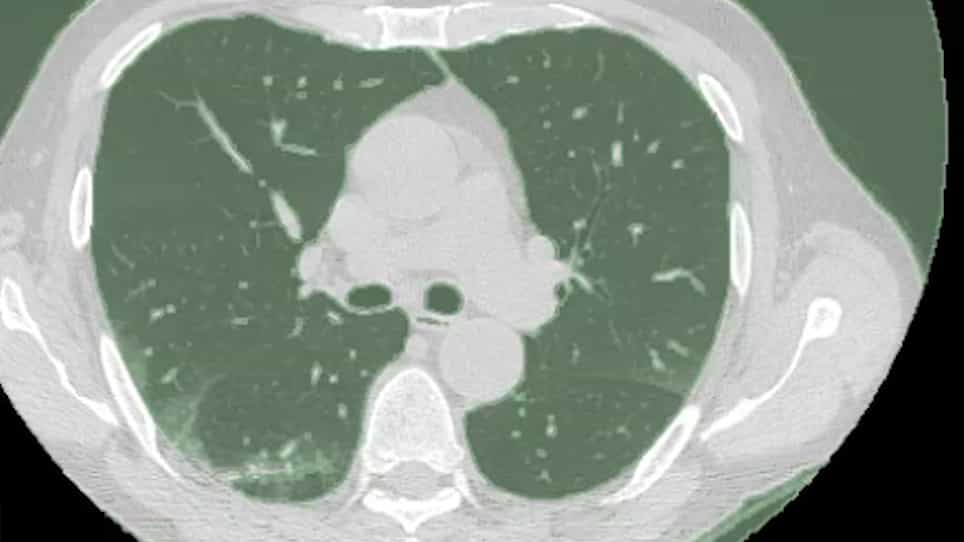
Idiopathic inflammatory myopathies (IIM) are a diverse group of autoimmune disorders characterized by muscle weakness and involvement of extra-muscular organs, including the skin and lungs. The occurrence of interstitial lung disease (ILD) is considered a poor prognostic factor. While antibodies such as anti-Jo-1 and anti-MDA5 are associated with an increased risk of developing ILD, the presence of anti-Mi2 antibodies typically confers a favorable prognosis, with rare lung involvement. This case report presents a diagnostically challenging instance of a patient with positive anti-Mi2 antibodies who developed rapidly progressive ILD (RP-ILD) versus possible Pneumocystis jiroveci pneumonia (PJP). We present a 74-year-old Caucasian woman with a history of Stage IV adenocarcinoma with brain metastasis, complicated by vasogenic edema, treated with 12 mg of dexamethasone daily. Two weeks later, she developed proximal muscle weakness and was diagnosed with steroid-induced myopathy. Four weeks afterward, she presented with progressive shortness of breath and hypoxia, requiring high-flow nasal cannula and ICU admission. CT imaging revealed new multifocal opacities with perihilar ground-glass opacities. Review of previous investigations showed linear ground-glass opacities in the left lung and a positive anti-Mi2 autoantibody. The patient was started on intravenous steroids and intravenous immunoglobulin (IVIG) with subsequent improvement. On day five of hospitalization, serum beta-D-glucan returned elevated. Due to overlapping features with PJP, trimethoprim/sulfamethoxazole was initiated. The patient improved significantly and was later discharged on room air. Follow-up imaging six months later showed near-complete resolution. This case highlights the diagnostic complexity in critically ill, immunosuppressed patients with acute respiratory failure, where both autoimmune and infectious etiologies, such as PJP, should be considered.

Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History