Related Experiment Video
Updated: May 21, 2025
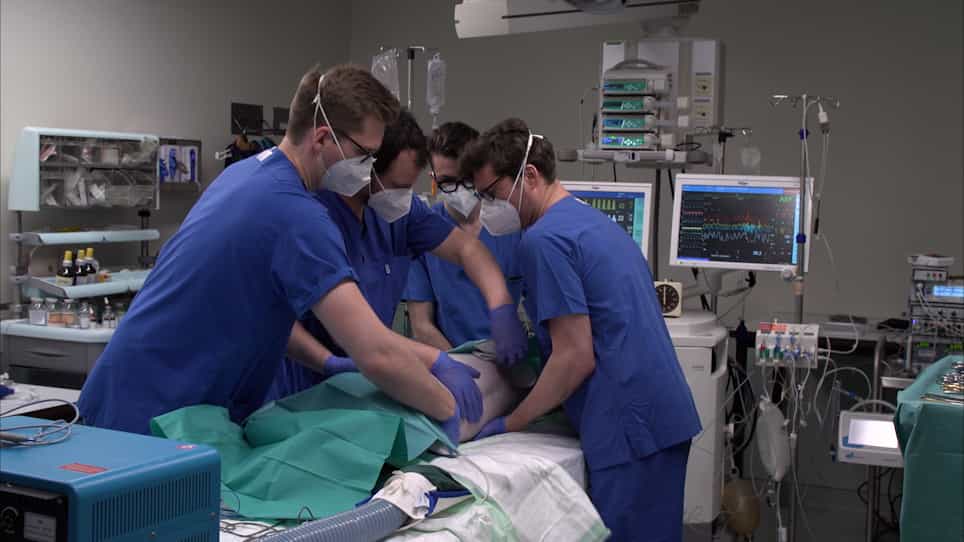

Real-Time Assessment of Spinal Cord Microperfusion in a Porcine Model of Ischemia/Reperfusion
Published on: December 10, 2020
Spinal Cord Protection for Open Descending Thoracic and Thoracoabdominal Aorta Surgery: Analysis of The Society of
Andrea Amabile1, Levi N Bonnell2, Alex Del Vecchio3
1Division of Cardiac Surgery, Department of Surgery, Yale School of Medicine, New Haven, Connecticut; Division of Cardiac Surgery, Department of Cardiothoracic Surgery, University of Pittsburgh, Pittsburgh, Pennsylvania; UPMC Heart and Vascular Institute, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania.

Background:
Spinal cord injury (SCI) is a devastating complication of open descending thoracic (DTAA) and thoracoabdominal aortic aneurysms (TAAA). We evaluated the efficacy of spinal drain placement on spinal injury in DTAA/TAAA repair.
Methods:
Adult patients (≥18 years) undergoing open DTAA/TAAA repair without aortic root, ascending, or arch involvement were identified from The Society of Thoracic Surgeons Adult Cardiac Surgery Database (2017-2023). Patients with preoperative paralysis, postoperative spinal drain placement, or who died in the operating theater were excluded. Primary SCI outcomes were (1) lower extremity paralysis lasting >24 hours, and (2) a composite of paralysis and/or paresis lasting >24 hours. Multivariable logistic regression models with adjustment for patient, intraoperative, and aortic disease factors were derived to evaluate the role of spinal drain placement in DTAA and TAAA repair.
Results:
The study population included 2724 patients from 224 hospitals who underwent DTAA (n = 813; 61.3% spinal drain) or TAAA (n = 1911; 75.2% spinal drain) repairs. Observed rates of SCI were distinctly higher for TAAA than for DTAA repairs (paralysis: 7.3% vs 1.9%, P < .001; paralysis/paresis: 10.3% vs 3.0%; P < .001). Spinal drain was independently associated with increased paralysis (adjusted odds ratio, 3.63; 95% CI, 1.94-6.80; P < .001) and paralysis/paresis (adjusted odds ratio, 2.51; 95% CI, 1.58-4.00; P < .001) in TAAA repair but not DTAA.
Conclusions:
An unexpected association was found between spinal drain use and increased SCI. We hypothesize that spinal drain use may indicate higher-risk anatomy as opposed to being a causative factor of SCI.

Related Concept Videos
 01:15
Thoracic Aorta
 01:54
The Spinal Cord
 01:15
Spinal Cord: Gross Anatomy