Related Experiment Video
Updated: May 23, 2025
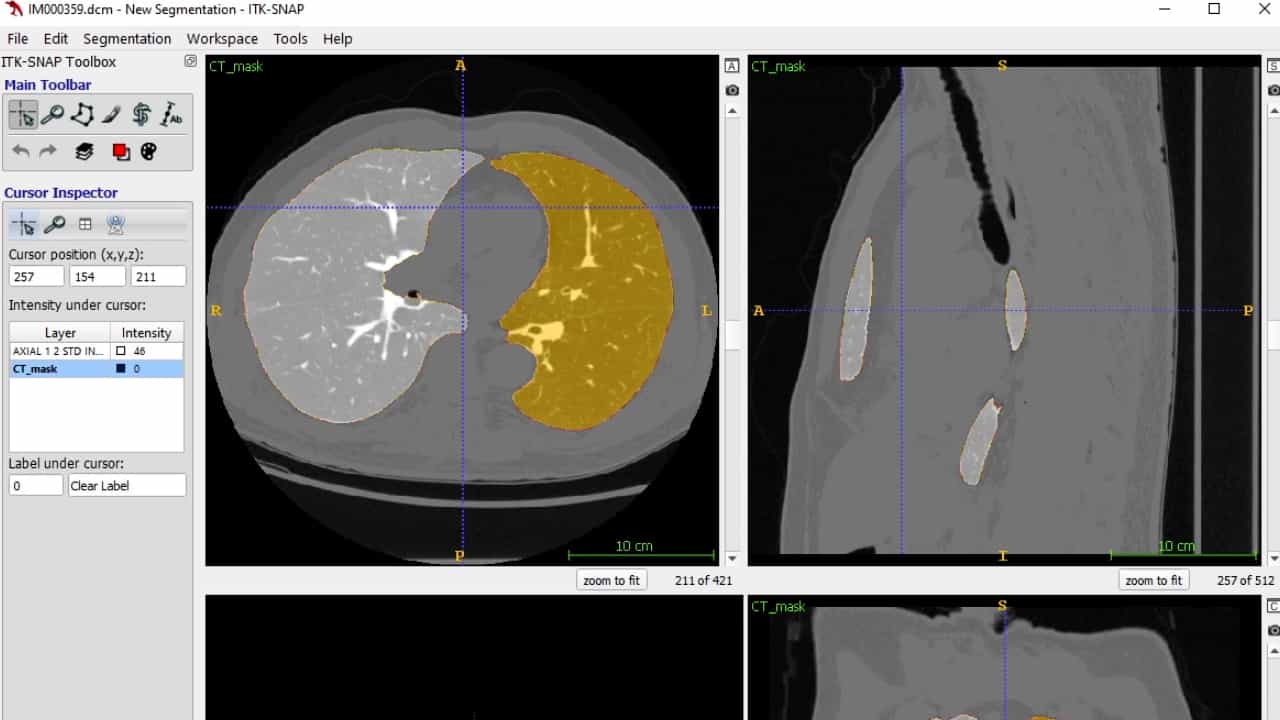

Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Use of quantitative CT chest imaging to derive and assess a radiographic phenotype of deployment-related constrictive
Alexander J Bell1, Maria Masotti2, Sundaresh Ram1,3,4
1Department of Radiology, University of Michigan, Ann Arbor, MI, USA.

Background:
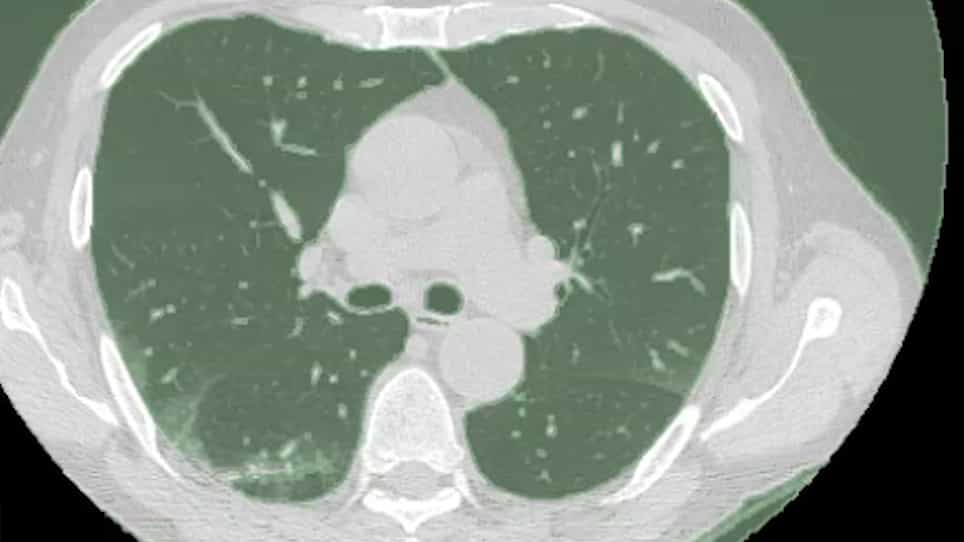
Efforts to phenotype veterans that developed respiratory symptoms following deployments to the Southwest Asia Theater of Military Operation have been limited by the insensitivity of current non-invasive testing to objectively identify deployment-related constrictive bronchiolitis and other features of chronic lung injury. In this study, we derived a quantitative CT (QCT)-based radiographic phenotype of biopsy-proven deployment-related constrictive bronchiolitis (DRCB) and assessed its ability to assist in the phenotyping of non-biopsied formerly deployed symptomatic veterans.
Methods:
QCT analysis combined with demographic, physiologic, symptom, and exposure data was obtained from three cohorts: military personnel with biopsy-proven deployment-related constrictive bronchiolitis (DRCB, n = 37), formerly deployed symptomatic veterans (FDSV, n = 71), and asymptomatic civilians (Control, n = 98). Differences in unadjusted QCT metrics and demographic variables between cohorts were identified and further assessed by principal component analysis. Thereafter, adjusted data from the DRCB cohort was used to derive a QCT-based radiographic phenotype of DRCB expressed as a DRCB-Probability Index (DRCB-PI). Application of the DRCB-PI to the FDSV cohort was used to assess additional phenotypic metrics associated with the DRCB phenotype (DRCB-PI > 0.5).
Results:
Individual unadjusted QCT metrics for functional small airways disease and high attenuation area were elevated in DRCB and FDSV cohorts (relative to Control). Primary component analysis revealed that DRCB and FDSV cohorts overlapped and were distinguished from the Control cohort. The FDSV subjects whose DRCB-PI was > 0.5 had greater evidence of small airways disease (assessed by oscillometry and QCT) and self-reported more intense immediate health effects to their exposures to military burn pit smoke, and sand and dust.
Conclusions:
Application of a QCT-derived radiographic phenotype of DRCB identified a subset of veterans with evidence of abnormal small airways and more severe self-reported health effects following inhalational exposures during military deployment. Future studies incorporating QCT may help establish non-invasive strategies to detect DRCB and other forms of chronic lung injury.

Related Concept Videos
 01:30
Radiological Investigation I: X-ray and CT
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...