Related Experiment Video
Updated: May 23, 2025
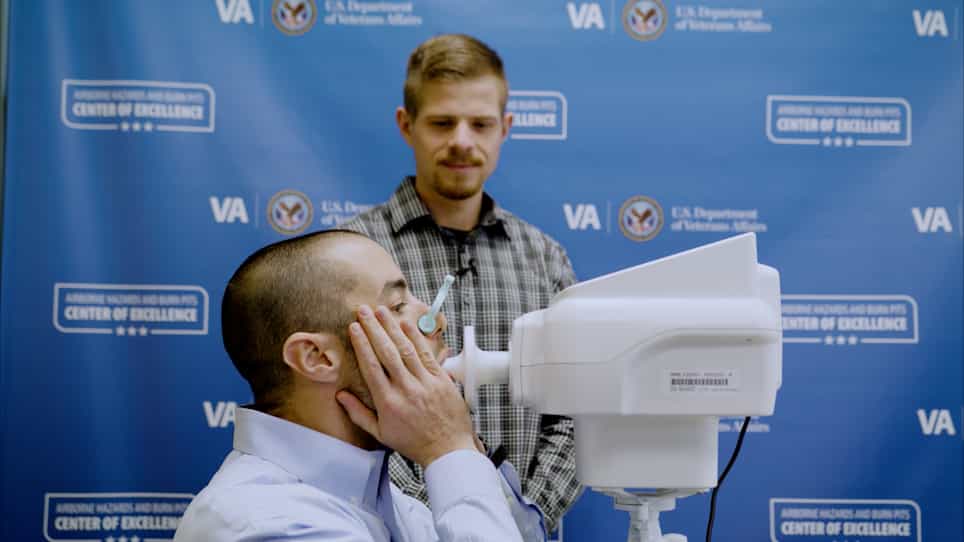

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Evaluation of the Accuracy of a Mechanical Insufflation-Exsufflation Device's Cough Peak Flow Measurement
Neeraj M Shah1,2, Sophie Madden-Scott1, Chloe Apps1,3,4
1Drs. Shah, Suh, Murphy, Ms. Madden-Scott, Apps, Mr. Hart, and Kaltsakas are affiliated with Lane Fox Clinical Respiratory Physiology Centre, Guy's and St Thomas' NHS Foundation Trust, London, United Kingdom.

Abstract:
Background: Mechanical insufflation-exsufflation (MI-E) is used to augment secretion clearance in neuromuscular patients with weakened cough strength. Cough peak flow (CPF) is a measure of cough function that is used to assess a patient's ability to clear secretions, with thresholds set that categorize cough as effective, ineffective or severely ineffective. MI-E is prescribed according to these thresholds, and CPF is used to assess titration of MI-E settings. The Clearway2 (Breas Medical, Stratford-upon-Avon, United Kingdom) displays a real-time CPF, measured by an internal pneumotachograph. This study sought to assess the agreement and repeatability of this displayed CPF, against the reference CPF measurement by a calibrated pneumotachograph. Methods: This study consisted of two phases (1) lung model (Group A) and (2) acutely unwell individuals with neuromuscular conditions (Group B) and clinically stable individuals with neuromuscular conditions (Group C). Simultaneous CPF measurements were recorded from the MI-E device (CPFMI-E) and a calibrated pneumotachograph (CPF), which was inserted into the MI-E circuit. Bland-Altman analysis was used to assess agreement between methods of measurement, and repeatability was assessed using a repeated measures analysis of variance. Results: During phase 1, 805 simulated coughs were evaluated with the Clearway2. The mean bias toward CPFMI-E was 33 L/min (95% limits of agreement 6-60 L/min). During phase 2, the mean bias increased to 66 L/min (95% limits of agreement 13-119 L/min). CPFMI-E and CPF both had good repeatability in all groups. Conclusions: The Clearway2 MI-E device provided a real-time CPF measurement that was repeatable and systematically higher than CPF. It may therefore be a useful tool to measure change longitudinally, or in response to changes in MI-E settings, in an individual patient. Caution is advised if using the CPFMI-E to assess cough efficacy against clinical thresholds.
More Related Videos
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
 08:25
Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Related Concept Videos
 01:28
Pipe Flowrate Measurement
The orifice meter is a simple,...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...