Related Experiment Video
Updated: May 23, 2025

High-Efficiency Generation of Antigen-Specific Primary Mouse Cytotoxic T Cells for Functional Testing in an Autoimmune Diabetes Model
Published on: August 16, 2019
Evaluation of proinsulin(F25D) as a targeting ligand for insulin-binding B cells in autoimmune diabetes
Kyle D Apley1, Lindsay E Bass2, Jaylyn King3
1Department of Biomedical Engineering, Washington University, St. Louis, Missouri, 63130, USA.

Insulin-binding B cells are implicated in Type 1 Diabetes (T1D) pathology. Antigen-specific immunotherapy (ASIT) holds promise in T1D. However, ASIT-targeted suppression of insulin-binding B cells is hampered by insulin's hormonal activity and the resulting binding and endocytosis of insulin by insulin receptors (INSR). To evaluate ASIT strategies that target insulin-binding B cells in vivo, non-hormonally active insulin variants are needed. In this work, we aimed to improve upon prior non-hormonal insulin variants by making mutations to the insulin precursor, proinsulin, and including a c-terminal sortase (SrtA) tag (LPETGGHG) to enable facile site-selective bioconjugation to scaffolds or payloads. Of the insulin variants investigated that retained low-nM binding to the murine-derived insulin autoantibody mAb 125, proinsulin(F25D)-SrtA had the lowest INSR binding and activity and the greatest fibrillation resistance. Compared to desoctapeptide insulin, a previously proposed non-hormonal insulin variant, proinsulin(F25D)-SrtA demonstrated 50-fold lower INSR binding and 100-fold greater fibrillation lag time. However, insulin(F25D)-SrtA bound to the anti-insulin antibody 12M4 isolated from a presymptomatic T1D individual, whereas proinsulin(F25D)-SrtA and desoctapeptide insulin did not, highlighting the potential for anti-insulin B cells to develop in human T1D that would escape this ASIT moiety. The characteristics of proinsulin(F25D)-SrtA make it a well-suited non-hormonal insulin variant for insulin-binding B cell targeting and warrants additional study with other anti-insulin B cell specificities derived from T1D individuals.
Insulin-binding B cells are implicated in Type 1 Diabetes (T1D) pathology. Antigen-specific immunotherapy (ASIT) holds promise in T1D. However, ASIT-targeted suppression of insulin-binding B cells is hampered by insulin's hormonal activity and the resulting binding and endocytosis of insulin by insulin receptors (INSR). To evaluate ASIT strategies that target insulin-binding B cells in vivo, non-hormonally active insulin variants are needed. In this work, we aimed to improve upon prior non-hormonal insulin variants by making mutations to the insulin precursor, proinsulin, and including a c-terminal sortase (SrtA) tag (LPETGGHG) to enable facile site-selective bioconjugation to scaffolds or payloads. Of the insulin variants investigated that retained low-nM binding to the murine-derived insulin autoantibody mAb 125, proinsulin(F25D)-SrtA had the lowest INSR binding and activity and the greatest fibrillation resistance. Compared to desoctapeptide insulin, a previously proposed non-hormonal insulin variant, proinsulin(F25D)-SrtA demonstrated 50-fold lower INSR binding and 100-fold greater fibrillation lag time. However, insulin(F25D)-SrtA bound to the anti-insulin antibody 12M4 isolated from a presymptomatic T1D individual, whereas proinsulin(F25D)-SrtA and desoctapeptide insulin did not, highlighting the potential for anti-insulin B cells to develop in human T1D that would escape this ASIT moiety. The characteristics of proinsulin(F25D)-SrtA make it a well-suited non-hormonal insulin variant for insulin-binding B cell targeting and warrants additional study with other anti-insulin B cell specificities derived from T1D individuals.


Related Concept Videos
 01:25
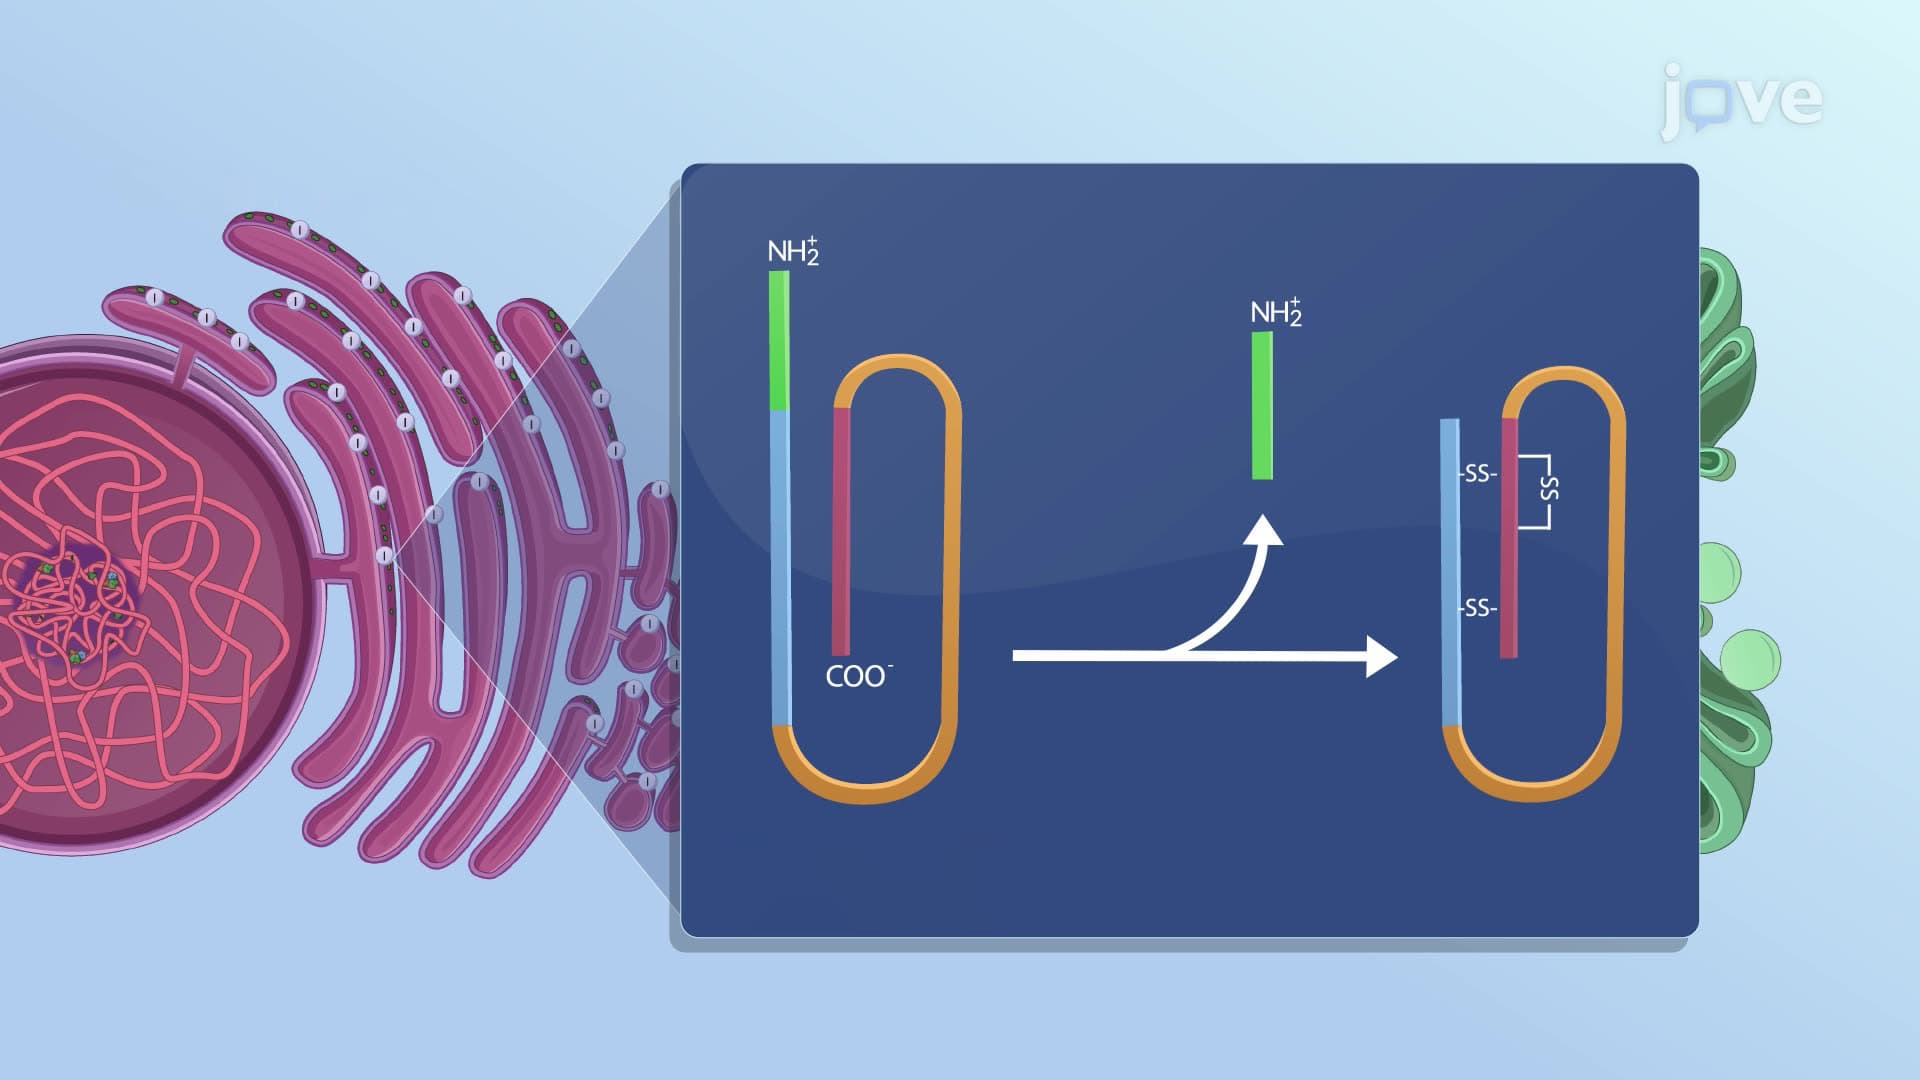
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:05
Insulin Secretory Vesicles
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...