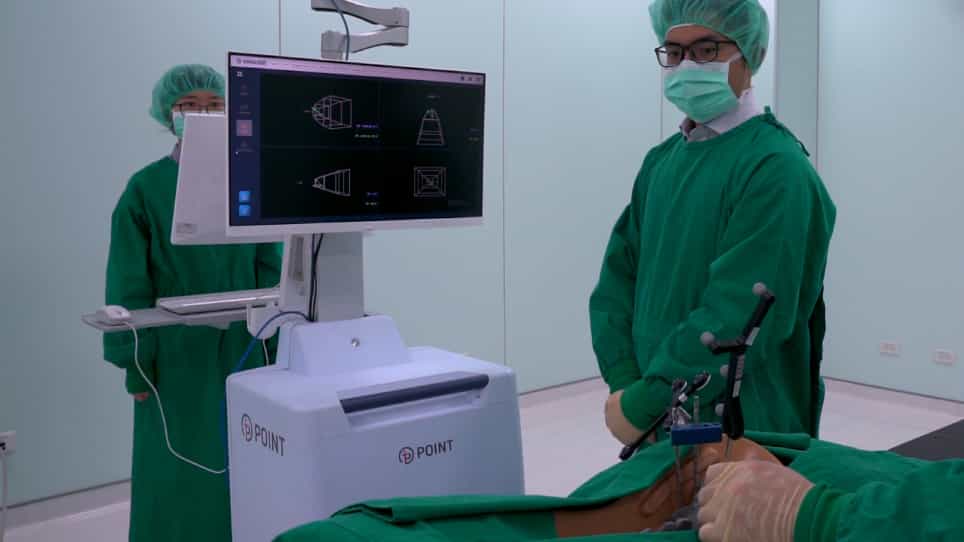
Precision versus Tradition: A Meta-Analysis Comparing Robotic and Conventional Minimally Invasive Pedicle Screw Instrumentation in Thoracolumbar Fractures
Related Experiment Video
Updated: Sep 20, 2025

Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Paweł Łajczak1, Oguz K Sahin2, Eshita Sharma3
1Medical University of Silesia, Katowice, Poland.

Background:
Robotic-assisted minimally invasive surgery (RA-MIS) is becoming increasingly applied to spinal surgery, offering an alternative to conventional minimally invasive spinal surgery (C-MIS). Recently, RA-MIS has been proposed for pedicle screw instrumentation in thoracolumbar fractures. This review aims to evaluate RA-MIS and C-MIS among the thoracolumbar fracture population.
Methods:
This study followed Preferred Reporting Items for Systematic Reviews and Meta-Analyses and Cochrane guidelines. 5 medical databases were searched. Finally, 10 studies were included in the meta-analysis, with a total of 562 patients. Outcomes on operation time, blood loss, pedicle screw accuracy, complications, and cost-effectiveness were evaluated.
Results:
RA-MIS showed superiority in terms of accurate (Gertzbein and Robbins [GR] A) screw placement (odds ratio [OR]: 3.58, 95% confidence interval [CI]: 2.30-5.58, P < 0.001) and satisfactory (GR A+B) screw placement (OR: 3.86, 95% CI: 2.14-6.96, P < 0.001) compared to C-MIS. RA-MIS led to a significantly lower incidence of severely misplaced (GR D+E) screws (OR: 0.26, 95% CI: 0.13-0.51, P < 0.001) and lower blood loss (mean difference [MD]: -12.03, 95% CI: -20.85 to -3.21, P < 0.01). However, we found no statistically significant differences in operation time (MD: -4.92, 95% CI: -12.06 to 2.22, P = 0.18) or complications (screw loosening, nerve injury, or infection). Costs of RA-MIS were significantly higher (MD: ¥8657.61, 95% CI: 6651.39 to 10,663.83, P < 0.01).
Conclusions:
Robotic-assisted minimally invasive spinal surgery is superior in terms of higher pedicle screw accuracy and reduced perioperative blood loss, at the cost of significantly higher costs of surgery. Furthermore, we observed no clear advantages regarding complication rate and total operation time. Future trials should provide a less biased methodology to confirm the findings.