Related Experiment Video
Updated: Sep 20, 2025
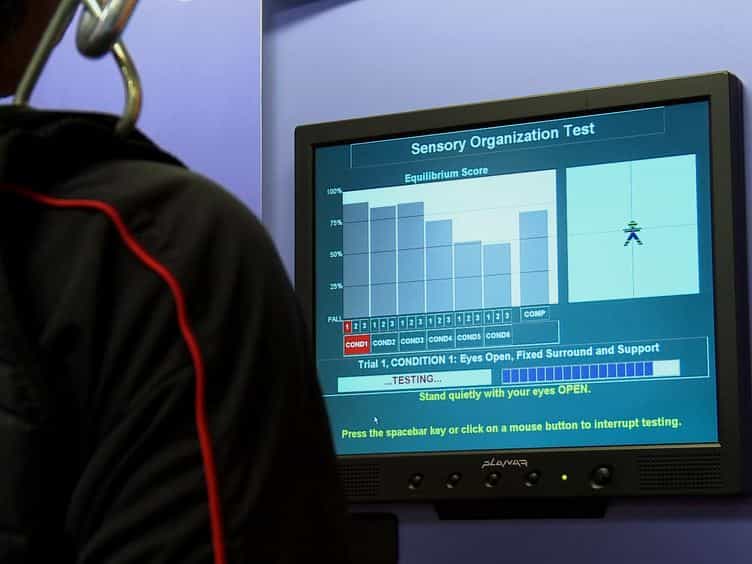

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Validation of ICD-10 Codes to Distinguish Between Claudication and Chronic Limb-Threatening Ischemia in Patients
Sanuja Bose1, David P Stonko1, Sharon C Kiang2
1Division of Vascular Surgery and Endovascular Therapy (S.B., D.P.S., J.H.B., C.W.H.), Johns Hopkins University School of Medicine, Baltimore, MD.

Insights
Administrative claims codes can identify peripheral artery disease phenotypes. Machine learning models, particularly gradient boosting, significantly improve the accuracy of distinguishing between claudication and chronic limb-threatening ischemia (CLTI).
Area of Science:
- Vascular Surgery
- Health Informatics
- Medical Data Science
Background:
- Administrative claims codes are crucial for health research but their accuracy in differentiating peripheral artery disease (PAD) phenotypes is not well-established.
- Distinguishing between claudication and chronic limb-threatening ischemia (CLTI) is vital for appropriate patient management and resource allocation.
- Current diagnostic accuracy of International Classification of Diseases, Tenth Revision (ICD-10) codes for PAD phenotypes needs validation.
Purpose of the Study:
- To validate a predefined set of ICD-10 codes for differentiating claudication from CLTI.
- To optimize the diagnostic accuracy of these codes using a supervised machine-learning approach.
- To compare the performance of machine-learning models against traditional logistic regression for PAD phenotype classification.
Main Methods:
- Utilized the US Medicare-matched VQI-VISION registry database (January 2016-December 2019) including patients undergoing peripheral vascular intervention.
- Established gold standard diagnoses for claudication and CLTI using Vascular Quality Initiative (VQI) registry data.
- Compared ICD-10 codes against gold standard diagnoses and evaluated traditional logistic regression and six machine-learning models, optimizing with grid search cross-validation.
Main Results:
- The predefined ICD-10 codes demonstrated high sensitivity (80.9%) and specificity (81.9%) for distinguishing claudication from CLTI.
- Traditional logistic regression improved sensitivity (96.2%) but decreased specificity (41.8%).
- Gradient boosting classifier achieved the highest performance (AUC 0.892), with 88.6% sensitivity and 77.1% specificity, and 84.2% total agreement.
Conclusions:
- International Classification of Diseases, Tenth Revision (ICD-10) codes can effectively discriminate between claudication and CLTI in administrative claims data.
- The validated set of claims codes provides a reliable tool for researchers to accurately distinguish between these two PAD phenotypes.
- Machine learning, specifically gradient boosting, offers superior performance in enhancing diagnostic accuracy for PAD phenotyping using claims data.
Background:
The accuracy of contemporary administrative claims codes to discriminate between different phenotypes of peripheral artery disease is not well defined. We aimed to validate a predefined set of International Classification of Diseases, Tenth Revision, codes used to distinguish between claudication and chronic limb-threatening ischemia (CLTI) and to optimize their diagnostic accuracy using a supervised machine-learning approach.
Methods:
We included all patients who underwent a peripheral vascular intervention for claudication or CLTI in the US Medicare-matched VQI-VISION (Vascular Quality Initiative Vascular Implant Surveillance and Interventional Outcomes Network) registry database between January 2016 and December 2019. Gold standard claudication and CLTI diagnoses were determined using VQI (Vascular Quality Initiative) registry data. These diagnoses were compared with a predetermined set of International Classification of Diseases, Tenth Revision, codes in the Medicare-matched data set. We used traditional logistic regression modeling and 6 machine-learning models to distinguish claudication from CLTI. We evaluated the sensitivity, specificity, total agreement, and area under the curve for all models, implementing grid search cross-validation to boost machine-learning model performance.
Results:
Of 54 180 patients who underwent a peripheral vascular intervention (mean age, 71.9±10.0 years; 41.0% female; 74.2 non-Hispanic White), 20 769 (38.3%) had claudication and 33 411 (61.7%) had CLTI per gold standard registry definitions. The predefined set of International Classification of Diseases, Tenth Revision, codes had high sensitivity (80.9%), specificity (81.9%), and total agreement (81.3%) for distinguishing claudication versus CLTI. Traditional logistic regression improved sensitivity to 96.2%, but with a substantial drop in specificity (41.8%) and an area under the curve of 0.785. Of the machine-learning models, gradient boosting classifier performed the best (area under the curve, 0.892), improving sensitivity to 88.6% and total agreement to 84.2% with minimal drop in specificity (77.1%).
Conclusions:
International Classification of Diseases, Tenth Revision, codes can be used to discriminate between claudication and CLTI in claims data. Our defined set of claims codes can be used by investigators to accurately distinguish between these 2 peripheral artery disease phenotypes.
More Related Videos
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
 08:16
High-Resolution Three-Dimensional Imaging of the Footpad Vasculature in a Murine Hindlimb Gangrene Model
Published on: March 16, 2022
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:30
Peripheral Artery Disease I: Introduction
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...