Related Experiment Video
Updated: Sep 19, 2025
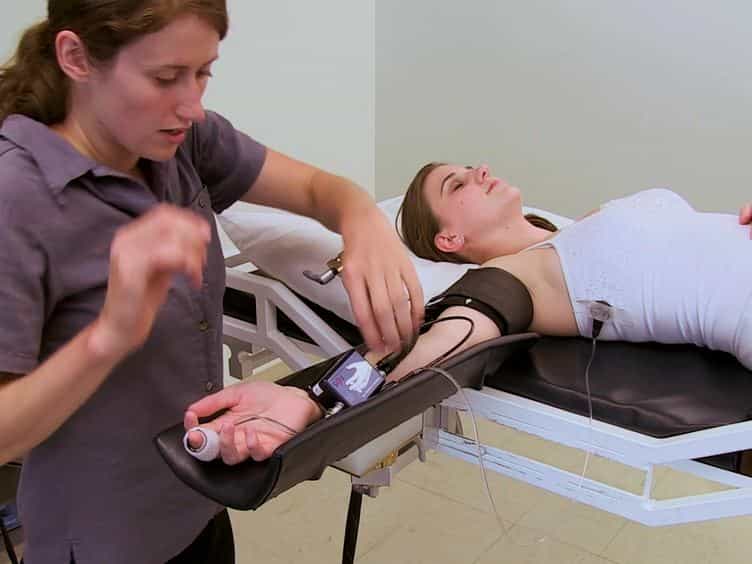

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Correlation between postprandial hypotension and post-induction hypotension in the elderly: a protocol for a
Tianchun Li1,2, Han Zang1, Lu Che1
1Department of Anesthesiology, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences, Beijing, China.

Introduction:
Post-induction hypotension (PIH) is particularly common in elderly patients undergoing general anaesthesia and is associated with severe postoperative complications. Autonomic nervous system (ANS) dysfunction is a potential risk factor for significant haemodynamic fluctuations during general anaesthesia in elderly patients. Tools to identify ANS are currently lacking in perioperative clinical practice. Postprandial hypotension (PPH) is closely linked to ANS dysfunction and is also common among elderly individuals. Therefore, this study aims to explore the relationship between PPH and PIH in elderly patients undergoing non-cardiac surgery. By examining this correlation, we hope to better understand the factors contributing to PIH and explore the potential role of PPH in predicting PIH.
Methods And Analysis:
This is a prospective observational cohort study. 120 elderly Chinese patients aged ≥65 years and scheduled to undergo non-cardiac surgery under general anaesthesia at Peking Union Medical College Hospital (PUMCH) will be included. PPH assessments will include baseline pre-prandial records and blood pressure measurements immediately after meal completion, followed by every 5 min for 120 min. To evaluate PIH, blood pressure will be monitored from the patients' entry into the operating room until 20 min after anaesthesia induction or the initiation of surgery. PIH is defined as systolic blood pressure of <90 mmHg or main arterial pressure <65 mmHg or a decrease of more than 30% from baseline within 20 min after general anaesthesia induction or before surgical incision. Baseline assessment will include regular preoperative assessment, symptoms and medical history related to baroreflex dysfunction, and preoperative volume status will be assessed by passive leg raising test. Follow-up will be conducted at 1, 3, 7 and 30 days and 6 months postoperatively. The primary outcome is PIH. Secondary outcomes include early intraoperative hypotension, postoperative complications graded by Clavien-Dindo classification, 30-day postoperative mortality and 12-item WHO Disability Assessment Schedule 2.0 (12-item WHODAS 2.0) score 6 months postoperatively.
Ethics And Dissemination:
This study has been registered in the ClinicalTrials.gov system of the National Institutes of Health (registration number NCT05575661). The Ethics Committee of PUMCH has also granted ethical approval (approval number I-22PJ008). The study results will be disseminated through publication in peer-reviewed journals focused on anaesthesiology and geriatric medicine, as well as presentations at relevant scientific conferences.
Trial Registration Number:
NCT05575661.


Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:29
Hypertension II: Pathophysiology