

In Vivo Intramuscular pH in Tibia Fractures Is Acidic Prior to Stabilization and Equilibrates Toward Systemic pH 48 h
Danielle F Peterson1, Loren O Black1, Karalynn Lancaster1
1Orthopaedics & Rehabilitation, Oregon Health & Sciences University, Portland, Oregon, USA.

Abstract:
Early and reliable diagnosis of acute compartment syndrome (ACS) remains challenging for providers. Transcutaneous intramuscular pressure (TIMP) measurements, historically proposed for ACS diagnosis, are unreliable and prone to errors. Little is known about In Vivo limb pH balance in lower extremity injuries. The aim of this observational study was to quantify acid-base chemistry through invasive measurement of intramuscular pH (IpH) adjacent to tibia fractures. Patients with tibial shaft or plateau fractures undergoing intramedullary nail or external fixator application were included. We compared anterior compartment IpH to venous pH (VpH) measurements at presurgery and 12, 24, 36, and 48 h postoperatively, as well as TIMP measurements at the beginning and end of surgery. A total of 39 patients with tibia fractures (11 plateau, 27 shaft) provided consent. Initial IpH was universally acidic (mean [SD] 6.57 [0.506]) compared to VpH (7.35 [0.0600]). Final IpH at 48 h converged to VpH (IpH 7.41 [0.408], VpH 7.40 [0.0305]). IpH and VpH demonstrated a significant positive correlation over all 48 h (rrm = 0.476, df = 115, analytic 95% CI [0.322, 0.605], p < 0.0001). There was no correlation between TIMP and IpH (rrm = 0.041, df = 33, analytic 95% CI [-0.296, 0.369], p = 0.816). In tibia fractures requiring operative stabilization, adjacent musculature demonstrated nearly 1 order of magnitude more acidic than systemic circulating physiology prior to skeletal stabilization. Limb IpH converged to systemic VpH within 48 h after surgery. No correlation exists between heritage TIMP measurements and direct measures of intramuscular physiology in the form of In Vivo IpH; improvements in diagnostic modalities for muscular diagnoses, such as compartment syndrome, remain valuable. Level of Evidence: Level 2 prospective observational cohort. Clinical Significance: This study provides a critical foundation for understanding the In Vivo acid-base balance of muscle tissue adjacent to fractures, allowing for future research into the consequence of tissue acidity on inflammation, immune response, and fracture healing.


Related Concept Videos
 01:31
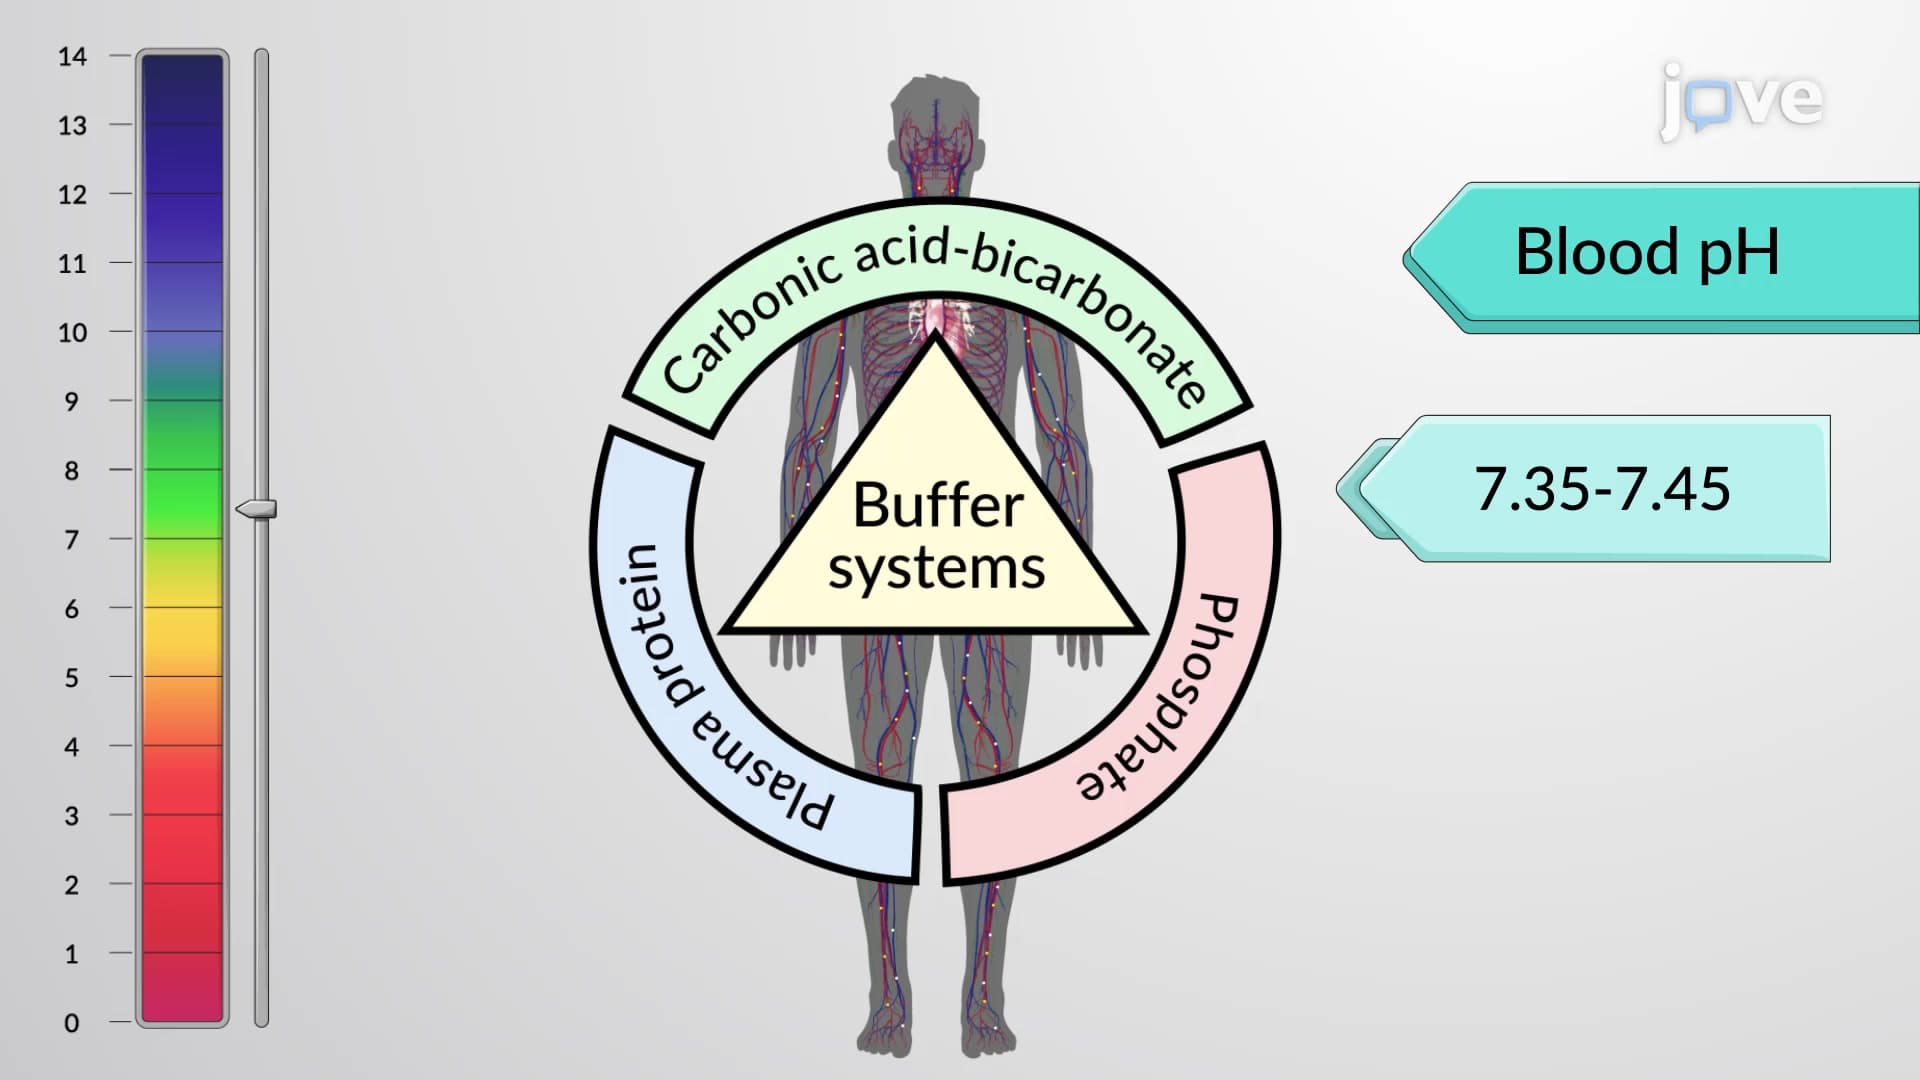
pH Homeostasis
Respiratory...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...