Related Experiment Video
Updated: Sep 19, 2025
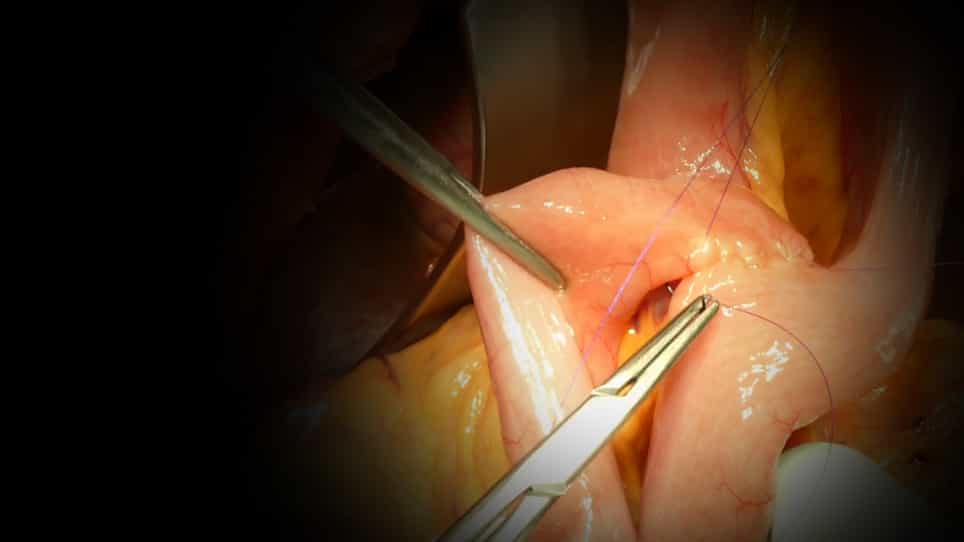

Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Semisupervised home-based prehabilitation in patients undergoing pancreaticoduodenectomy: Impact on postoperative
Bikash Nepal1, Rajesh Gupta1, Thakur Deen Yadav1
1Department of GI Surgery, HPB and Liver Transplantation, Post Graduate Institute of Medical Education and Research, Chandigarh, India.

Background:
Prehabilitation is a relatively newer concept of utilizing the preoperative period for patient optimization to enhance the patient's physiological reserve. We planned a study to see the impact of a structured, multidimensional prehabilitative intervention on postoperative outcomes in patients undergoing pancreaticoduodenectomy.
Methodology:
All consecutive patients planned for pancreaticoduodenectomy from January 2023 to June 2024 were assessed for enrollment. At least 2 weeks of semisupervised home-based prehabilitative intervention was done that included physical exercises, nutritional optimization, smoking cessation, and comorbidity optimization. Postoperative outcomes were recorded that included postoperative pancreatic fistula (POPF), complications grade, delayed gastric emptying, postoperative hospital stay, readmission rate, and mortality. Postoperative outcomes were compared with a historical control group of 81 patients.
Results:
Of the 85 patients who were assessed for inclusion, 58 patients completed the prehabilitation program and underwent pancreaticoduodenectomy and were finally analyzed. The median age of the study group was 58 (interquartile range 45, 63.2), and 29 (50%) were male. Prehabilitation intervention resulted in improved weight control (median 56.5 kg [interquartile range 51.2, 67] vs 55 kg [ 49.2, 67.5], P < .001), increase in breath hold time (median 32 [interquartile range 28, 35] vs 28 [24, 33.5] seconds, P < .001), higher prognostic nutritional index (median 45.5 [interquartile range 39.5, 49.6] vs 47.8 [42.4, 50.8], P = .003), and increased gait speed (median 0.66 [interquartile range 0.58, 0.75] vs 0.54 [0.50, 0.66] m/s, P = .001). Clinically relevant postoperative pancreatic fistula (18 [22.2%] vs 11 [19%], P = .64) and major complications were similar between the prehabilitation and control groups (17 [29.3%] vs 24 [29.6%], P = .96). The mortality in the control group was higher compared with that in the prehabilitation group (6.3% vs 1.7%).
Conclusion:
Semisupervised home-based prehabilitation is effective in improving physiological parameters and functional capacity in pancreaticoduodenectomy. However, establishing the definite role of prehabilitation in pancreaticoduodenectomy to improve postoperative outcomes needs a large randomized study.

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...