Late-stage placental barrier model for transport studies of prescription drugs during pregnancy
Related Experiment Video
Updated: Sep 19, 2025
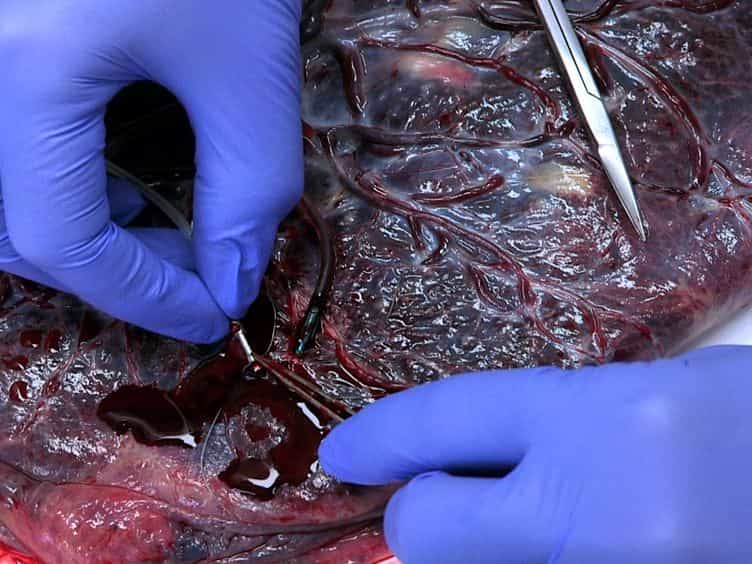
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Sonya Kouthouridis1, Poonam Saha2, Madeleine Ludlow3
1Department of Chemical Engineering, McMaster University, Hamilton, ON, L8S 4L8, Canada. kouthous@mcmaster.ca.

Throughout pregnancy, the placental barrier is crucial for fetal development, evolving continuously to meet the growing nutritional demands of the fetus. Although the placenta has the capacity to selectively filter compounds, harmful xenobiotic substances from the maternal blood can sometimes cross over into the fetal circulation. This drives the development of in vitro placental barrier models in the context of drug transport studies. In this work, we adapted our lab's previous placental barrier model to transplacental drug transport by transitioning from self-assembled vasculature to a simplified straight tubular vasculature to improve throughput and consistency. We then closely examined the angiogenic cytokine secretion and crosstalk between trophoblasts and endothelial cells. Furthermore, we validated this model for drug barrier studies by assessing the permeability of three model therapeutic agents: paclitaxel, vancomycin, and IgG. Drug permeabilities were shown to be drug type, concentration, and size dependent, similar to what has previously been reported. The presented model offers a promising tool for enhancing drug safety assessments in pregnant women, ensuring both maternal well-being and fetal health.
Throughout pregnancy, the placental barrier is crucial for fetal development, evolving continuously to meet the growing nutritional demands of the fetus. Although the placenta has the capacity to selectively filter compounds, harmful xenobiotic substances from the maternal blood can sometimes cross over into the fetal circulation. This drives the development of in vitro placental barrier models in the context of drug transport studies. In this work, we adapted our lab's previous placental barrier model to transplacental drug transport by transitioning from self-assembled vasculature to a simplified straight tubular vasculature to improve throughput and consistency. We then closely examined the angiogenic cytokine secretion and crosstalk between trophoblasts and endothelial cells. Furthermore, we validated this model for drug barrier studies by assessing the permeability of three model therapeutic agents: paclitaxel, vancomycin, and IgG. Drug permeabilities were shown to be drug type, concentration, and size dependent, similar to what has previously been reported. The presented model offers a promising tool for enhancing drug safety assessments in pregnant women, ensuring both maternal well-being and fetal health.


Related Concept Videos
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...
 01:24
Cellular Membranes and Drug Transport
Phospholipids arrange themselves into a bilayer, with hydrophilic heads oriented outward and hydrophobic tails facing inward.
 00:57
Physiological Pharmacokinetic Models: Blood Flow-Limited Versus Diffusion-Limited Models
 01:06
Carrier-Mediated Transport
Active transport involves two types of membrane-spanning transporters: uptake and efflux. Uptake transporters are expressed in the small...