Related Experiment Video
Updated: Jan 18, 2026


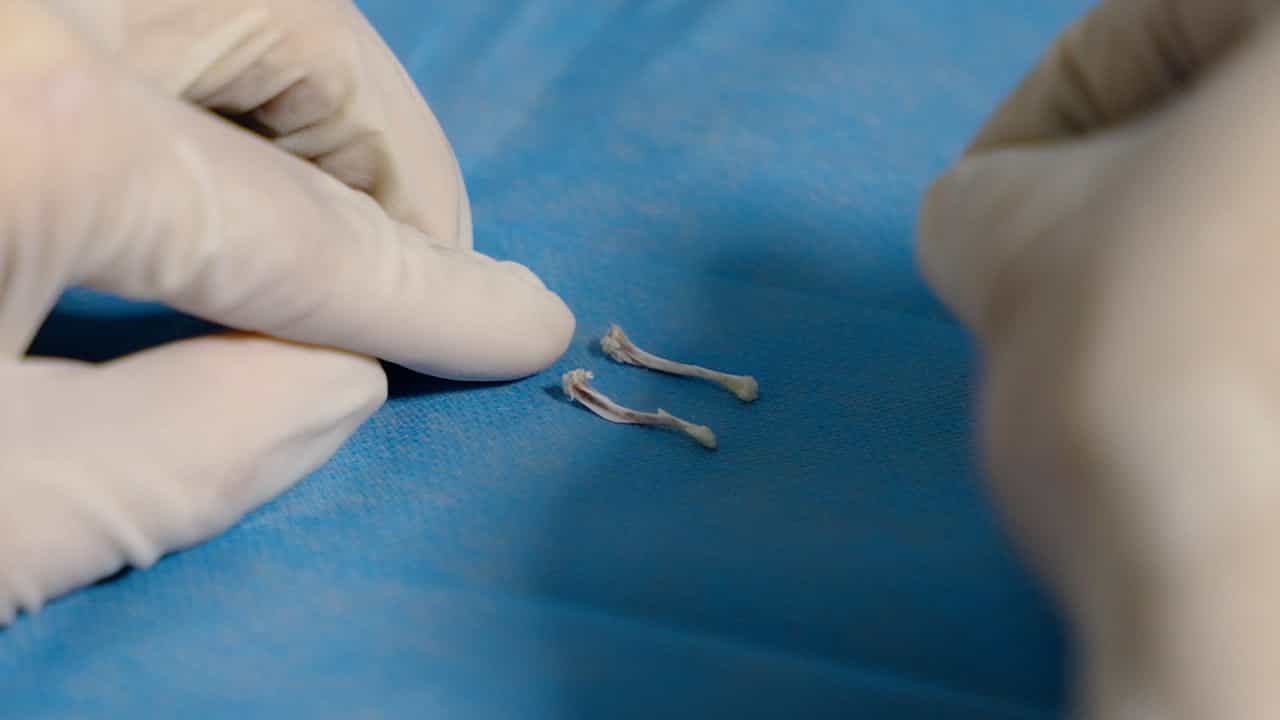
Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Patterns of Bone Mineral Density Loss at Multiple Skeletal Sites Following Recent Menopause in Users and Non-Users of
Kara L Holloway-Kew1, Amelia G Morse2, Kara B Anderson2
1Deakin University, IMPACT - the Institute for Mental and Physical Health and Clinical Translation, School of Medicine, Geelong, Australia. k.holloway@deakin.edu.au.

Abstract:
Post-menopausal bone loss has been well described, however fewer studies have focussed on changes around the time of menopause. This study describes bone mineral density (BMD) loss following recent menopause, stratified by hormone replacement therapy (HT) use. Women (n = 287) who self-reported recent menopause (≥ 12 months to < 5 yr since last menstrual period) for at least one assessment phase of the Geelong Osteoporosis Study were included. BMD was measured using Lunar DPX-L and GE-Prodigy machines. Time since menopause was calculated for each participant at each assessment phase and divided into three categories: < 5 yr, 5-10 yr and ≥ 10 yr. BMD loss was expressed as: (i) cumulative loss over time, (ii) absolute value per year and (iii) percentage loss per year. Proportions of women with normal BMD, osteopenia and osteoporosis were also calculated. Cumulative BMD loss was lower among HT users than non-users at all sites and time categories, except the femoral neck. Compared to the other time categories, HT non-users had a greater rate of BMD loss (expressed as an absolute value or percentage per year) during the first five years postmenopause at the ultra-distal forearm and lumbar spine. No differences were observed between the time categories for HT users. The proportions of women with osteopenia and osteoporosis increased across each of the time categories, but patterns differed by skeletal site, being more pronounced for the femoral neck and mid-forearm sites. Rates of bone loss were greater at the lumbar spine and ultra-distal forearm during the first five years following menopause.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:28
Menopause
 01:40
Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:31
Osteoclasts in Bone Remodeling
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...