Related Experiment Video
Updated: Jul 24, 2026

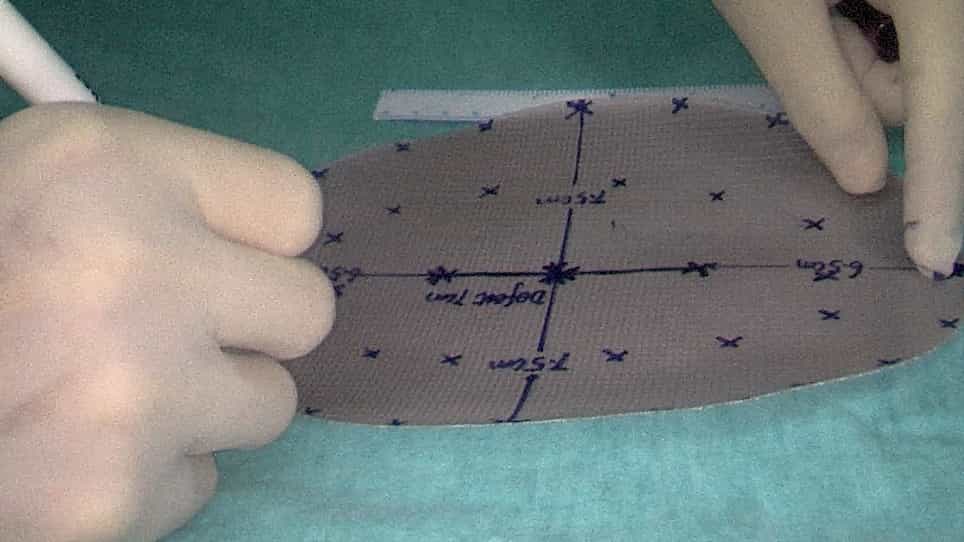
Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
How can we predict or prevent late mesh infection in ventral hernia repair? : Description of the type of study: a
José Bueno-Lledó1, Omar Carreño-Sáenz2, Carla Perez-Alonso2
1Unit of Abdominal Wall Surgery, Department of Digestive Surgery, Hospital Universitari i Politecnic "La Fe". University of Valencia, Calle Gabriel Miró 28, puerta 12, Valencia, 46008, Spain. buenolledo@hotmail.com.

Background:
Mesh infection (CMI) after ventral hernia repair (VHR) is uncommon, with an incidence of 1-7%. The aim of this observational retrospective study was (1) to analyse the incidence and aetiologies of late CMI (one or more years after prosthetic repair) in a series of VHR patients, (2) to identify pre-operative and perioperative variables related to late CMI and (3) to consider possible prevention measures to reduce its occurrence.
Materials And Methods:
A multivariate analysis of a prospective database of patients with a diagnosis of CMI who underwent open VHR between January 2014 and December 2023 at a tertiary centre was conducted. Institutional review board approval was obtained. Two groups of patients were compared: patients with onset of CMI less than one year after VHR (early CMI [ECMI] group) and patients with onset of CMI (sinus or suspected infection) one or more years after VHR (late CMI [LCMI] group).
Results:
At a median of 31.6 months (range: 19-55 months) of post-operative followup, 108 cases of CMI were reported, of which 64 cases were clinically diagnosed within one year of VHR (ECMI group) and 44 cases after one year (LCMI group). The most frequent clinical presentation of CMI was post-operative chronic sinus (94%) and mesh extrusion through the wound (6%). In multivariate analysis, pre-operative predictors associated with LCMI were BMI > 30 (p < 0.001; OR 1.980, p=0.002) and steroid or immunosuppressive drug use (p < 0.001; OR 1.06, p=0.004). Previous hernia repair using PTFE mesh was also a predictor of LCMI (p < 0.002; OR 2.11, p=0.000). Various factors, such as smoking, diabetes, previous hernia repair, presence of a stoma, operative time, concomitant enterotomy or post-operative SSI, were not significant indicators of LCMI.
Conclusions:
CMI is one of the most prevalent and challenging complications of VHR. Obesity (BMI > 30) and immunosuppression, as well as the use of ePTFE mesh in the previous hernia repair, are predictors of LCMI after VHR; studies of these factors may reduce and prevent the occurrence of LCMI.
Insights
Late mesh infection after ventral hernia repair is linked to obesity and immunosuppression. Previous use of PTFE mesh also predicts late infection, highlighting factors for prevention.
Area of Science:
- Surgical complications
- Hernia repair outcomes
- Biomaterial-associated infections
Background:
- Surgical site infection (SSI) following ventral hernia repair (VHR) with mesh is a significant concern.
- Late-onset complications, occurring one or more years post-implantation, present unique diagnostic and management challenges.
- Understanding risk factors for late mesh infection is crucial for improving patient outcomes.
Purpose of the Study:
- To determine the incidence and causes of late surgical site infection (SSI) after prosthetic ventral hernia repair (VHR).
- To identify pre-operative and peri-operative factors associated with late SSI.
- To inform potential preventative strategies for late mesh infection.
Main Methods:
- Retrospective analysis of a prospective database of patients undergoing open VHR between 2014 and 2023.
- Comparison of patients with early CMI (<1 year post-VHR) versus late CMI (≥1 year post-VHR).
- Multivariate analysis to identify predictors of late CMI.
Main Results:
- Of 108 CMI cases, 64 were early and 44 were late. Chronic sinus was the most common presentation (94%).
- Predictors for late CMI included BMI > 30 (OR 1.980), immunosuppressive drug use (OR 1.06), and prior PTFE mesh use (OR 2.11).
- Smoking, diabetes, operative time, and post-operative SSI were not significant predictors of late CMI.
Conclusions:
- Surgical site infection (SSI) remains a challenging complication of ventral hernia repair (VHR).
- Obesity (BMI > 30), immunosuppression, and prior ePTFE mesh use are significant predictors of late SSI.
- Targeting these factors may aid in reducing the incidence of late mesh infection.
More Related Videos

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
Hiatal Hernia
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications