Related Experiment Video
Updated: Sep 19, 2025


An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Defining an Anastomotic Stricture Following Oesophageal Atresia Repair
1The Department of Paediatric Surgery, The Great North Children's Hospital, Queen Victoria Road, Newcastle upon Tyne NE1 4LP, England, United Kingdom.

Insights
The number of dilatations after esophageal atresia repair follows a negative binomial distribution, not Poisson. This statistical model helps predict dilatation probabilities and suggests a definition for anastomotic stricture.
Area of Science:
- Pediatric Surgery
- Biostatistics
- Gastroenterology
Background:
- Babies with esophageal atresia often require multiple anastomotic dilatations post-repair.
- The number of dilatations is a discrete random variable.
- Characterizing this variable's probability distribution is crucial for understanding patient outcomes.
Purpose of the Study:
- To characterize the probability distribution of anastomotic dilatations in infants following esophageal atresia repair.
- To determine population-level probabilities of dilatation.
- To propose a statistical definition for anastomotic stricture.
Main Methods:
- Collected data on dilatations from a consecutive institutional series.
- Fitted the data to Poisson and negative binomial distributions using maximum likelihood estimators.
- Analyzed clinical variables including complexity of atresia, anastomotic leak, salvage surgery, and fundoplication.
Main Results:
- The data fit a negative binomial distribution (μˆ: 4.41, kˆ: 0.56) better than a Poisson distribution.
- The 0.9 quantile indicated 12 dilatations.
- 12 dilatations were significantly associated with salvage surgery, anastomosis resection, and fundoplication, supporting construct validity. The institutional stricture rate was 9%.
Conclusions:
- The negative binomial distribution accurately models the number of dilatations, enabling statistical inference for the broader population.
- A proposed definition of anastomotic stricture is the 0.9 quantile, corresponding to 12 dilatations.
- This framework allows for better understanding and management of anastomotic strictures in infants post-esophageal atresia repair.
Background:
Babies who have undergone repair of an oesophageal atresia may have the anastomosis dilated, often more than once. The number of times a baby undergoes anastomotic dilatation therefore forms a discrete random variable. The aim of this study is to characterise the probability distribution of this variable to determine the probabilities of dilatation for the population of babies with oesophageal atresia. Secondly we suggest a possible definition of an anastomotic stricture.
Methods:
The dilatations performed on a consecutive institutional series were recorded. The dataset was fitted to the Poisson and negative binomial probability distributions, calculating the parameters with maximum likelihood estimators, then calculating the probabilities of the number of dilatations and the quantiles. We also collected the following clinical variables: whether the atresia was complex, the occurrence of an anastomotic leak, the need for salvage surgery and subsequent resection of the anastomosis, fundoplication surgery, karyotype status, cardiac status and neurological status.
Results:
The sample was right skewed and fitted the negative binomial, but not the Poisson distribution, well. The parameters of the distribution are: μˆ: 4.41, kˆ: 0.56. The quantiles and calculation of specific probabilities are presented. The 0.9 quantile is 12 dilatations; this was strongly associated with both the use of salvage surgery (OR = 4.686 (1.105, 17.697), and the need for resection of the anastomosis (OR = 23.366 (3.013, 281.822), p = 0.001) and fundoplication (OR = 7.55 (2.17,30.31, p = 0.0004)), suggesting construct validity. Using this definition, our institutional stricture rate is 9 %.
Conclusions:
Identifying that the number of dilatations fits a negative binomial distribution allows us to use statistical inference to state probabilities not of our sample, but of the underlying population of babies with this condition, assuming the distribution is confirmed to fit other such samples. We suggest the 0.9 quantile of 12 dilatations could form a definition of a stricture.


Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:26
Aneurysm III: Interprofessional Care
 01:19
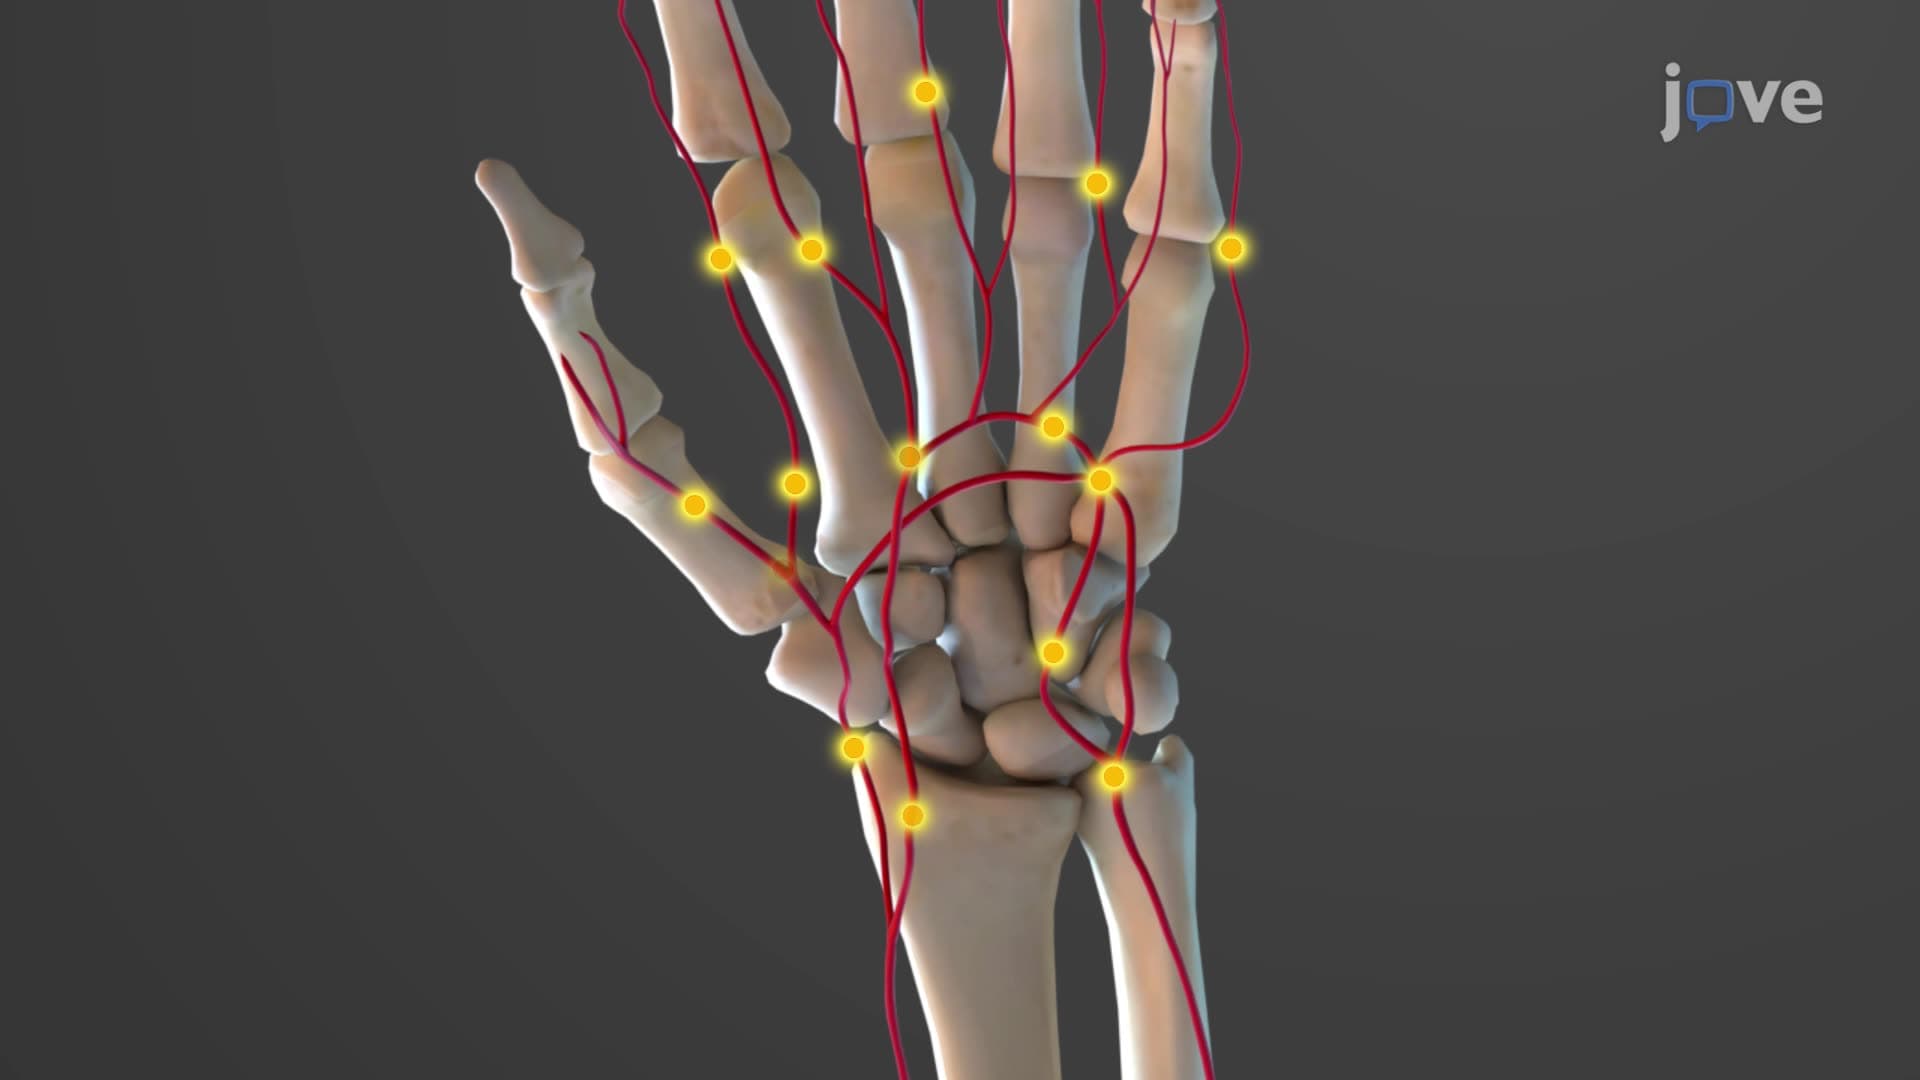
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They...