Related Experiment Video
Updated: Jun 15, 2025
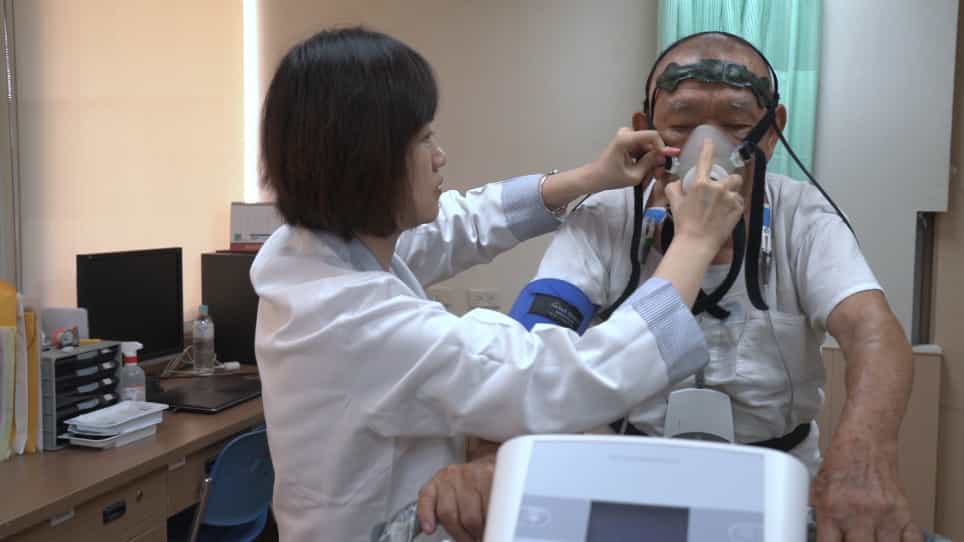

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Temporal behavior of exercise oscillatory ventilation and respiratory muscle performance in patients with heart
Marlus Karsten1, Pietro Palermo2, Irene Mattavelli2
1Research Group on Cardiovascular Health and Exercise (GEPCardio), Physiotherapy Graduate Program, Department of Physiotherapy, Universidade do Estado de Santa Catarina (UDESC), Florianopolis, SC, Brazil; Centro Cardiologico Monzino, IRCCs, Milan, Italy.

Background:
Exercise oscillatory ventilation (EOV) is a negative prognostic marker in patients with heart failure (HF). EOV can either disappear (D-EOV) or persist (P-EOV) during exercise, with each showing different clinical implications. The relationship between respiratory muscle weakness and EOV persistence is not well understood, and its impact on exercise performance and muscle function in HF patients needs further exploration.
Methods:
This study included 98 clinically stable HF patients with reduced left ventricular ejection fraction (LVEF), all undergoing cardiopulmonary exercise testing (CPET) and measurement of maximal inspiratory pressure (MIP) and maximal expiratory pressure (MEP). EOV was classified as D-EOV or P-EOV, and the temporal behavior of EOV was analyzed in relation to inspiratory muscle weakness (IMW), using standard ERS criteria.
Results:
Patients with P-EOV were older, with lower BMI, showed worse exercise performance, with lower peak workload (47 [38;59] vs. 67 [52;94] watts) and pVO2 (10.8 [9.3;12.7] vs. 13.4 [12.1;16.0] mL/kg/min). Respiratory muscle strength was weaker in P-EOV patients (MIP: 73.3 ± 25.6 vs. 93.4 ± 26.6 cmH2O; MEP: 102.9 ± 40.9 vs. 131.8 ± 40.8 cmH2O). A higher proportion of P-EOV patients had IMW (p < 0.05). P-EOV patients with IMW had worse exercise capacity, lower BMI and lower exercise performance (peak workload = 41.5 [36;52] vs. 63 [46;86] watts) than those with D-EOV and IMW.
Conclusions:
EOV persistence is associated with worse exercise performance, respiratory muscle weakness, and potentially sarcopenia in HF patients.


Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:25
Hyperpnea and Hyperventilation