Related Experiment Video
Updated: Jun 14, 2025

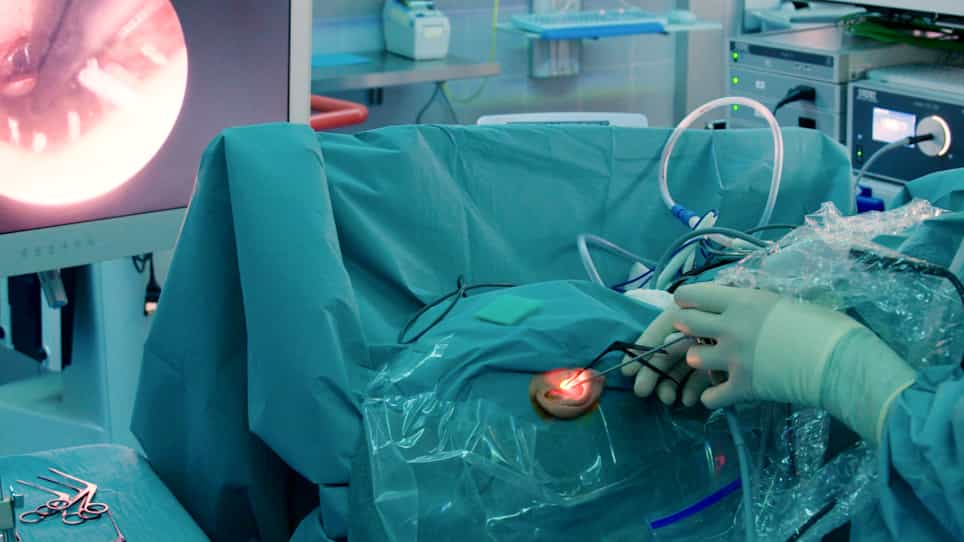
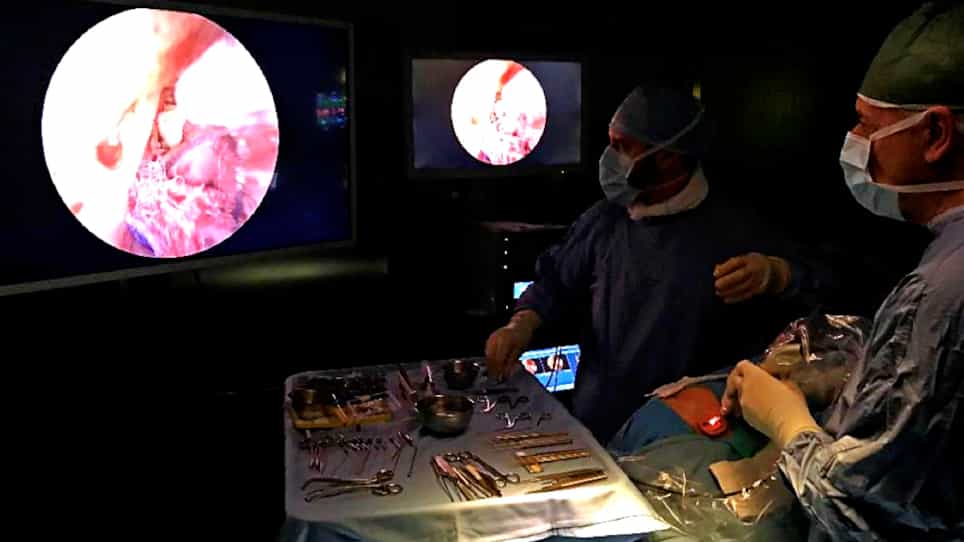
Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Endoscopic surgery versus various open approaches in esthesioneuroblastoma: a systematic review of the literature
Michael Koch1, Matthias Balk1, Sven Schlaffer2
1Department of Otorhinolaryngology and Head and Neck Surgery, University of Erlangen-Nuremberg, Erlangen, Germany.

Objective:
Esthesioneuroblastoma (ENB) is treated using several open surgery (OpS) methods, with or without endoscopic assistance ( ± E-ass) or endoscopic surgery (ES). This systematic review compared the results with various approaches using OpS ± E-ass and ES.
Data Sources:
A systematic PubMed/Medline search was conducted for the period 1990-2023.
Review Methods:
Keywords were "esthesioneuroblastoma" or "olfactory neuroblastoma" and "surgery," "surgical," "resection," "approach," "open," and "endoscopic." Studies/case series and case reports were included. Results with OpS ± E-ass (stratified into various approaches) were compared with ES results. Parameters assessed were follow-up period, frequencies of advanced tumor stages, Hyams grade III-IV tumors, negative margins/gross total resection, postoperative complication rates, preoperative/postoperative radiation therapy/chemotherapy, primary tumor progression, and frequency of/time to first recurrence.
Results:
A total of 88 studies/case series or single cases/case reports (SC/CR) with results after OpS ± E-ass (850 cases) and 84 with results after ES (584 cases) were included. Compared with OpS ± E-ass, after ES, the average follow-up was significantly shorter (p=0.048) and mean crude disease-free survival (DFS) significantly better (studies/case series, p=0.0001; SC/CR, p=0.001). Compared with OPS ± E-ass, after ES, significantly fewer advanced tumors were treated (studies/case series, p=0.0001; SC/CR, p=0.001); negative margins were significantly less frequent (studies/case series, p=0.009); surgical complications were less frequent (studies/case series, p=0.022); less radiation therapy (studies/case series, p=0.043) and/or chemotherapy (SC/CR, p=0.022) was performed; and recurrences were noted significantly less often (studies/case series, p=0.0001; SC/CR, p=0.034). Among OpS ± E-ass, craniofacial resection ± E-ass showed most significant differences from ES.
Conclusions:
These data support that ES can be regarded as the surgical method of first choice in less advanced ENB but may also be a good choice in carefully selected advanced ENB.