Related Experiment Video
Updated: Jun 14, 2025
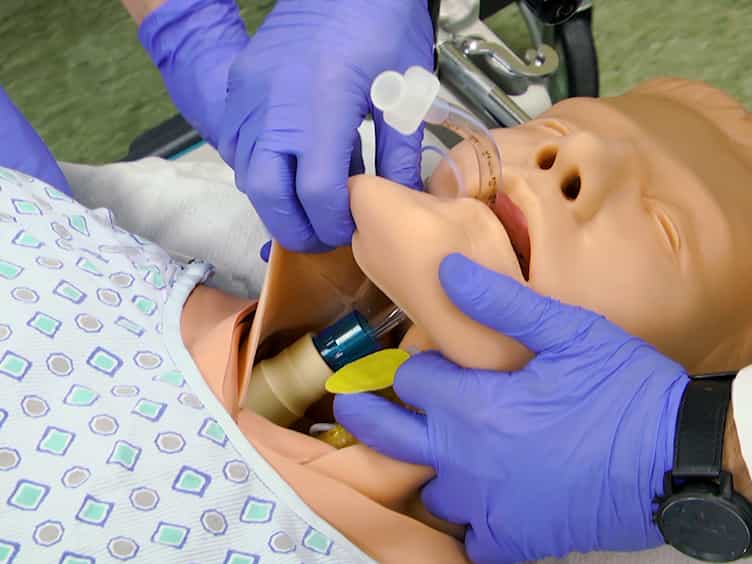

Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
Early Use of a Risk-Adjusted Mechanical Ventilation Digital Quality Measure Bundle in a Large Health System
Christopher M Horvat1,2, Jesse Klug1,2, Ruoting Li2
1ICU Service Center, UPMC, Pittsburgh, PA.

Objectives:
To describe the development, validation, and deployment of a risk-adjusted digital quality measure (dQM) bundle for spontaneous awakening trials (SATs), spontaneous breathing trials (SBTs), and low-tidal volume ventilation (LTVV) as part of a quality improvement (QI) program in a large health system.
Design:
Quasi-experimental before-after study.
Setting:
Thirty-seven ICUs across 14 hospitals in the United States.
Patients:
Mechanically ventilated patients older than 16 years.
Interventions:
An available, open-source, hospital mortality model, a new gradient-boosted ICU mortality model, and four new, heterogenous, stacked ensemble predicted duration of mechanical ventilation (DMV) models (one model predicting up to 14 d of ventilation [14-d DMV model] and three multiple classifier models predicting up to 6 d of ventilation) were created. A regularly refreshing dashboard displaying risk-adjusted information was coupled with audit and feedback sessions for ICU leadership beginning in September 2020.
Measurements And Main Results:
Risk model performance was evaluated, as appropriate, with C-statistics, mean se (MSE), concordance correlation coefficients (CCCs), and F1-scores. Across all ICUs, compliance with SBTs improved from 81 to 97%, LTVV 80 to 90%, and SATs 27 to 65%. Both hospital and ICU mortality models had robust performance, with C-statistics of 0.85 (95% CI, 0.84-0.85) and 0.94 (0.93-0.94), respectively. The 14-day DMV model MSE was 0.63 and CCC was 0.97, whereas the multiple classifier DMV models F1-scores ranged from 0.42 to 0.59. Unadjusted DMV was greater post-implementation (4.32 ± 3.99 d) vs. pre-implementation (3.76 ± 3.66 d). Actual vs. predicted ventilator days were stable pre-implementation vs. post-implementation when assessed with the multiple classifier models and decreased in the post-implementation period when assessed with the 14-day model. Risk-adjusted mortality remained stable.
Conclusions:
A dQM bundle proved useful for efficiently tracking process measures related to a ventilator management QI program in a large health system, although risk-adjusted information differed depending on model constructs. Future work should focus on developing and validating generalizable and interoperable dQM bundles.


Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:30
Health Information Technology and Healthcare Information System
Health Information Technology, commonly called HIT, integrates advanced information systems and technology in healthcare settings. Its primary functions include:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...