

Long-Term Results of Atrioventricular Node Ablation After His Bundle Pacing in Uncontrolled Atrial Tachyarrhythmias
María Teresa Moraleda-Salas1, Ane Erkoreka-Gasituaga2, Carlos Perea-Alfaro2
1Arrhythmia Unit, Department of Cardiology, Hospital Juan Ramon Jimenez, Huelva, Spain.

Introduction:
In the evolving treatment of atrial fibrillation (AF), atrioventricular (AV) node ablation is being reconsidered as an early option for patients with inadequate AF control and limited cure potential. Although interest in physiological pacing is growing, concerns about the long-term safety of permanent His bundle pacing (p-HBP) persist. Our current study aims to evaluate the long-term outcomes of patients who underwent AV node ablation and p-HBP, focusing on left ventricular ejection fraction (LVEF), NYHA class, readmissions, and pacing parameters.
Methods:
This descriptive observational study involved patients with uncontrolled permanent atrial arrhythmias who were eligible for heart rate (HR) control (between January 2019 and July 2020) and underwent p-HBP and AV node ablation, followed during a near 4-year period.
Results:
We conducted a long-term follow-up study with a median duration of 47 months on 32 patients who received p-HBP followed by AV node ablation. The average age was 77 years, predominantly female (65.6%), with a high prevalence of hypertension (90.6%). The main indications for ablation were uncontrolled AF (59.4%) and atypical atrial flutter (37.5%). At baseline, the median LVEF was 60%. Notably, LVEF improved significantly from 45% to 50% in those with reduced baseline function (p < 0.05). NYHA class improvements were also observed over time. The His thresholds remained similar during long-term follow-up, being 1.25 V at 0.4 ms (1.25-2.4 V at 0.4 ms) before AV node ablation and 1.30 V at 0.4 ms (0.75-2.25 V at 0.4 ms), p = 0.89, at long-term follow-up. The impedances remained stable. No complications related to the pacemaker occurred. Number of medications per patient for HR control significantly decreased from 1.6 to 0.37 (p < 0.05), while hospital admissions for tachyarrhythmias dropped markedly. There was one death during the follow-up due to cancer, but conclusions regarding mortality are limited by the small sample size.
Conclusions:
AV node ablation and p-HBP significantly improve functional class and LVEF, with benefits maintained over time. Patients experience fewer emergency visits and reduced HR medication. Pacing parameters remained stable during long-term follow-up.
More Related Videos
 10:46
Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:19
Conduction System of the Heart
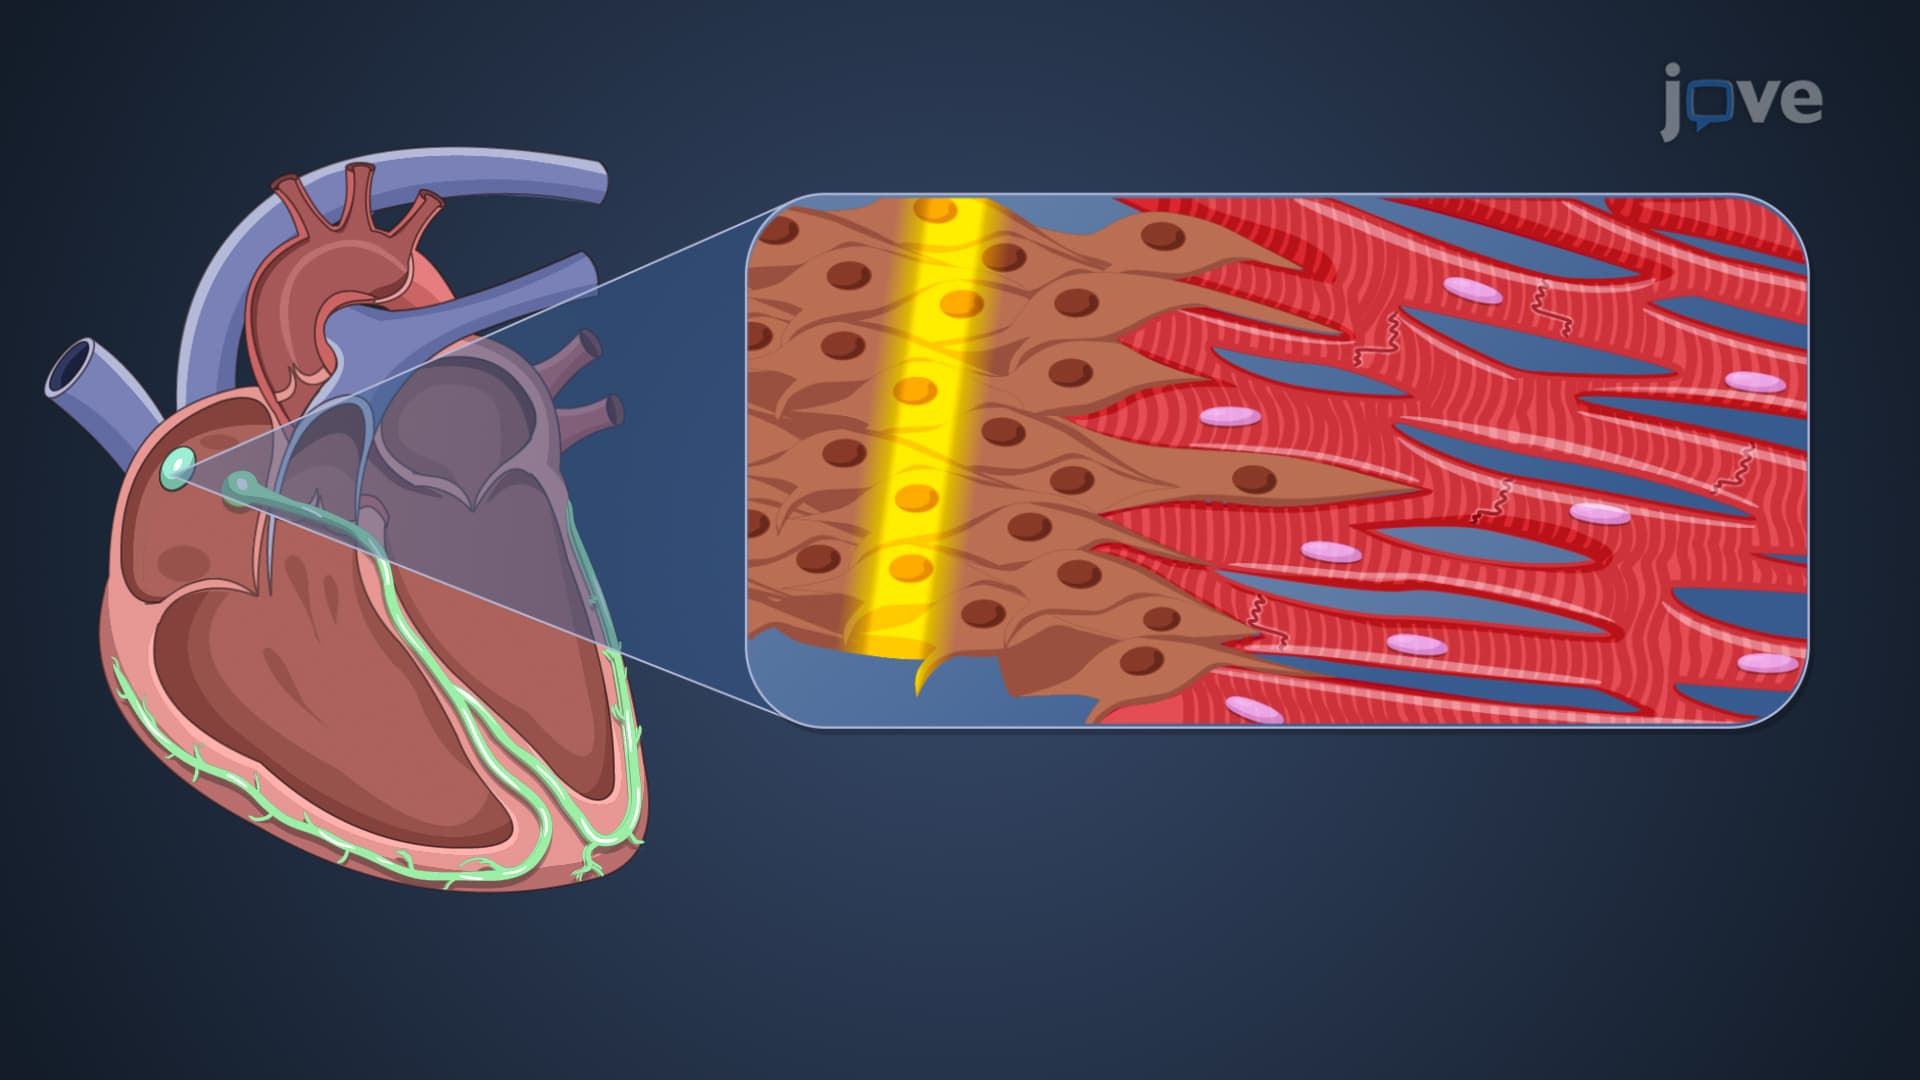
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:19
Electrophysiology of Normal Cardiac Rhythm