Related Experiment Video
Updated: May 3, 2026
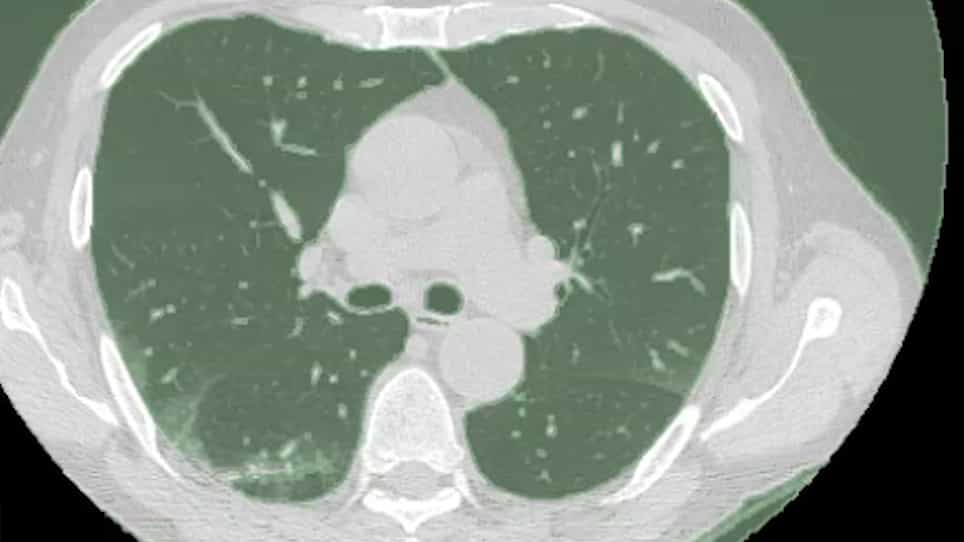

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Bilateral Pleural Effusion in Cryptogenic Organizing Pneumonia: A Case Report and Review of Atypical Presentations
Hussain A Alwesaibi1, Abdullah H Albin Saad1, Mohammed S Almulaify1,2
1Department of Internal Medicine, Dammam Medical Complex, Dammam, SAU.

Abstract:
Cryptogenic organizing pneumonia (COP) is a rare form of idiopathic interstitial lung disease that often presents with non-specific respiratory symptoms and radiographic findings that mimic infectious pneumonia. Due to these overlapping clinical features, COP is frequently misdiagnosed, leading to delays in appropriate management. We report the case of a 23-year-old female patient who presented with dyspnea, productive cough, and fever. Despite receiving broad-spectrum antimicrobial therapy, there was no clinical or radiographic improvement. Imaging revealed bilateral pulmonary opacities and pleural effusions, and diagnostic bronchoscopy with transbronchial biopsy confirmed organizing pneumonia. Secondary causes, including infections, autoimmune diseases, and malignancy, were excluded. The patient started on oral prednisolone, resulting in significant improvement in both symptoms and radiological findings. This case underscores the importance of considering COP in patients with non-resolving pneumonia, particularly when there is no response to adequate antibiotic therapy. A combination of radiological assessment, histopathological confirmation, and exclusion of secondary causes is essential for accurate diagnosis. Clinicians should maintain a high index of suspicion for COP in such scenarios, as timely diagnosis and initiation of corticosteroid therapy are critical for symptom resolution and prevention of disease progression.
Insights
Cryptogenic organizing pneumonia (COP) is a rare lung disease often misdiagnosed as infection. Early corticosteroid treatment is crucial for symptom relief and preventing progression.
Area of Science:
- Pulmonology
- Internal Medicine
- Pathology
Background:
- Cryptogenic organizing pneumonia (COP) is a rare idiopathic interstitial lung disease.
- COP often mimics infectious pneumonia due to non-specific symptoms and radiographic findings.
- Misdiagnosis of COP can lead to delayed treatment and potential complications.
Observation:
- A 23-year-old female presented with dyspnea, cough, and fever, unresponsive to antibiotics.
- Imaging showed bilateral pulmonary opacities and pleural effusions.
- Diagnostic bronchoscopy with transbronchial biopsy confirmed organizing pneumonia after excluding secondary causes.
Findings:
- The patient received a diagnosis of COP after extensive workup.
- Initiation of oral prednisolone led to significant clinical and radiological improvement.
- Exclusion of infections, autoimmune diseases, and malignancy was critical for diagnosis.
Implications:
- This case highlights the importance of considering COP in non-resolving pneumonia.
- Accurate diagnosis requires a combination of imaging, histopathology, and exclusion of other causes.
- Prompt corticosteroid therapy is vital for managing COP and improving patient outcomes.

Related Concept Videos
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:14
Atypical Pneumonia
 01:29
Pneumonia I: Introduction