
Smoking Predicts Mortality in Asymptomatic Patients Undergoing Carotid Endarterectomy but Not Carotid Artery Stenting
Mark Basilious1, Nakia Sarad1, Izzet Akosman1
1Division of Vascular & Endovascular Surgery, Weill Cornell Medicine, New York, NY.

Insights
Smoking increases mortality risk after carotid endarterectomy (CEA) for asymptomatic stenosis. Quitting smoking for at least one month may reduce mortality risk following CEA procedures.
Area of Science:
- Vascular Surgery
- Cardiovascular Medicine
- Public Health
Background:
- Asymptomatic carotid artery stenosis poses a significant risk for stroke.
- Interventional procedures like carotid endarterectomy (CEA) and stenting are used to manage this condition.
- The impact of smoking status on outcomes after these interventions requires further investigation.
Purpose of the Study:
- To evaluate the association between smoking status and mortality following interventions for asymptomatic carotid artery stenosis.
- To compare outcomes between active smokers, former smokers, and never smokers undergoing CEA, transfemoral carotid stenting (TFCAS), and transcarotid artery revascularization (TCAR).
Main Methods:
- Analysis of the Vascular Quality Initiative database (2003-2021).
- Inclusion of patients undergoing CEA, TFCAS, or TCAR for asymptomatic carotid artery stenosis.
- Propensity score matching to control for confounding factors.
- Stratification into never, former, and active smoker cohorts.
- Primary outcomes: 30-day and 1-year mortality.
Main Results:
- Active smoking was independently associated with increased 30-day and 1-year mortality after CEA.
- Former smokers also showed increased 1-year mortality after CEA compared to never smokers.
- No significant differences in mortality were observed between smoking statuses after TFCAS or TCAR.
- Active smokers had a higher risk of myocardial infarction after CEA compared to former smokers.
Conclusions:
- Smoking status is an independent predictor of mortality following carotid endarterectomy (CEA) but not carotid stenting.
- Postponing elective CEA for at least one month after smoking cessation may improve patient outcomes.
- These findings underscore the importance of smoking cessation in patients undergoing intervention for carotid artery disease.
Background:
To assess the influence of smoking status on mortality for individuals undergoing intervention for asymptomatic carotid artery stenosis.
Methods:
The Vascular Quality Initiative database was queried from 2003 to 2021 to identify patients undergoing interventions for asymptomatic carotid artery stenosis with carotid endarterectomy (CEA), transfemoral carotid stenting (TFCAS), or transcarotid artery revascularization (TCAR). Patients were grouped into 3 cohorts: never, former, or active smokers. Active smokers were those who smoked tobacco within 1 month of their procedure, whereas former smokers had quit at least 1 month prior. Propensity matching was then performed adjusting for demographics, comorbidities, preoperative medications, and additional risk factors including anatomic risk, urgency, anesthesia modality, and degree of stenosis. The primary outcomes were 30-day and 1-year mortality. We also evaluated 30-day incidences of transient ischemic attack, stroke, and other complications. Multivariate logistic regression was used to identify independent predictors of mortality.
Results:
We identified 63,651 patients who underwent carotid artery interventions for asymptomatic stenosis: 54,953 received CEA, 3,486 underwent TFCAS, and 5,212 had TCAR. After propensity score matching, no significant differences persisted in preoperative demographics and risk factors. After CEA, active smokers exhibited significantly higher rates of 30-day (0.86% vs. 0.53%, P = 0.021) and 1-year (4.14% vs. 2.58%, P < 0.001) mortality compared to never smokers. Former smokers also had an increased 1-year mortality compared to never smokers (4.28% vs. 3.69%, P = 0.023), but no significant difference in 30-day mortality. Active smokers also had an increased risk of postoperative myocardial infarction after CEA compared to former smokers (0.57% vs. 0.35%, P = 0.013). No significant differences were observed in mortality between smoking statuses after TFCAS or TCAR. Apart from a reduction in stroke rate in active smokers compared to former smokers in TFCAS (1.51% vs. 3.14%, P = 0.046), no other significant differences were noted in any of the secondary outcomes. On multivariate logistic regression analysis, active smoking was independently predictive of 30-day (odds ratio [OR] 1.44, 95% confidence interval [CI]: 1.05-1.97) and 1-year mortality (OR 1.52, 95% CI: 1.32-1.76), and former smoking was predictive of 1-year mortality (OR 1.26, 95% CI: 1.12-1.42) following CEA.
Conclusion:
Smoking status is an independent predictor of mortality following CEA in asymptomatic patients, but not in either stenting modality. Our findings suggest a potential benefit of postponing elective CEA in appropriately selected asymptomatic patients until at least 1 month of smoking cessation is attained.
More Related Videos
 11:00
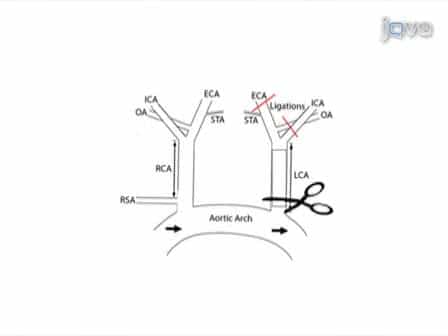
A Model of Disturbed Flow-Induced Atherosclerosis in Mouse Carotid Artery by Partial Ligation and a Simple Method of RNA Isolation from Carotid Endothelium
Published on: June 22, 2010
 09:33
A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:23
Atherosclerosis IV: Nursing Management
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:26
Atherosclerosis III: Management
 01:26
Angina IV: Management
 01:27
Peripheral Artery Disease III: Interprofessional Care