Related Experiment Video
Updated: Sep 18, 2025
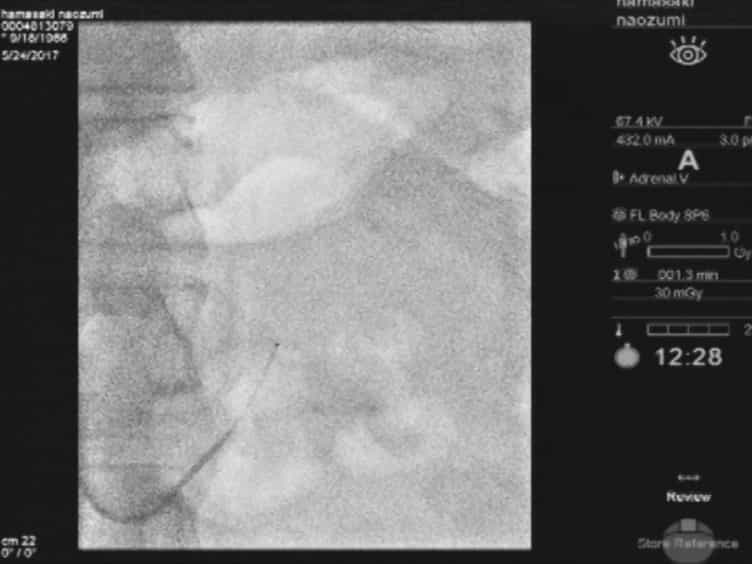
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
A Study of Adrenal Incidentaloma-Related Hormonal Assays After First Integration of the Diagnosis Within Primary
Oana-Claudia Sima1, Mihai Costachescu2, Ana Valea3,4
1PhD Doctoral School of "Carol Davila" University of Medicine and Pharmacy, 010825 Bucharest, Romania.

Background:
Adrenal incidentalomas are detected in various medical and surgical healthcare departments, including primary healthcare. One up to three out of ten individuals confirmed with nonfunctioning adrenal incidentalomas (NFAs) actually present a mild autonomous cortisol secretion (MACS), which is distinct from Cushing's syndrome.
Objective:
We aimed to assess the cortisol secretion in newly detected adrenal incidentalomas in patients who were referred by their primary healthcare physician upon accidental detection of an adrenal tumor at abdominal computed tomography (CT) scan that was performed for unrelated (non-endocrine) purposes.
Methods:
This retrospective study included adults diagnosed with an adrenal incidentaloma via CT during the previous 3 months.
Inclusion Criteria:
age ≥ 40 years (y). A triple stratification of exclusion criteria involved: (1) Clinical aspects and medical records such as active malignancies or malignancies under surveillance protocols, subjects under exogenous glucocorticoid exposure (current or during the previous year), or suggestive endocrine phenotypes for any hormonal ailment; (2) Radiological appearance of suspected/confirmed (primary or secondary) adrenal malignancy, adrenal cysts, or myelolipomas; (3) Endocrine assays consistent with active endocrine tumors. Protocol of assessment included baseline ACTH, morning plasma cortisol (C-B), cortisol at 6 p.m. (C-6 pm), and after 1 mg dexamethasone suppression testing (C-1 mg-DST), 24-h urinary free cortisol (UFC), and a second opinion for all CT scans. MACS were defined based on C-1 mg-DST ≥ 1.8 and <5 µg/dL (non-MACS: C-1 mg-DST < 1.8 µg/dL).
Results:
The cohort (N = 60, 78.33% female; 60.72 ± 10.62 y) associated high blood pressure (HBP) in 66.67%, respectively, type 2 diabetes (T2D) in 28.37% of the patients. Females were statistically significantly older than males (62.40 ± 10.47 vs. 54.62 ± 9.11 y, p = 0.018), while subjects with unilateral vs. bilateral tumors (affecting 26.67% of the individuals) and those with MACS-positive vs. MACS-negative profile had a similar age. Body mass index (BMI) was similar between patients with unilateral vs. bilateral incidentalomas, regardless of MACS. Patients were divided into five age groups (decades); most of them were found between 60 and 69 years (40%). Left-gland involvement was found in 43.33% of all cases. The mean largest tumor diameter was 26.08 ± 8.78 mm. The highest rate of bilateral tumors was 46.67% in the 50-59 y decade. The rate of unilateral/bilateral and tumor diameters was similar in females vs. males. The MACS-positive rate was similar in females vs. males (23.40% vs. 23.08%). A statistically significant negative correlation (N = 60) was found between BMI and C-B (r = -0.193, p = 0.03) and BMI and UFC (r = -0.185, p = 0.038), and a positive correlation was found between C-B and C-6 pm (r = 0.32, p < 0.001), C-B and UFC (r = 0.226, p = 0.011), and C-6 pm and C-1 mg-DST (r = 0.229, p = 0.010), and the largest tumor diameter and C-1 mg-DST (r = 0.241, p = 0.007).
Conclusions:
Adrenal incidentalomas belong to a complex scenario of detection in the modern medical era, requiring a multidisciplinary collaboration since the patients might be initially detected in different departments (as seen in the current study) and then referred to primary healthcare for further decision. In these consecutive patients, we found a higher female prevalence, a MACS rate of 23.33%, regardless of uni/bilateral involvement or gender distribution, and a relatively high rate (than expected from general data) of bilateral involvement of 26.67%. The MACS-positive profile adds to the disease burden and might require additional assessments during follow-up and a protocol of surveillance, including a tailored decision of tumor removal. The identification of an adrenal incidentaloma at CT and its hormonal characterization needs to be integrated into the panel of various chronic disorders of one patient. The collaboration between endocrinologists and primary healthcare physicians might improve the overall long-term outcomes.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:31
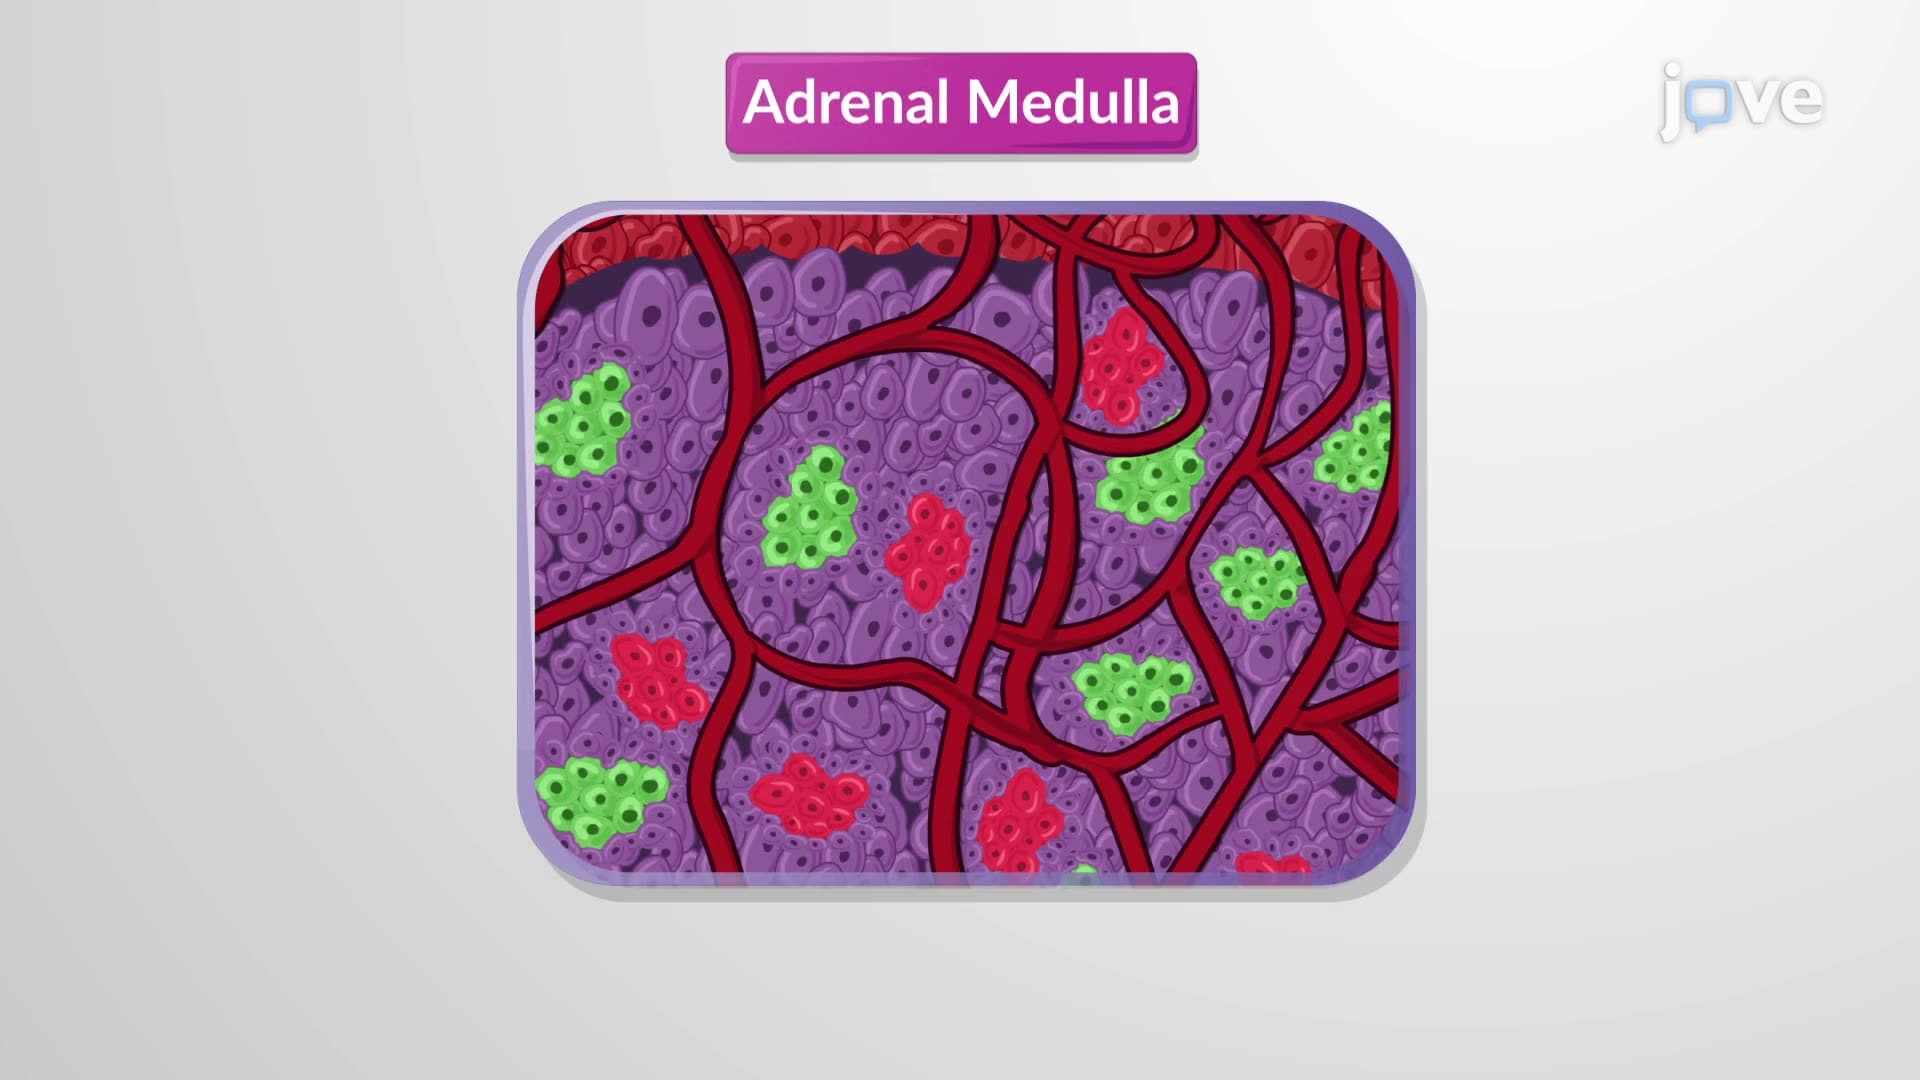
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...
 01:17
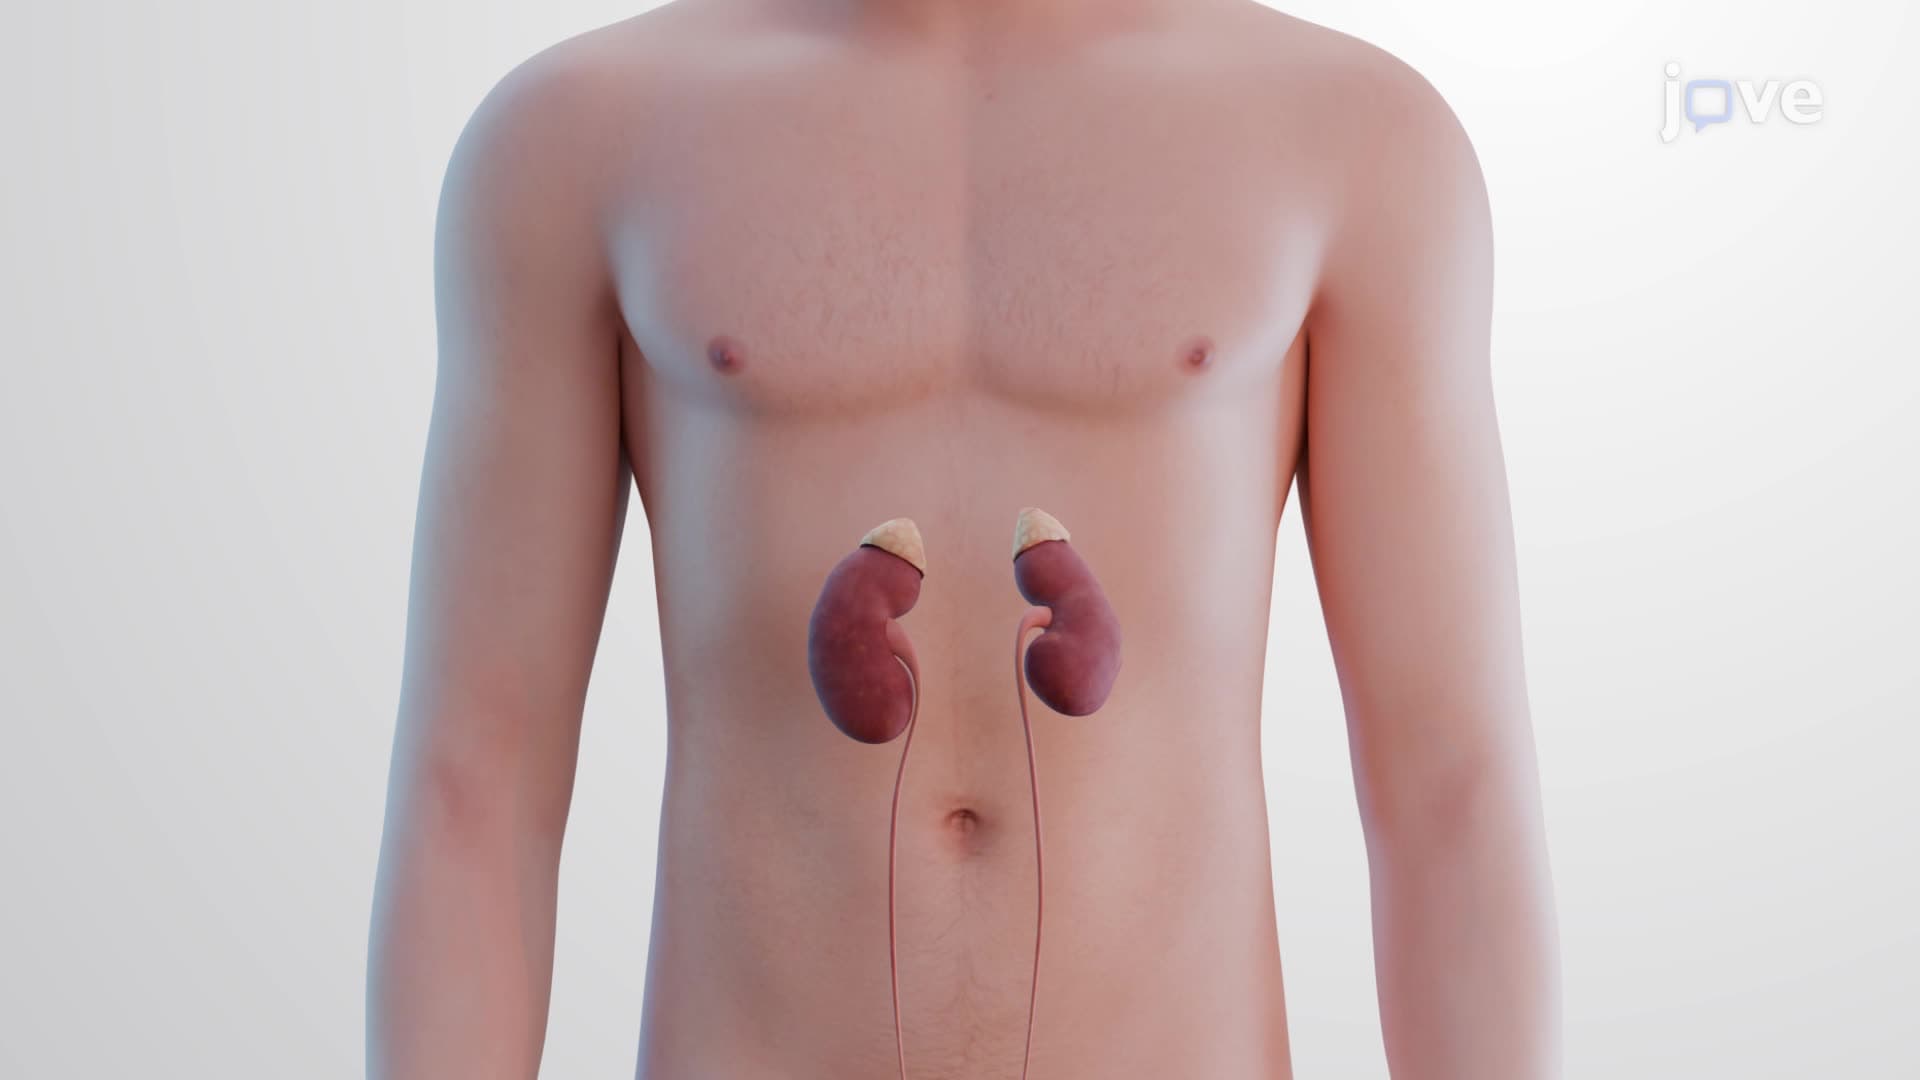
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct...
 01:37
Hypothalamic-Pituitary Axis
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:22
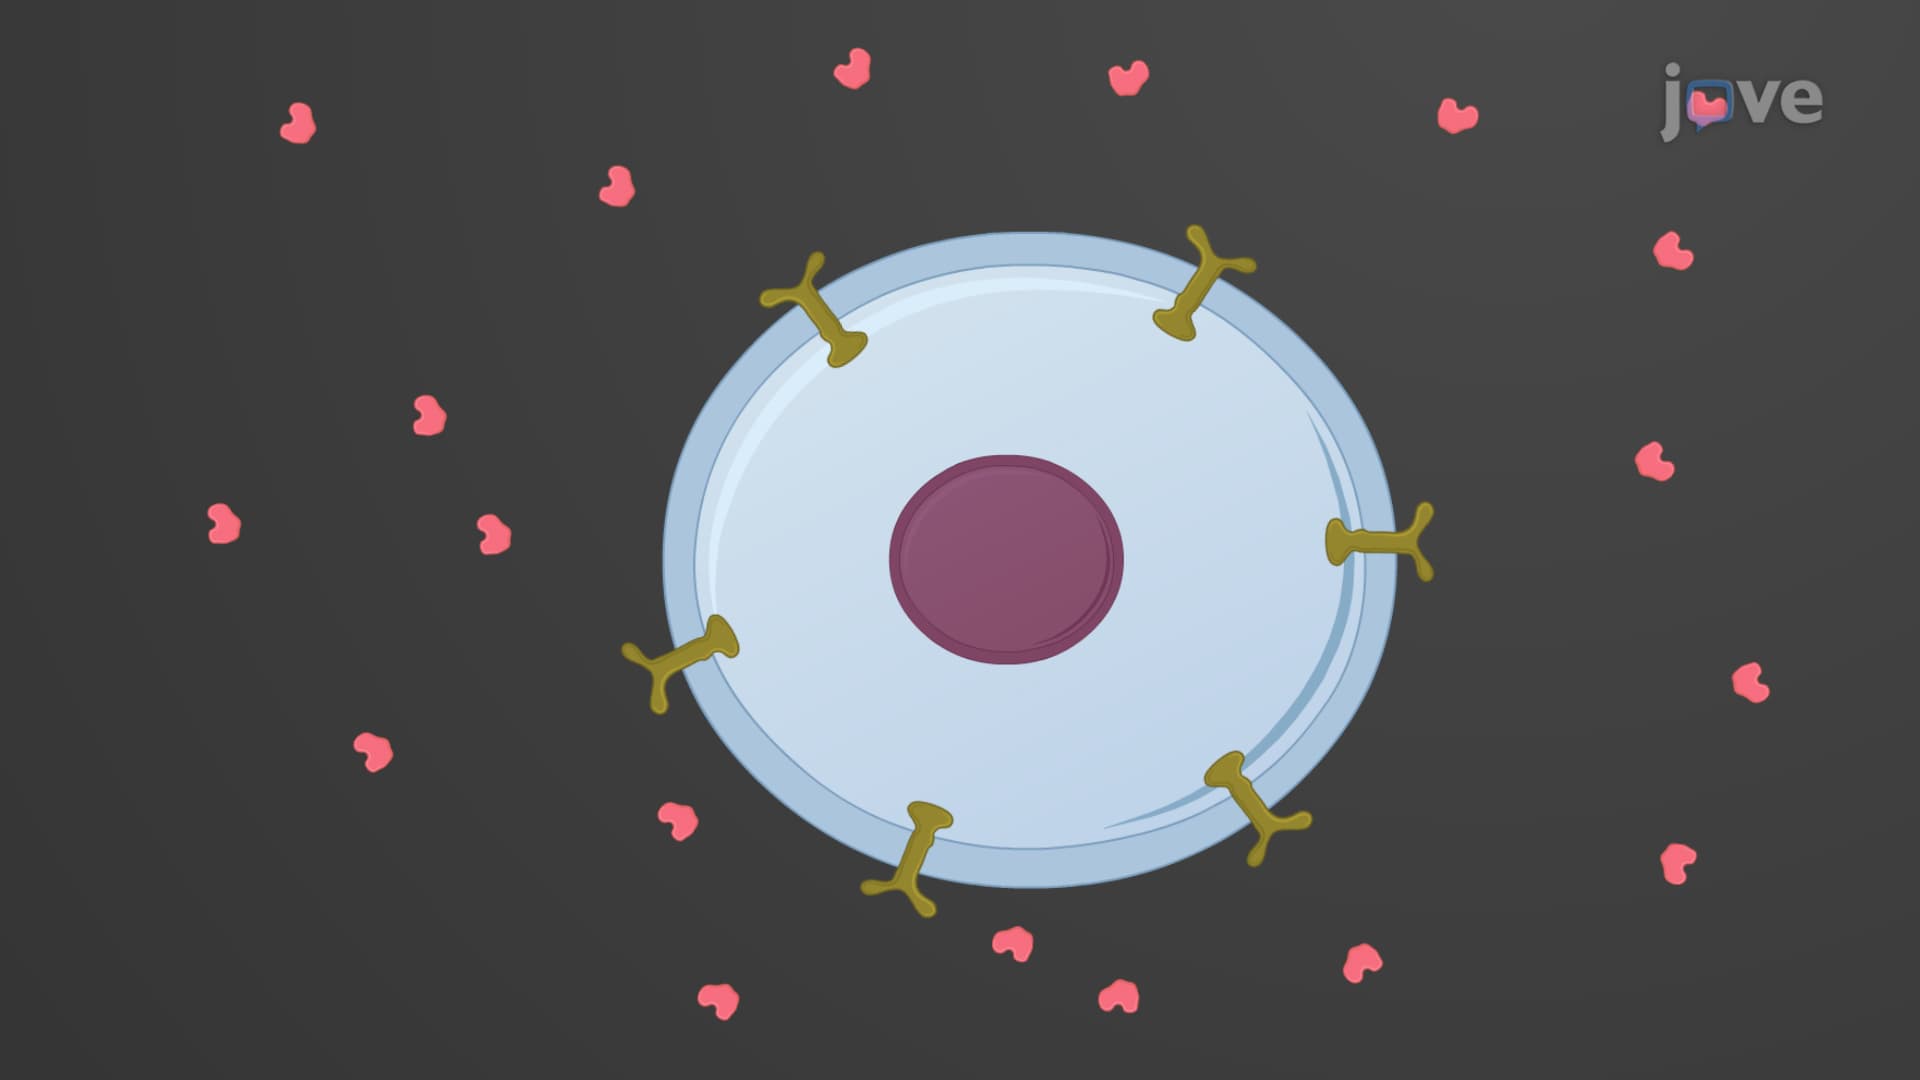
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...