Related Experiment Video
Updated: Sep 18, 2025


Optimization of Transesophageal Atrial Pacing to Assess Atrial Fibrillation Susceptibility in Mice
Published on: June 29, 2022
Very slow atrioventricular nodal reentry masquerading as junctional rhythm: Diagnostic challenges and mechanistic
Benzy J Padanilam1, Justin Arunthamakun1, Neal Joshi1
1Division of Cardiology, Department of Internal Medicine, Ascension St. Vincent Hospital, Indianapolis, Indianapolis, Indiana.

Background:
Very slow atrioventricular nodal reentrant tachycardia (AVNRT) can mimic nonreentrant accelerated junctional rhythm (JR) or junctional tachycardia (JT).
Objective:
This study aimed to describe the clinical features and mechanism of slow AVNRT masquerading as accelerated JR or JT (collectively called JRs).
Methods:
We reviewed all AVNRT and JT ablations performed at Ascension St. Vincent Hospital, Indianapolis, from July 2016 to June 2024. Patients with a tachycardia cycle length (TCL) of ≥500 ms were analyzed, focusing on clinical characteristics and electrophysiological findings.
Results:
Among 556 AVNRT ablations, 22 patients had TCL of ≥500 ms. Nine were clinically diagnosed as having JR based on 1 or more of the following: initiation with junctional beats (4), an apparent accelerating JR merging into sinus rhythm (3), slow tachycardia rates at 70-110 beats/min (8), and incessant slow tachycardia with simultaneous atrial and ventricular activation identified on implantable cardioverter-defibrillator interrogation (1). Five of these 9 patients with JR diagnosis also had a supraventricular tachycardia diagnosis. During electrophysiology study, His-refractory premature atrial complex perturbed the next His signal in all 22 cases, confirming AVNRT. The mean TCL was 578 ms (range, 500-670 ms). Two patients each had initiation with junctional beats and isorhythmic dissociation with sinus rhythm at onset of AVNRT. Radiofrequency ablation successfully modified the slow pathway and eliminated AVNRT in 21 of 22 patients.
Conclusion:
Clinically apparent JRs are often very slow AVNRT in patients referred for ablation. The mechanism of AVNRT initiation with isorhythmic dissociation with sinus rhythm may be concurrent JR and AVNRT or 2-for-1 atrioventricular nodal conduction and AVNRT competing with sinus rhythm.


Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:19
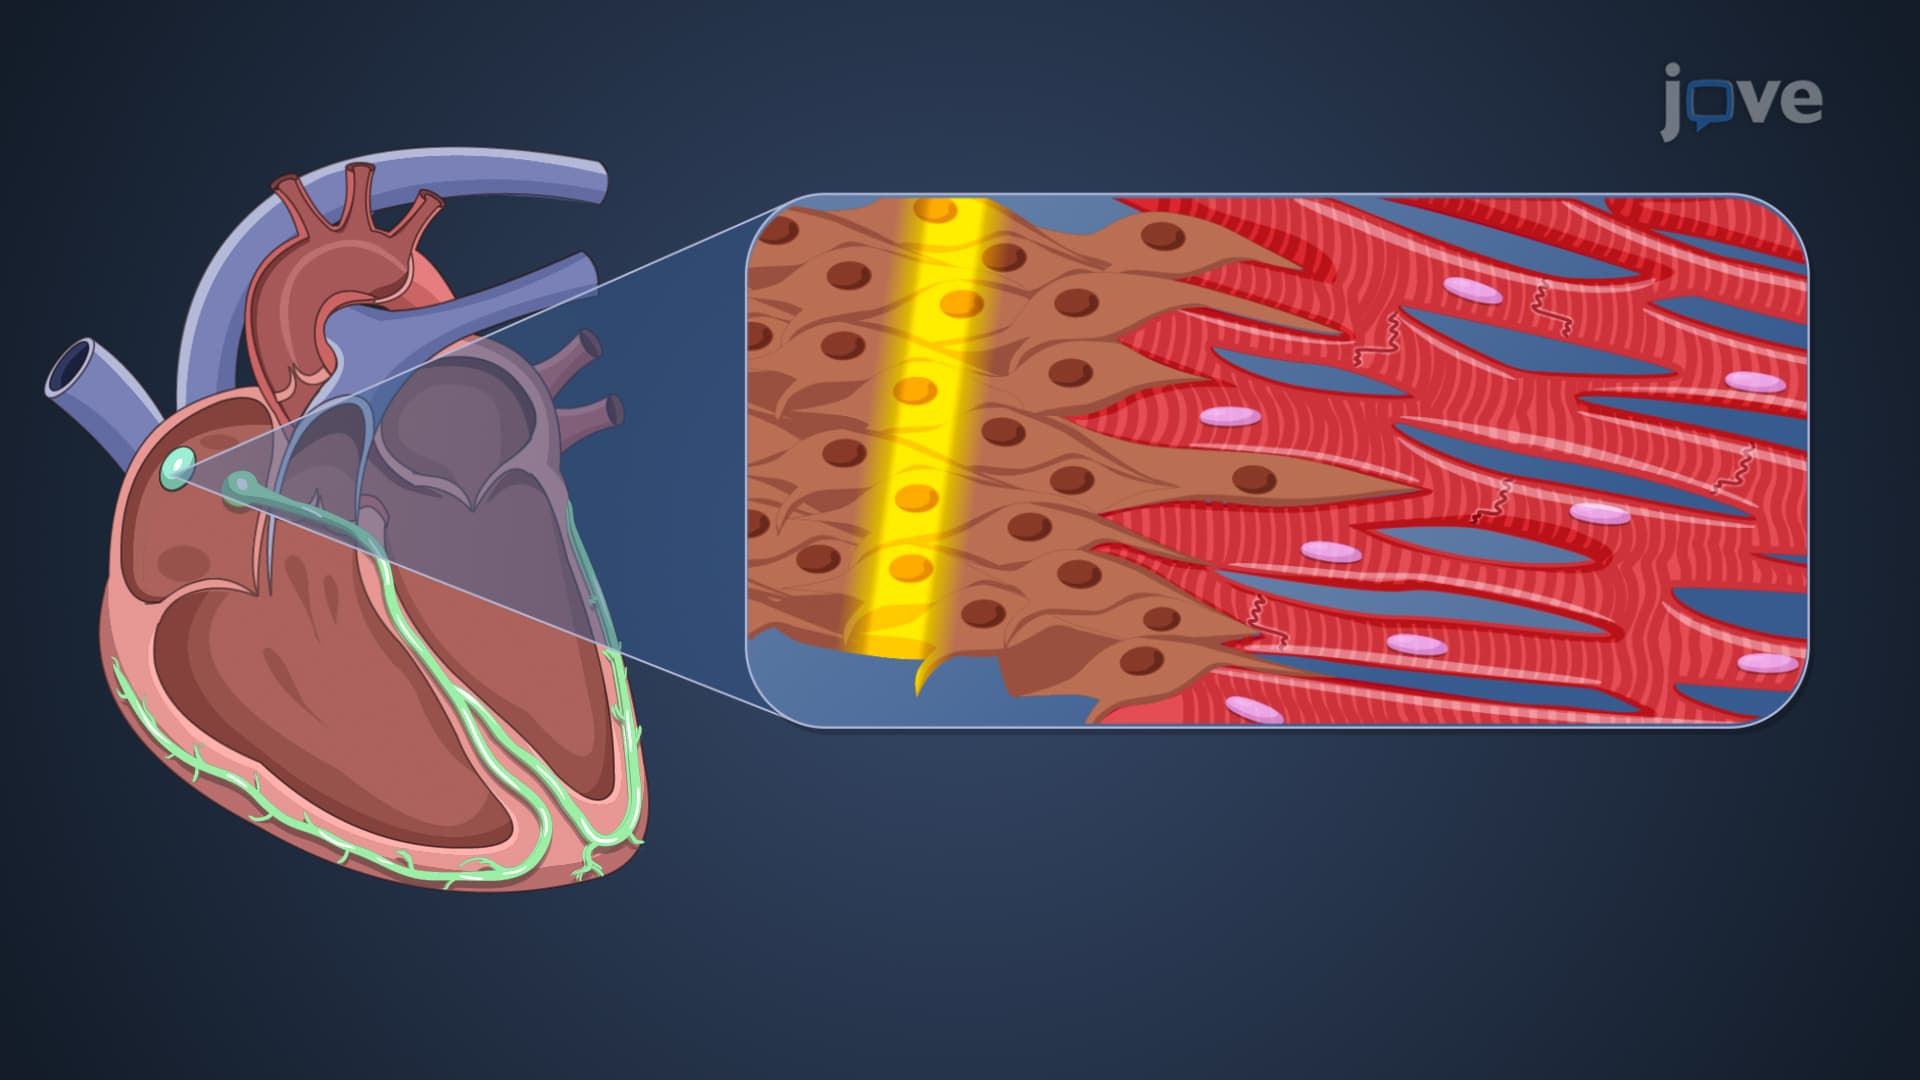
Electrophysiology of Normal Cardiac Rhythm
 01:29
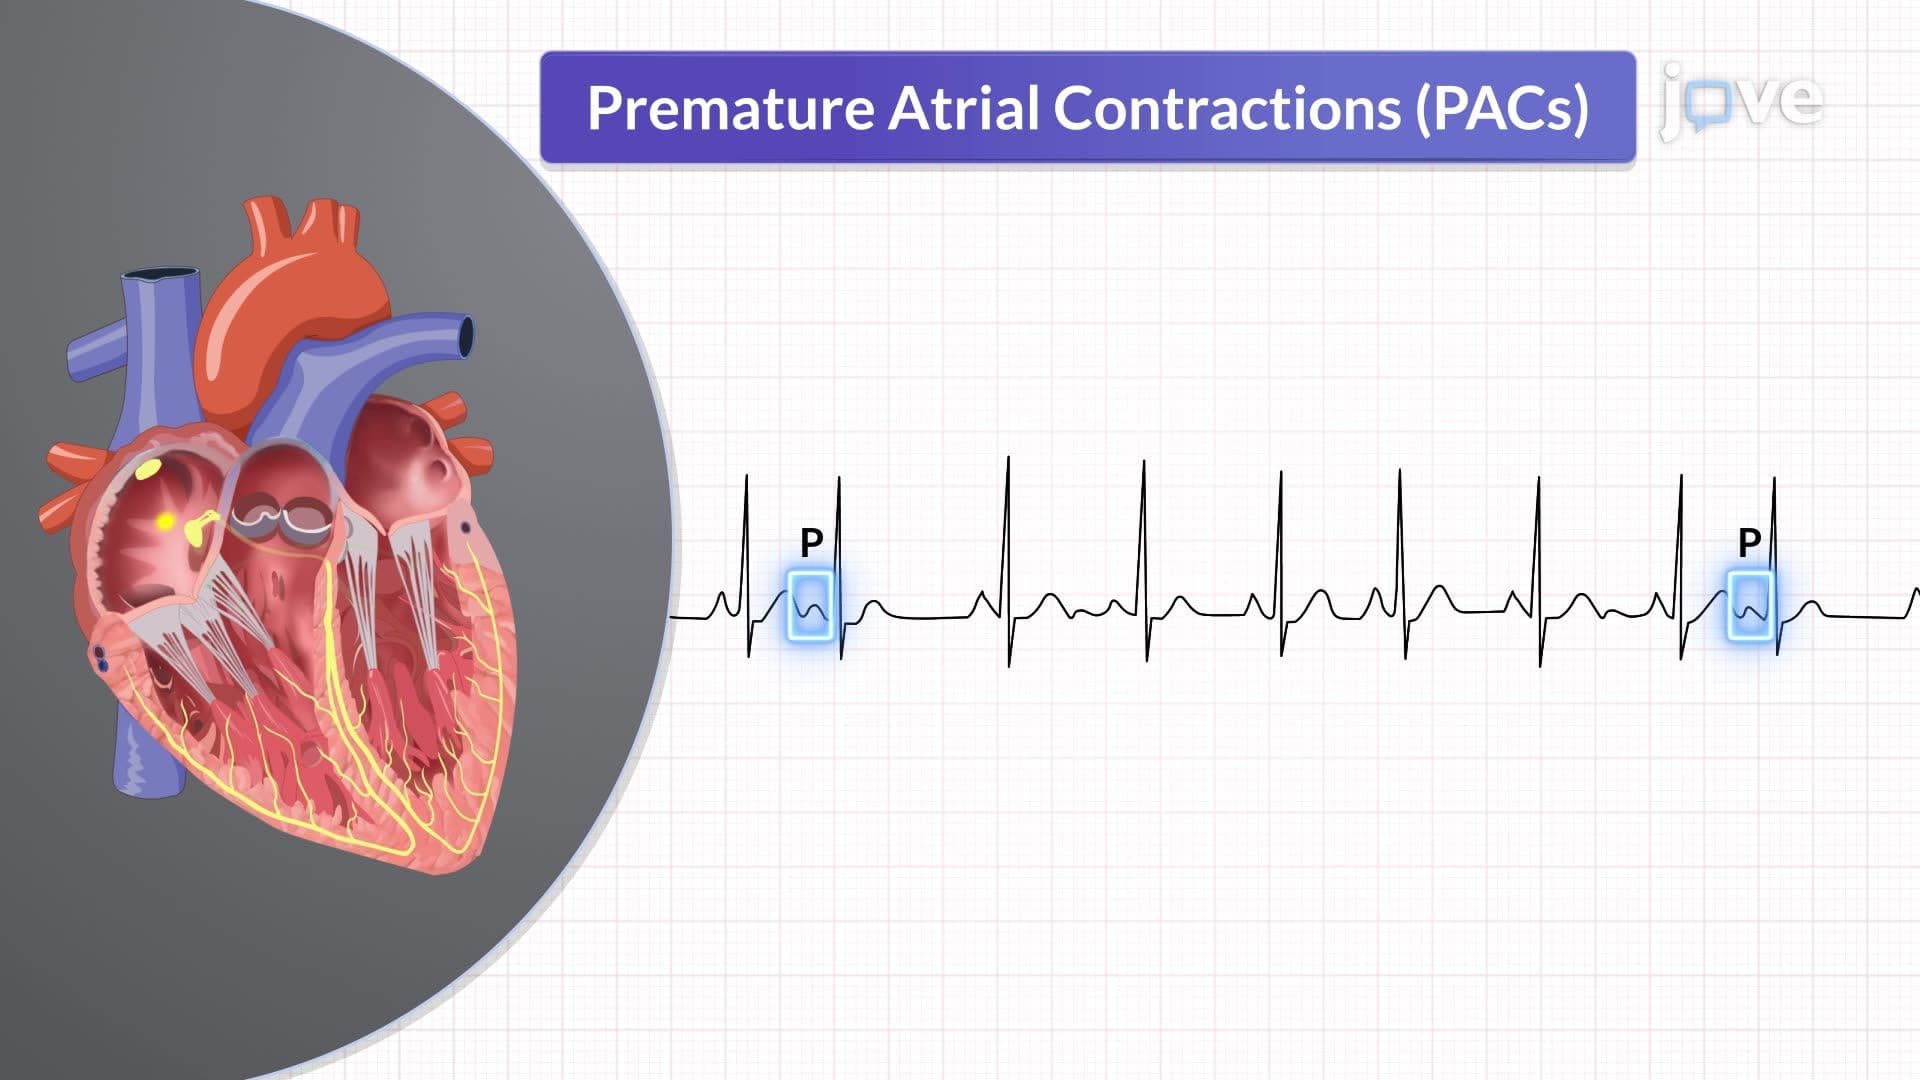
Dysrhythmias III: Characteristics of Dysrhythmias