Related Experiment Video
Updated: Jun 17, 2026
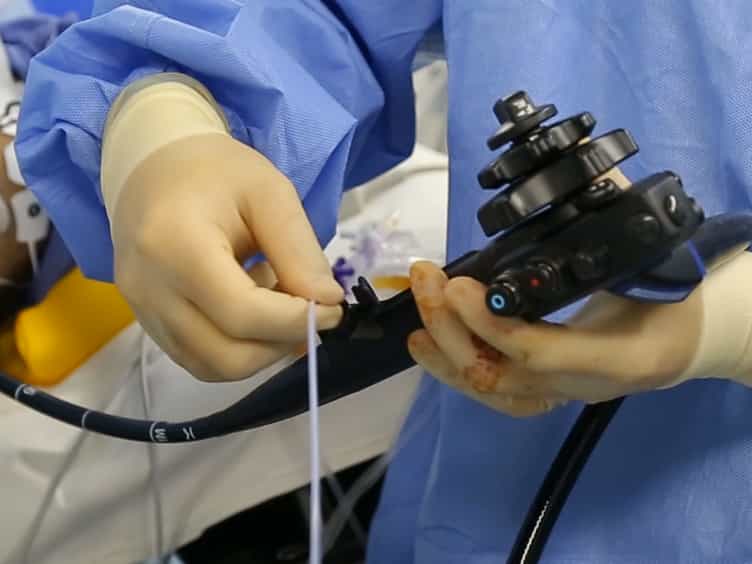

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Predictive Factors Aiding in the Estimation of Intraoperative Resources in Gastric Cancer Oncologic Surgery
Alexandru Blidișel1, Mihai-Cătălin Roșu2,3,4, Andreea-Adriana Neamțu2,5,6,7
1Department of Surgery I-Clinic of Surgical Semiotics & Thoracic Surgery, Center for Hepato-Biliary and Pancreatic Surgery, "Victor Babes" University of Medicine and Pharmacy, Eftimie Murgu Square, No. 2, 300041 Timisoara, Romania.

Abstract:
Background/Objectives: Operating rooms represent valuable and pivotal units of any hospital. Therefore, their management affects healthcare service delivery through rescheduling, staff shortage/overtime, cost inefficiency, and patient dissatisfaction, among others. To optimize scheduling, we aim to assess preoperative evaluation criteria that influence the prediction of surgery duration for gastric cancer (GC) patients. In GC, radical surgery with curative intent is the ideal treatment. Nevertheless, the intervention sometimes must be palliative if the patient's status and tumor staging prove too advanced. Methods: A 6-year retrospective cohort study was performed in a tertiary care hospital, including all cases diagnosed with GC (ICD-10 code C16), confirmed through histopathology, and undergoing surgical treatment (N = 108). Results: The results of our study confirm male predominance (63.89%) among GC surgery candidates while bringing new perspectives on patient evaluation criteria and choice of surgical intervention (curative-Group 1, palliative-Group 2). Surgery duration, including anesthesiology (175.19 [95% CI (157.60-192.77)] min), shows a direct correlation with the number of lymph nodes dissected (Surgical duration [min] = 10.67 × No. of lymph nodes removed - 32.25). Interestingly, the aggressiveness of the tumor based on histological grade (highly differentiated being generally less aggressive than poorly differentiated) shows differential correlation with surgery duration among curative and palliative surgery candidates. Similarly, TNM staging indicates the need for a longer surgical duration (pTNM stage IIA, IIB, and IIIA) for curative interventions in patients with less advanced stages, as opposed to shorter surgery duration for palliative interventions (pTNM stage IIIC and IV). Conclusions: The study quantitatively presents the resources needed for the optimal surgical treatment of different groups of GC patients, as the disease coding systems in use regard the treatment of each pathology as "standard" in terms of patient management. The results obtained are anchored in the global perspectives of surgical outcomes and aim to improve the management of operating room scheduling, staff, and resources.


