Related Experiment Video
Updated: Sep 18, 2025
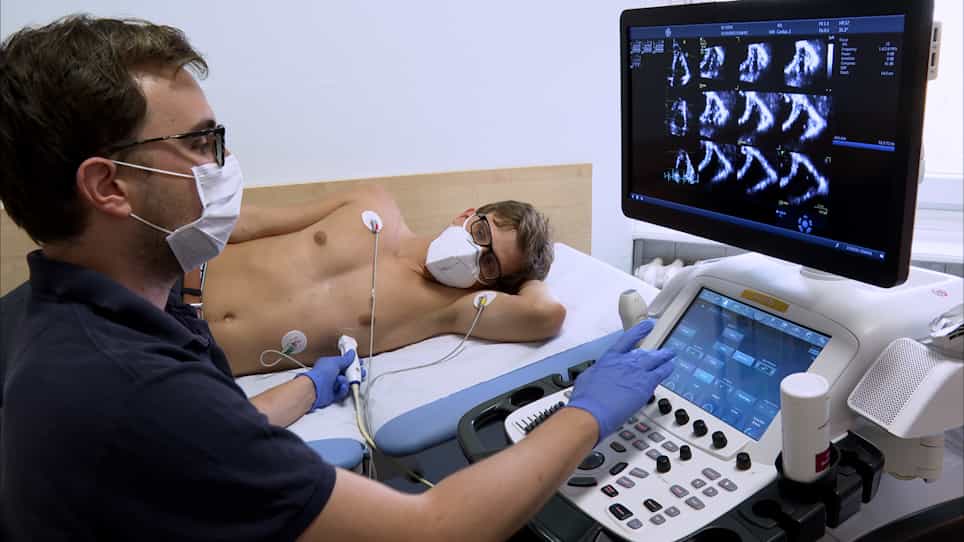

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Regional Right Ventricular Remodeling in Hypoplastic Left Heart Syndrome Across Staged Surgical Palliation and Its
Kana Yazaki1, Chun-Po Steve Fan1, Swapna Sivadas Thilakam1
1Labatt Family Heart Centre, Department of Paediatrics, Hospital for Sick Children and University of Toronto, Toronto, Ontario, Canada.

Background:
Right ventricular (RV) remodeling and (mal)adaptation contribute to high morbidity and mortality in children with hypoplastic left heart syndrome (HLHS). The mechanisms are incompletely understood. The authors hypothesized that apical hypertrophy leads to a loss of RV volume, necessitating basal functional compensation, which determines RV function and outcomes. Consequently, the aim of this study was to examine regional patterns of RV hypertrophic remodeling and their relationships to RV function in HLHS.
Methods:
Longitudinal clinical and echocardiographic parameters in 111 children with HLHS and 56 age-matched control subjects were retrospectively analyzed. To evaluate RV regional remodeling over time, six echocardiograms were analyzed for each patient: (1) after birth, (2) after stage 1 surgery, (3) before stage 2 surgery, (4) after stage 2 surgery, (5) before stage 3 surgery, and (6) the last echocardiogram or before heart transplantation or death. Global and regional RV hypertrophy, geometry, function, and strain were measured. To evaluate the relative contribution of basal vs apical shortening to overall RV ejection, we calculated the ratio of basal to apical fractional area change (FAC).
Results:
Before stage 1, apical function was impaired compared with basal function. After stage 1, RV sphericity (mid/basal ratio; P < .001) and hypertrophy (P < .001) increased, particularly at the apex (apical/basal ratio; P = .010). At the same time, global RV dilatation and dysfunction worsened, driven predominantly by decreased basal function. Patients with the lowest basal/apical FAC ratios (≤1.04) after birth tended to need transplantation (P = .07). After stage 2, RV hypertrophy (P < .001) and dilatation improved, accompanied by reduced shortening (RV FAC; P < .001) and longitudinal strain (P = .004), mainly at the base (P < .001).
Conclusion:
Patients with decreased RV basal function concomitantly with decreased apical function before stage 1 or loss of RV volume secondary to RV apical hypertrophy may be at higher risk for transplantation. The present results advance understanding of RV dysfunction in HLHS and may aid in serial assessment of these high-risk patients.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy