Related Experiment Video
Updated: Sep 17, 2025
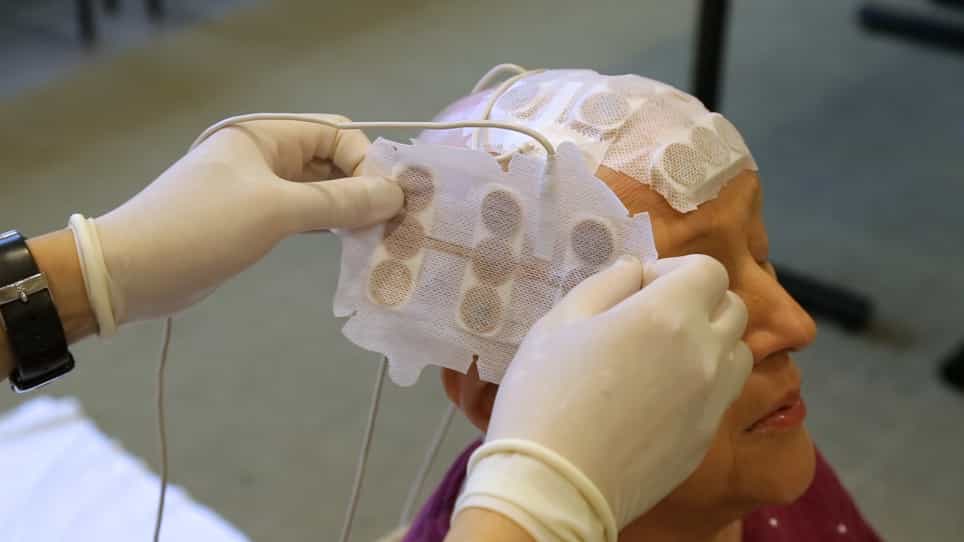

The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Second-line temozolomide in first recurrent MGMT-methylated glioblastoma after lomustine/temozolomide: Efficacy and
Thomas Zeyen1, Antonia Treiber1, Matthias Schneider2
1Department of Neurooncology, Center for Neurology and Center for Integrated Oncology (CIO), University Hospital Bonn, Bonn, Germany.

Background:
The optimal salvage therapy for recurrent MGMT-methylated glioblastoma (GBM), IDH wildtype, remains undefined. While lomustine is often used in clinical trials and considered standard-of-care, cumulative toxicity precludes its use in patients previously treated with lomustine/temozolomide. The role of temozolomide rechallenge in this setting is unclear.
Methods:
This monocentric retrospective study included 70 patients with MGMT-methylated GBM, IDH wildtype, who received lomustine/temozolomide as first-line therapy. Descriptive data on second-line therapies were collected, and therapy responses were assessed. Survival outcomes were evaluated using Kaplan-Meier analysis.
Results:
Of 55 patients with documented tumor progression, 40 patients received second-line therapy. The most frequently used systemic therapy was temozolomide (n = 33, 79% of patients with second-line therapy), with a median number of 6 cycles and hematotoxicity grade 3 or 4 observed in <20% of patients. Among patients receiving temozolomide only, stable disease or partial response was achieved in 53.3%, with a progression-free survival rate at 6 months after first recurrence of 50% and a 1-year OS rate of 45%.
Conclusions:
Temozolomide rechallenge is a common, safe, and effective second-line option for patients with MGMT-methylated, IDH wildtype GBM following first-line lomustine/temozolomide therapy. These findings support its consideration as a salvage therapy in appropriate clinical scenarios.


