Related Experiment Video
Updated: Sep 17, 2025
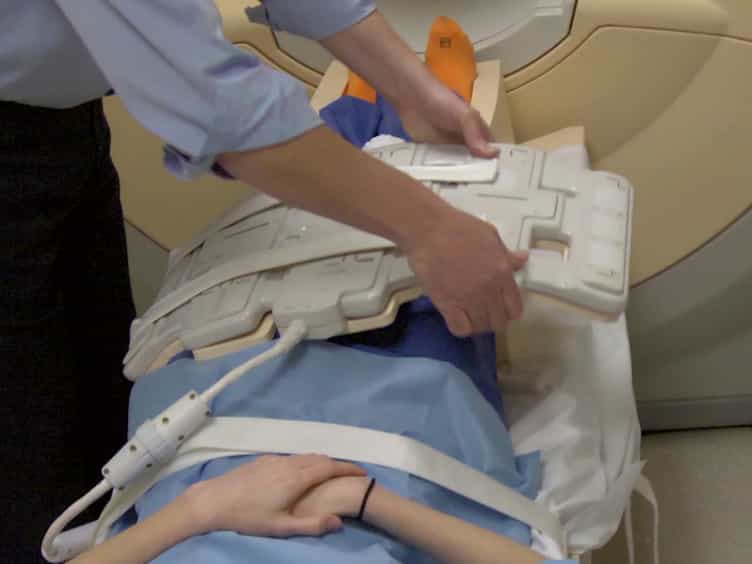
Quantitative Magnetic Resonance Imaging of Skeletal Muscle Disease
Published on: December 18, 2016
Advances in JDM: biomarker and MRI sensitivity, outcomes and steroid management in a Dutch national prospective
Saskia R Veldkamp1, Laura van der Griend2, Elsbeth Noppers2
1Center for Translational Immunology, University Medical Center Utrecht, Utrecht, The Netherlands.

Insights
This study highlights that while Juvenile Dermatomyositis (JDM) treatments are improving, many children experience disease flares and refractory conditions. New biomarkers like Galectin-9 and CXCL10 show promise for better JDM diagnosis and management.
Area of Science:
- Pediatric Rheumatology
- Autoimmune Diseases
- Inflammatory Disorders
Background:
- Juvenile Dermatomyositis (JDM) is a rare, chronic childhood autoimmune disease.
- It affects muscles and skin, leading to significant morbidity.
- Understanding the Dutch JDM population's characteristics and outcomes is crucial for improving care.
Purpose of the Study:
- To prospectively characterize the demographics, clinical features, and treatment outcomes of the Dutch JDM population.
- To evaluate diagnostic markers and disease course in JDM patients.
- To identify unmet needs in JDM management.
Main Methods:
- Prospective evaluation of JDM patients diagnosed between 2007-2024.
- Data collection included demographics, clinical features, diagnostic tests (CK, Galectin-9, CXCL10), and MRI.
- Treatment and follow-up data were analyzed over a median of 3.2 years.
Main Results:
- 83 patients (65% female) were included, with a median age of 6.0 years at diagnosis.
- Proximal muscle weakness (94.9%) and Gottron's papules (79.7%) were common.
- IFN-related biomarkers Galectin-9 (98.3%) and CXCL10 (93.3%) showed higher diagnostic sensitivity than CK (73.1%).
- MRI revealed muscle edema in 90.9% of patients.
- Despite treatment, 32.5% experienced flares, and 28.9% had refractory disease; 14.5% developed calcinosis.
Conclusions:
- Galectin-9 and CXCL10 offer superior diagnostic sensitivity over CK in JDM.
- MRI is highly sensitive for detecting muscle edema.
- Refractory disease and flares remain common challenges in JDM management.
- Predictors for safe immunosuppressant tapering and early targeted therapy are needed.
Objectives:
JDM is a rare chronic inflammatory disorder of childhood. The aim of this prospective study was to describe the characteristics and outcomes of the Dutch JDM population.
Methods:
Demographics, clinical features, diagnostic test results and treatment were prospectively evaluated at diagnosis and during follow-up visits in JDM patients diagnosed between 2007 and 2024 in the study-coordinating centre and between 2015 and 2024 in five other tertiary referral hospitals.
Results:
A total of 83 patients were included (65% female). Median age at diagnosis was 6.0 years (IQR 4-9). Median follow-up was 3.2 years (IQR 1.4-5.8). The most common features at diagnosis were proximal muscle weakness (94.9%) and Gottron's papules/sign (79.7%). While CK was abnormal in 73.1%, IFN-related biomarkers Galectin-9 and CXCL10 were elevated in 98.3% and 93.3% at diagnosis, respectively. Whole-body MRI showed muscle oedema in 30/33 (90.9%) patients. Corticosteroids could be tapered to 0.2 mg/kg at 6 months in 41.5%. Of all patients, 27 (32.5%) experienced one or more flares and 24 (28.9%) had a refractory disease course. Calcinosis occurred in 12 patients (14.5%). At last follow-up, 28.9% of patients had clinically inactive disease without medication. No patient died.
Conclusion:
This study demonstrates the superior diagnostic sensitivity of Galectin-9 and CXCL10 over CK, the high sensitivity of MRI and the frequent occurrence of refractory disease and flares despite treatment. Reliable predictors are needed to identify patients who can safely taper immunosuppressants versus those needing continued treatment, and who may benefit from targeted therapies initiated upfront.

Related Concept Videos
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:14
Myocarditis III: Medical Management
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:14
Changes in Skin Color: Clinical Perspectives
Albinism
Albinism is a genetic disorder that affects (completely or partially) the coloring of skin, hair, and eyes. The defect is primarily...
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests