Association of Polypharmacy and Potentially Inappropriate Medications With Outcomes in Older Adults With DLBCL: A Population Study
Related Experiment Video
Updated: Sep 17, 2025

Assessment of Dependence in Activities of Daily Living Among Older Patients in an Acute Care Unit
Published on: September 30, 2020
Inna Y Gong1,2, Abi Vijenthira1,2, Zharmaine Ante3
11Division of Medical Oncology and Hematology, Princess Margaret Cancer Centre, Toronto, Ontario, Canada.

Background:
Polypharmacy and potentially inappropriate medications (PIMs) may be associated with survival and health care utilization in older patients undergoing treatment for diffuse large B-cell lymphoma (DLBCL).
Methods:
This population-based study examined patients with DLBCL aged ≥66 years receiving rituximab-based therapy from January 1, 2006, to December 31, 2017, and followed them until March 31, 2019. Polypharmacy was defined as taking ≥5 or ≥8 concurrent medications within 90 days of treatment initiation. PIMs were assessed using the Anticholinergic Risk Scale (ARS) and the Geriatric Oncology Potentially Inappropriate Medications (GO-PIM) scale. Cox regression and negative binomial models were conducted, adjusting for age, sex, frailty, and comorbidity burden (Aggregated Diagnosis Groups [ADGs]). The primary outcome was all-cause mortality, and the secondary outcome was health care utilization, measured by unplanned emergency department visits and hospitalizations.
Results:
A total of 5,527 patients were included (median age, 75 years; 48% female), of whom 69% and 40% had polypharmacy defined as ≥5 and ≥8 medications, respectively. In terms of PIMs, 27% of patients had at least one PIM based on ARS, whereas 70% had a high-risk medication based on the GO-PIM scale. Polypharmacy was associated with increased risk of all-cause mortality in the adjusted analysis, with an adjusted hazard ratio (aHR) of 1.14 (95% CI, 1.05-1.23; P=.0021) for patients taking ≥5 medications, and 1.18 (95% CI, 1.09-1.27; P<.0001) for those taking ≥8 medications. Increasing number of PIMs was associated with increased mortality risk. Polypharmacy was associated with an increased relative risk of health care utilization, with an adjusted rate ratio (aRR) of 1.14 (95% CI, 1.06-1.22; P=.0004) for patients taking ≥5 medications, and 1.16 (95% CI, 1.08-1.24; P<.0001) for those taking ≥8 medications. For PIMs, a higher score on the GO-PIM scale was associated with greater risk of health care utilization (aRR for ≥3 medications, 1.20; 95% CI, 1.09-1.32; P=.0003), whereas ARS was not.
Conclusions:
Polypharmacy and PIMs are associated with an increased relative risk of mortality and health care utilization among older adults with DLBCL undergoing treatment, independent of frailty and comorbidity.
More Related Videos
 12:18
A Machine Learning Approach to Design an Efficient Selective Screening of Mild Cognitive Impairment
Published on: January 11, 2020
 08:56
Simultaneous Imaging and Flow-Cytometry-based Detection of Multiple Fluorescent Senescence Markers in Therapy-Induced Senescent Cancer Cells
Published on: July 12, 2022
Related Concept Videos
 01:28
Drug Therapy
Antianxiety Medications
 01:21
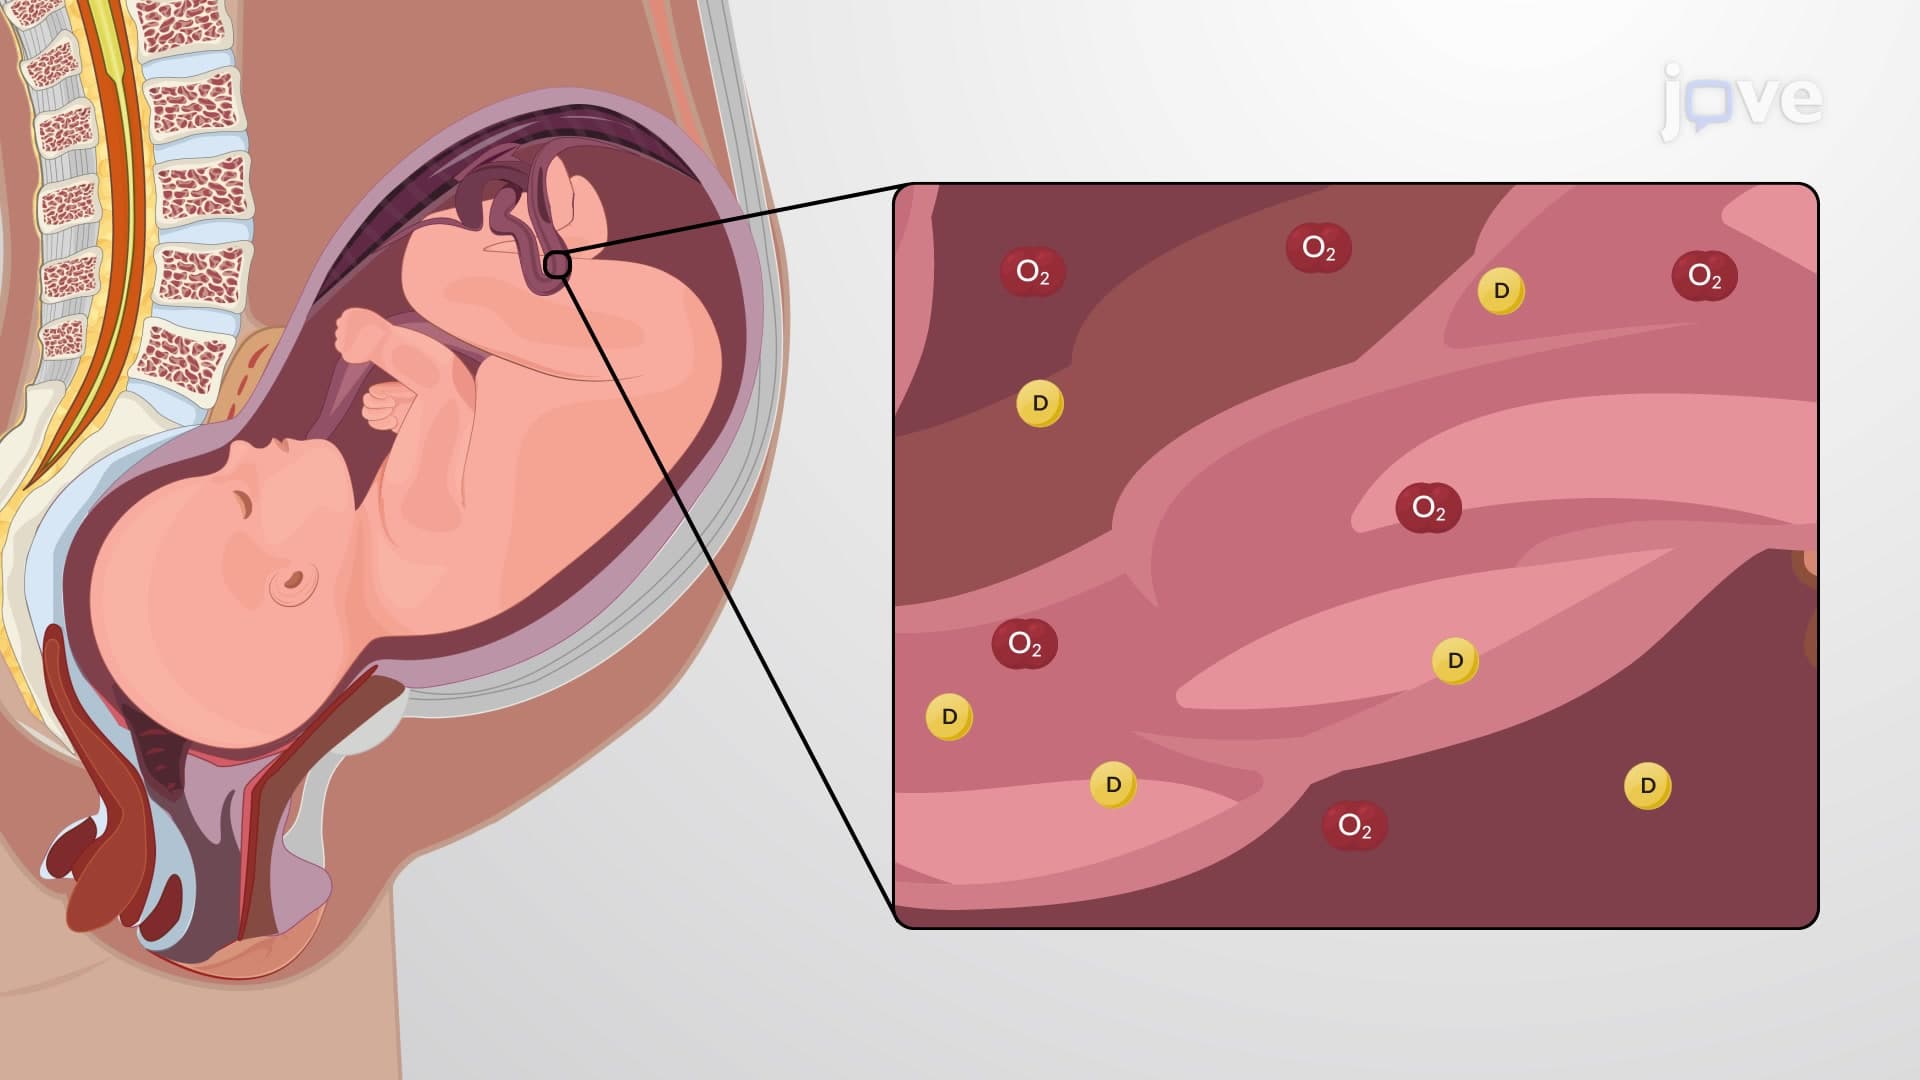
Factors Affecting Drug Response: Overview
 01:19
Nonlinear Pharmacokinetics: Overview
Nonlinearity can arise due to the saturation of plasma protein-binding or...
 01:29
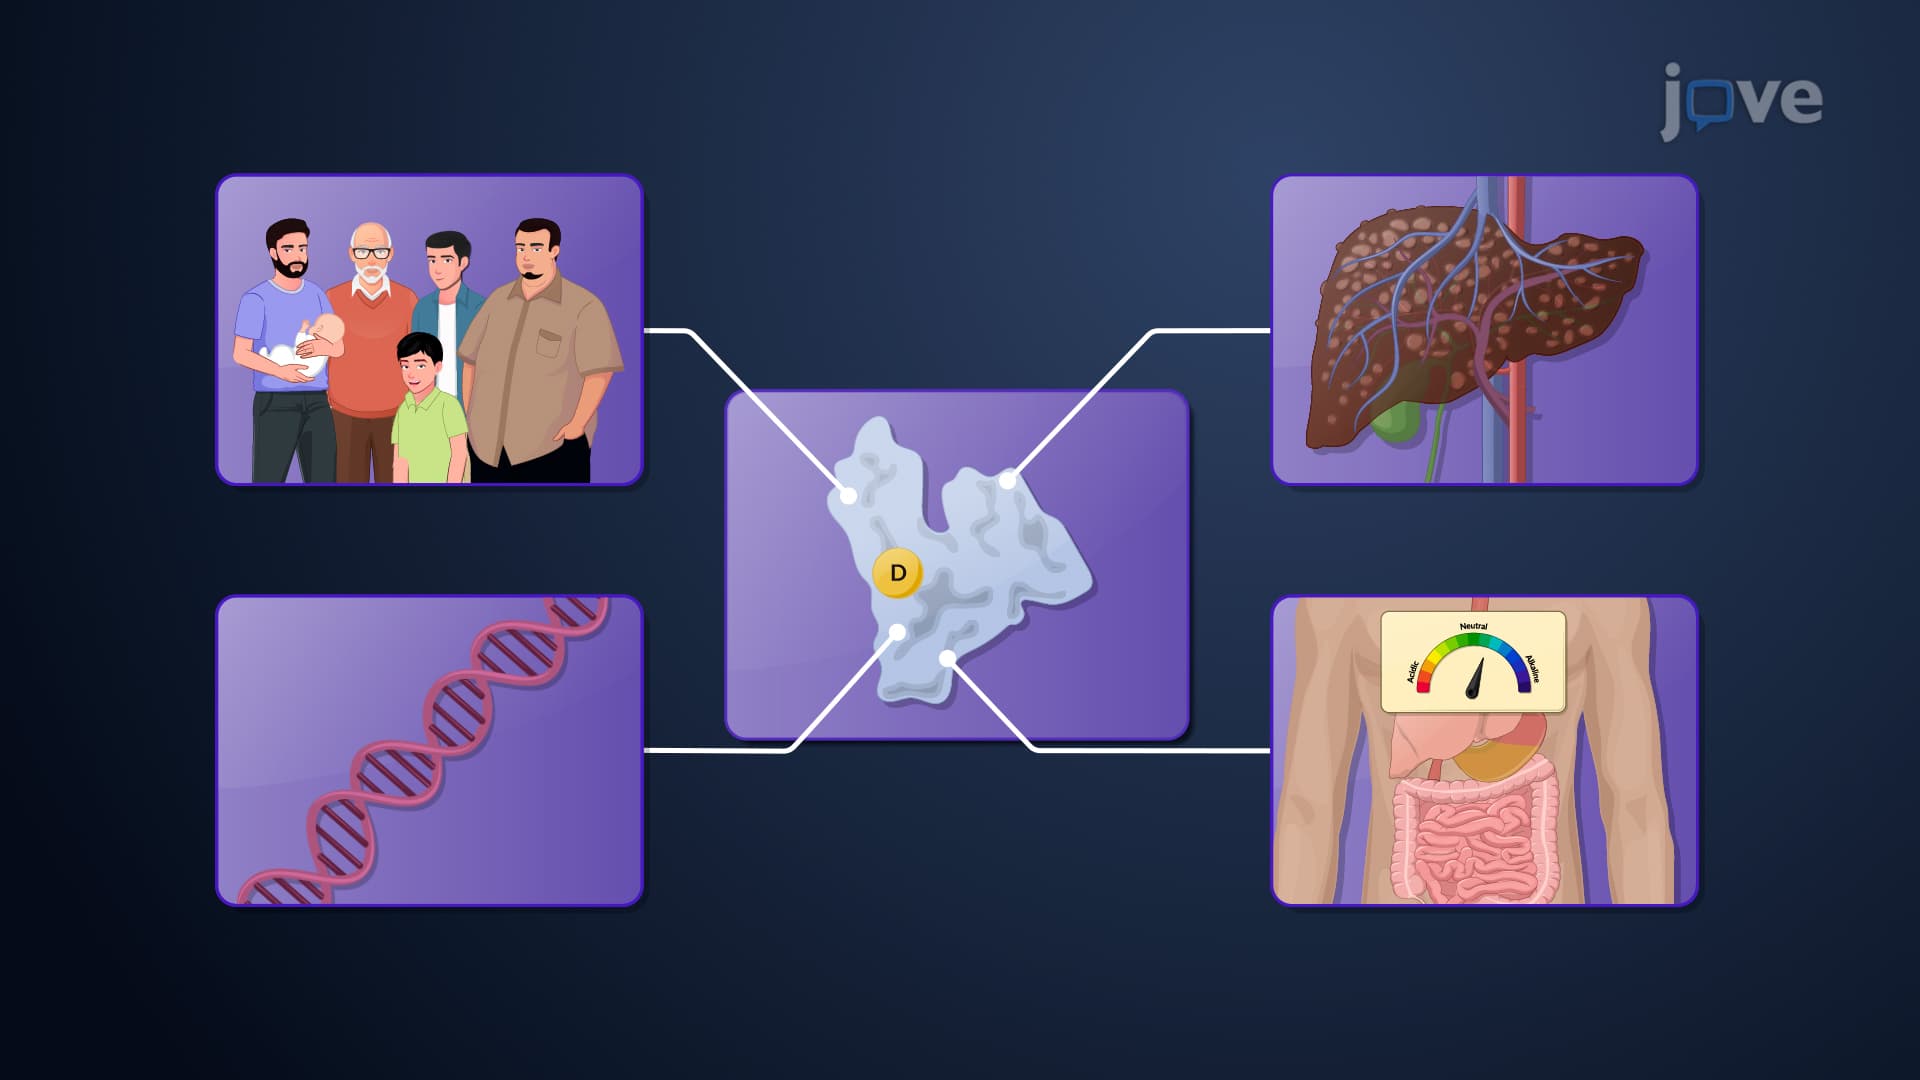
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:26
Psychosis: Goals of Pharmacotherapy
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of...